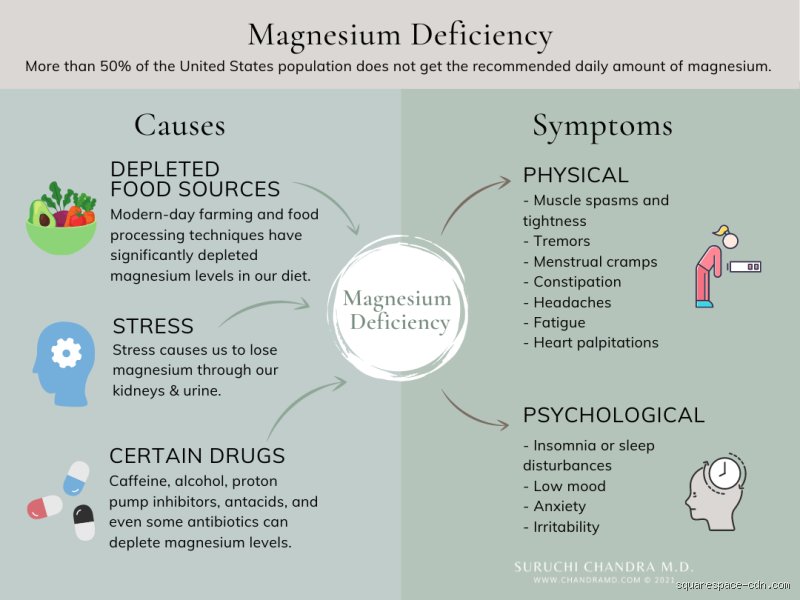
Pharmaceutical interventions and iatrogenic depletion
Proton pump inhibitors (PPIs)
Long-term utilization of proton pump inhibitors—such as omeprazole, lansoprazole, and pantoprazole—is firmly linked to chronic hypomagnesemia. PPIs alter the luminal pH of the gastrointestinal tract, which impairs active and passive transport mechanisms responsible for intestinal magnesium absorption, specifically involving transient receptor potential melastatin channels (TRPM6 and TRPM7). The United States Food and Drug Administration (FDA) has issued safety communications advising clinicians to monitor serum magnesium levels in patients requiring prolonged PPI therapy, particularly those concurrently taking other depleting agents.
Diuretics
Both loop diuretics (e.g., furosemide) and thiazide diuretics (e.g., chlorthalidone, hydrochlorothiazide) significantly increase urinary magnesium excretion.
Loop Diuretics: These drugs inhibit the sodium-potassium-chloride cotransporter in the thick ascending limb of the loop of Henle, a primary site for passive paracellular magnesium reabsorption. By disrupting the lumen-positive electrical gradient, loop diuretics prevent passive ion drag, leading to substantial renal wasting.
Thiazide Diuretics: These agents act on the distal convoluted tubule. While initial use causes acute natriuresis and hypomagnesemia, long-term administration often downregulates the apical magnesium channel TRPM6, perpetuating chronic deficiency.
Nephrotoxic chemotherapeutics and antibiotics
Platinum-based chemotherapeutic agents, most notably cisplatin, induce direct tubular toxicity, damaging the renal epithelial cells responsible for divalent cation reabsorption. This often results in severe, treatment-resistant renal magnesium wasting that can persist long after chemotherapy cessation. Similarly, certain antimicrobial agents, including aminoglycosides and amphotericin B, disrupt renal tubular integrity, triggering profound electrolyte derangements.
Endocrine disruptions and metabolic pathologies
Endocrine homeostasis relies heavily on adequate magnesium status, yet several metabolic disorders create a bidirectional feedback loop that accelerates depletion.
Diabetes mellitus and insulin resistance
Type 2 diabetes mellitus and metabolic syndrome have a complex, reciprocal relationship with magnesium. Hyperglycemia induces osmotic diuresis, flushing excess glucose and dissolved electrolytes, including magnesium, through the renal tubules. Simultaneously, intracellular magnesium acts as an essential cofactor for tyrosine kinase activity on insulin receptors. A deficiency in intracellular magnesium impairs insulin signaling, worsening insulin resistance, which in turn exacerbates renal glucose spillage and accelerates magnesium loss.
Hyperparathyroidism and thyroid disorders
Parathyroid hormone (PTH) regulates calcium and magnesium homeostasis. Primary hyperparathyroidism can increase bone resorption and alter renal handling of divalent cations. Conversely, severe magnesium deficiency can functionally impair PTH secretion and cause target-tissue resistance to PTH, resulting in refractory hypocalcemia. Thyroid hormone imbalances, particularly thyrotoxicosis, increase metabolic turnover and renal clearance, raising overall daily requirements.
Lifestyle stressors, exercise physiology, and environmental variables
Behavioral patterns, physiological stress, and physical exertion impose significant demands on mineral reserves.
Chronic psychological and physiological stress
The human stress response activates the hypothalamic-pituitary-adrenal (HPA) axis, releasing catecholamines (adrenaline and noradrenaline) and glucocorticoids (cortisol). This neuroendocrine cascade stimulates intracellular shifts, driving magnesium from the extracellular fluid into the bloodstream, where it is subsequently filtered and excreted by the kidneys. Chronic, unremitting psychological stress thus depletes total body stores over time.
High-Intensity athletics and profuse sweating
While physical activity promotes cardiovascular health, heavy endurance training and intense athletic competition accelerate mineral loss. Sweat contains measurable concentrations of magnesium. When an individual engages in prolonged physical exertion in high-temperature environments, cumulative losses through perspiration, combined with increased metabolic demands for muscle contraction and cellular repair, can precipitate deficiency if intake is not proportionally scaled.
Alcoholism and hepatic dysfunction
Chronic alcohol consumption is among the most potent clinical drivers of severe hypomagnesemia. Ethanol acts as a direct renal toxin, impairing the reabsorptive capacity of the loop of Henle and the distal convoluted tubule. Chronic alcoholism is frequently compounded by malnutrition, pancreatic exocrine insufficiency, chronic diarrhea, and secondary hyperaldosteronism, creating a multi-factorial etiology for profound mineral depletion.
Inherited channelopathies and renal wasting syndromes
Though less common than acquired deficiencies, genetic mutations affecting specific transport proteins underscore the biological mechanisms governing magnesium homeostasis.
Gitelman Syndrome: An autosomal recessive renal tubular disorder caused by mutations in the SLC12A3 gene, which encodes the thiazide-sensitive sodium-chloride cotransporter in the distal convoluted tubule. This leads to hypomagnesemia, hypocalciuria, and hypokalemia.
Bartter Syndrome: A group of rare autosomal recessive disorders affecting the thick ascending limb of the loop of Henle, impairing salt reabsorption and causing secondary renal potassium and magnesium wasting.
Familial Hypomagnesemia with Secondary Hypocalcemia (FHHNC): Caused by mutations in the CLDN16 or CLDN19 genes encoding paracellin-1 (claudin-16), disrupting tight junctions and blocking paracellular magnesium reabsorption in the renal medulla.
Diagnostic complexities and subclinical Evaluation
Identifying magnesium deficiency presents a significant clinical hurdle. Serum magnesium testing remains the standard diagnostic metric in routine clinical practice, yet extracellular serum accounts for less than one percent of total body magnesium. The vast majority of the mineral resides intracellularly within bone, muscle, and soft tissues.
Because homeostatic mechanisms tightly regulate serum concentrations to protect vital functions such as cardiac electrophysiology, serum magnesium levels can remain deceptively normal even in the presence of severe intracellular depletion. Consequently, subclinical deficiency frequently goes undetected by standard blood panels. Advanced diagnostic evaluations, such as ionized serum magnesium assays, red blood cell (RBC) magnesium testing, or oral magnesium tolerance loading tests, offer higher diagnostic sensitivity but are less frequently utilized in standard screening protocols.
Strategic approaches to prevention and management
Addressing the multifactorial causes of magnesium deficiency requires a targeted, individualized strategy.
+-------------------------------------------------------------+
| Primary Intervention Vectors |
+-------------------------------------------------------------+
| 1. Dietary Optimization |
| - Incorporation of leafy greens, seeds, nuts, legumes |
| - Selection of unrefined, whole-food grain sources |
+-------------------------------------------------------------+
| 2. Pharmacological Review |
| - Assessment of PPI, diuretic, and antibiotic regimens |
| - Evaluation of substitution or dose titration |
+-------------------------------------------------------------+
| 3. Targeted Supplementation |
| - Bioavailable salt forms (glycinate, malate, citrate) |
| - Mitigation of gastrointestinal side effects |
+-------------------------------------------------------------+
Dietary optimization serves as the foundation of prevention, emphasizing whole foods rich in chlorophyll-bound magnesium, such as dark leafy greens, pumpkin seeds, almonds, black beans, and whole grains. In cases driven by unavoidable pharmacotherapy or chronic pathology, clinician-supervised supplementation utilizing bioavailable organic salts, such as magnesium glycinate, malate, or citrate, can effectively restore intracellular concentrations. By understanding the interplay between diet, medication, genetics, and metabolic stress, clinicians and individuals can proactively identify vulnerabilities and maintain optimal physiological function.