When planning your content for optimal search engine optimization (SEO), structuring your article with a clear hierarchy and keyword strategy is essential. Below is an example framework that illustrates how to integrate long-tail keywords, specific word counts, and header layouts (H1, H2, H3) to meet rigorous content requirements.
Introduction and Core Concepts
Effective search optimization starts right at the top. By placing your primary keyword in both the H1 header and the very first sentence of your introduction, you immediately signal the page topic to search engines and readers alike.
Why Early Keyword Placement Matters
Placing terms early helps search algorithms quickly crawl and contextualize the subject matter, reducing bounce rates by confirming to users they have landed on the right page.
Technical Development 1: Core Architectures
How Does Modern Infrastructure Scale?
Modern technical development relies heavily on scalable cloud architectures and modular codebases. When building robust applications, developers must balance performance, maintainability, and security.
Key Frameworks in Action
Utilizing containerization tools like Docker and orchestration systems like Kubernetes ensures consistent deployment across multiple environments. Furthermore, adopting microservices allows independent scaling of individual application components without risking the stability of the entire system.
Technical Development 2: Advanced Integration
Implementing Continuous Delivery Pipelines
Streamlining the deployment process is critical for modern engineering teams. Continuous Integration and Continuous Deployment (CI/CD) pipelines automate testing and verification, ensuring that every code commit meets rigorous quality standards before reaching production environments.
Comparison and Alternatives: Choosing the Right Stack
Monolithic vs. Microservices Architectures
When comparing system design choices, teams often weigh the simplicity of a monolithic architecture against the flexibility of microservices. While monoliths are easier to launch initially, microservices provide superior scalability and fault isolation for large-scale enterprise applications.
Would you like to customize this outline for a specific industry or keyword topic?
Key Physiological & Psychological Factors behind Suboptimal Rigidity
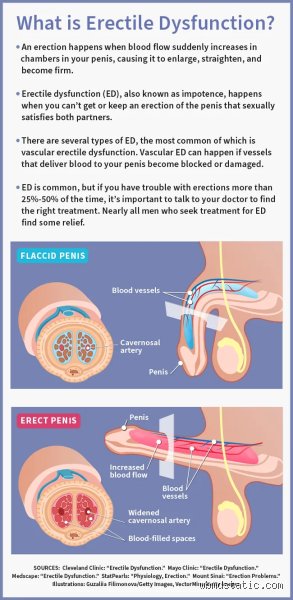
To understand why maximum firmness isn't being reached, it helps to examine how an erection functions. Rigidity relies on a delicate balance: smooth muscle tissue in the penis must relax, arteries must open wide to increase blood flow, and veins must temporarily compress to lock that blood in place. When any part of this system is disrupted, full rigidity becomes difficult to maintain.
1. Vascular & Cardiovascular Health
Erectile capacity is frequently referred to by cardiologists as a "canary in the coal mine." Because the penile arteries are significantly smaller than coronary arteries (roughly 1–2 mm compared to 3–4 mm), early stages of endothelial dysfunction or atherosclerosis often manifest as reduced erection firmness long before cardiac symptoms appear.
Endothelial Dysfunction: The lining of blood vessels (endothelium) produces nitric oxide, the crucial chemical signal telling vascular smooth muscles to relax and permit rapid blood inflow. Conditions like elevated LDL cholesterol, hypertension, or high blood sugar damage endothelial tissue, reducing nitric oxide production.
Blood Pressure Issues: Uncontrolled high blood pressure hardens arterial walls, making it harder for vessels to expand fully under pressure.
2. Hormonal Imbalances
While testosterone isn't the sole engine driving an erection, it plays a essential role in regulating libido, tissue health, and nitric oxide synthesis.
Free vs. Total Testosterone: Total testosterone levels can sometimes appear normal on standard lab panels while bioavailable or free testosterone is low due to elevated Sex Hormone-Binding Globulin (SHBG).
Elevated Prolactin or Estradiol: High levels of prolactin (often caused by chronic stress, sleep apnea, or pituitiary factors) or excess estrogen (frequently tied to body composition changes) can directly suppress erectile quality and drive.
3. Psychogenic Dynamics & Performance Anxiety
The brain is the central command module for sexual response. Even minor psychological stressors can trigger an involuntary sympathetic nervous system ("fight or flight") reaction.
Adrenaline Surge: When anxiety or self-monitoring ("spectatoring") occurs during intimacy, the body releases epinephrine and norepinephrine. These stress hormones cause immediate vasoconstriction, shunting blood away from the pelvic area back toward core muscle groups.
The Feedback Loop: Experiencing sub-maximal firmness once can create an anxious expectation for future encounters, initiating a persistent loop of performance anxiety that undermines natural arousal.
Strategic Diagnostic & Treatment Pathways
Addressing reduced rigidity effectively requires a structured, multi-pronged approach rather than relying on quick fixes.
┌────────────────────────────────────────────────────────┐
│ Comprehensive Evaluation │
│ (Comprehensive Blood Panel + Lifestyle Assessment) │
└──────────────────────────┬─────────────────────────────┘
 │
 ┌─────────────┴─────────────┐
 ▼ ▼
┌──────────────────────────┐┌──────────────────────────┐
│ Targeted Interventions ││ Medical Therapies │
│ - Sleep Optimization ││ - PDE5 Inhibitors │
│ - Exercise & Diet ││ - Hormonal Therapy │
│ - Anxiety Management ││ - Cardiovascular Care │
└──────────────────────────┘└──────────────────────────┘
Medical Evaluation & Diagnostic Testing
If reduced firmness persists for more than a few weeks, consulting a physician or urologist is the most efficient next step. Essential diagnostic markers to discuss include:
Comprehensive Lipid Panel & HbA1c: To assess cardiovascular health, insulin sensitivity, and vascular risk factors.
Hormone Panel: Total and free testosterone, SHBG, LH, FSH, prolactin, and estradiol—ideally drawn in the early morning when testosterone levels peak.
Morning Erection Assessment: Tracking nighttime or early-morning involuntary erections can help distinguish between physical (vascular/hormones) and psychogenic causes, as nocturnal erections occur independent of conscious anxiety.
Evidence-Based Lifestyle & Therapeutic Options
Cardiovascular & Exercise Interventions: Aer### Psychological Factors and the "Performance Trap"
While biological processes set the stage, the central nervous system acts as the master switch. Psychogenic factors can disrupt erectile quality just as effectively as physical vascular blockages.
The Anxiety-Adrenaline Loop
When you worry about whether you will achieve or maintain a full erection, your body perceives that worry as a stressor. In response, the sympathetic nervous system triggers a mild "fight-or-flight" response, releasing epinephrine (adrenaline) and cortisol.
Adrenaline acts as a direct vasoconstrictor. It signals the smooth muscle lining the penile arteries to contract, restricting incoming blood flow—the exact opposite of what needs to happen for a complete erection. This creates a self-reinforcing cycle: a minor, transient failure causes anxiety, anxiety causes a surge of adrenaline, and adrenaline guarantees another incomplete erection on the next attempt.
Initial Incomplete Erection
 │
 ▼
Performance Anxiety / Worry
 │
 ▼
Sympathetic Nervous System Activation (Adrenaline Release)
 │
 ▼
Vasoconstriction of Penile Arteries
 │
 ▼
Reduced Blood Flow & Loss of Rigidity
Chronic Stress, Burnout, and Mood
Chronic workplace stress, sleep deprivation, and clinical depression significantly alter neurotransmitter balance. Serotonin, dopamine, and nitric oxide pathways in the brain regulate both libido and physical response. When dopamine levels drop due to chronic burnout, sexual arousal pathways fail to generate strong enough signals to initiate a full erectile response.
Lifestyle and Metabolic Drivers
Subtle changes in daily habits often accumulate over time, gradually dampening erectile strength before any overt medical condition is diagnosed.
Subclinical Cardiovascular Changes: Endothelial cells—the inner lining of blood vessels—produce the nitric oxide required for vasodilation. Early-stage endothelial dysfunction caused by high cholesterol, elevated blood pressure, or a sedentary lifestyle reduces nitric oxide production long before systemic heart disease appears.
Sleep Architecture: Penile tissue relies on nocturnal erections during Rapid Eye Movement (REM) sleep to oxygenate tissue and maintain elasticity. Conditions like obstructive sleep apnea or chronic sleep restriction disrupt REM sleep, starving the tissue of regular oxygenation cycles and dampening morning and situational erections.
Alcohol and Substance Use: While alcohol lowers inhibitions, it acts as a central nervous system depressant and blunts sensory processing. Chronic heavy drinking can also cause peripheral neuropathy and elevate estrogen levels through altered liver metabolism.
A Diagnostic Roadmap: Identifying the Root Cause
Pinpointing why erectile firmness has dropped requires analyzing patterns rather than treating the issue as a single isolated symptom.
Evidence-Based Solutions to Restore Full Rigidity
Addressing partial erectile loss requires a targeted strategy that combines medical evaluation with lifestyle optimization.
 Diagnostic Evaluation
 │
 ┌───────────────────────┴───────────────────────┐
 ▼ ▼
 Physical / Medical Drivers Psychogenic / Behavioral
 │ │
 ┌───────┴───────┐ ┌───────┴───────┐
 ▼ ▼ ▼ ▼
PDE5 Inhibitors Endothelial Health Cognitive Sleep & Stress
(Sildenafil, (Exercise, Diet, Behavioral Optimization
 Tadalafil) Cardio) Therapy (CBT)
1. Medical Evaluation and Diagnostics
Consulting a physician or urologist provides baseline clarity. Essential diagnostic tests include:
Fasting Blood Glucose and HbA1c: To screen for early insulin resistance or prediabetes.
Lipid Panel: To assess cardiovascular health and arterial function.
Total and Free Testosterone: Best measured in the early morning (between 7:00 AM and 10:00 AM) when levels peak.
Blood Pressure Screening: To detect silent hypertension affecting arterial flexibility.
2. First-Line Medical Therapies
PDE5 Inhibitors: Medications such as sildenafil, tadalafil, and vardenafil work by inhibiting the enzyme phosphodiesterase type 5, preventing the breakdown of cyclic GMP (cGMP). This keeps smooth muscles relaxed and allows blood flow to remain unobstructed during arousal. Note that these medications require sexual stimulation to work; they do not automatically trigger an erection.
Hormone Replacement: If lab work confirms hypogonadism (pathologically low testosterone), testosterone replacement therapy (TRT) under medical supervision can restore both libido and night-time erectile frequency.
3. Targeted Lifestyle Adjustments
Zone 2 Cardiovascular Exercise: Engaging in 150–200 minutes per week of moderate aerobic exercise improves systemic endothelial function and increases natural nitric oxide production.
Dietary Optimization: A Mediterranean-style diet rich in polyphenols, nitrates (found in leafy greens and beets), healthy fats, and lean proteins directly supports vascular health.
Targeted Cognitive Behavioral Therapy (CBT): Working with a sex therapist or utilizing CBT techniques helps deconstruct the anxiety-adrenaline loop, shifting focus away from "performing" and back toward sensory awareness.
Conclusion
Experiencing a drop from 100% rigidity down to 70% or 80% is rarely a permanent condition, but it is an early indicator from your body. Because the penile arteries are among the smallest in the vascular system, changes in erectile quality often serve as an early warning system for overall cardiovascular, hormonal, and mental health. By treating this shift as valuable feedback rather than a personal failure, you can take proactive steps—combining medical insight, stress management, and vascular optimization—to fully restore your sexual health and confidence.