To understand why certain beverages can outperform plain water in specific contexts, we must venture deep into the mechanics of human physiology. Hydration is not merely a matter of pouring fluid into the stomach; it is a complex, highly regulated transport challenge involving osmolality, gastric emptying rates, cellular gradients, and precise hormonal signaling. When an athlete collapses from exhaustion after a grueling marathon, or when a child suffers from acute dehydration due to a gastrointestinal bug, handing them a glass of pure, demineralized water can sometimes do more harm than good. In fact, under conditions of severe fluid and electrolyte loss, drinking large volumes of pure water can precipitate a life-threatening condition known as hyponatremia—a perilous dilution of sodium in the bloodstream.
This first part of our comprehensive exploration will deconstruct the physiology of fluid absorption, challenge the simplistic dogmas surrounding daily hydration, and examine the foundational science that dictates how our bodies process different liquids. By the time we trace the path of a fluid molecule from your lips to your bloodstream, you will view a simple glass of fluid not as a passive quencher of thirst, but as an intricate biochemical delivery system.
1. The anatomy of Thirst and the physiology of Fluid balance
Before evaluating which liquids outperform water, we must first define what optimal hydration actually means. The human body is a marvel of aqueous engineering, composed of roughly 55% to 60% water by weight in adult males, and slightly less in adult females due to a higher percentage of adipose tissue. This water is not distributed uniformly; it is compartmentalized into two major domains:
Intracellular Fluid (ICF): Residing inside our trillions of cells, accounting for roughly two-thirds of total body water.
Extracellular Fluid (ECF): Comprising the interstitial fluid bathing our tissues and the intravascular fluid circulating within our blood vessels, making up the remaining one-third.
Maintaining the delicate balance between these compartments is a matter of survival. If water shifts too rapidly out of the blood vessels and into the cells, blood pressure drops, and vital organs risk perfusion failure. Conversely, if cells lose too much water to the extracellular space, they shrink, cellular metabolism stalls, and cognitive function plummets.
The brain monitors this internal ocean with exquisite sensitivity. Located deep within the diencephalon, the hypothalamus houses osmoreceptors—specialized neurons that constantly sample the concentration of solutes in the blood. When you become dehydrated, whether through vigorous exercise, prolonged heat exposure, or simple metabolic processes, the concentration of solutes (such as sodium and chloride) in the blood rises. The blood becomes hypertonic.
The osmoreceptors immediately detect this shift and trigger two simultaneous survival mechanisms:
The Thirst Drive: They send neural signals to the cerebral cortex, generating the conscious sensation of thirst, compelling you to seek out and consume fluids.
Hormonal Conservation: The hypothalamus signals the posterior pituitary gland to release Antidiuretic Hormone (ADH), also known as vasopressin. ADH travels via the bloodstream to the kidneys, instructing them to insert water channels (aquaporins) into the collecting ducts. This allows the kidneys to reabsorb water back into the bloodstream rather than excreting it as urine, resulting in concentrated, dark yellow urine.
Despite these robust mechanisms, our behavioral thirst response is notoriously flawed. Research in exercise physiology demonstrates that humans do not typically feel thirsty until they have already lost approximately 1% to 2% of their body weight in water. By the time you reach for a cup of water, cognitive performance, mood stability, and physical endurance have already begun to degrade. In vulnerable populations, such as the elderly, whose osmoreceptor sensitivity naturally declines with age, or young children engaged in intense play, this thirst reflex can fail entirely, leading to chronic, sub-clinical dehydration.
2. The mechanics of absorption: Why pure water isn't always the fastest
A common misconception is that the moment you swallow a liquid, it is instantly absorbed into your bloodstream to rehydrate your tissues. In reality, fluid absorption is a multi-step journey governed by physics and physiology, taking place primarily in the small intestine rather than the stomach.
When you ingest any beverage, it first enters the stomach, where it undergoes gastric processing. The rate at which the stomach empties its contents into the duodenum (the first section of the small intestine) is known as the gastric emptying rate. Several factors influence this rate:
Volume: Larger volumes in the stomach stretch its walls, accelerating emptying up to a point.
Caloric Density: Liquids packed with complex carbohydrates, fats, or proteins require extensive digestion and slow down gastric emptying, keeping fluids trapped in the stomach longer.
Osmolality: The concentration of dissolved particles (ions, sugars, proteins) in a fluid relative to human blood plasma (which is typically around 280–300 mOsm/kg) plays a monumental role.
Pure water is hypotonic, meaning it has a very low osmolality close to zero. When you chug a large volume of pure water, it empties from the stomach relatively quickly because it requires no enzymatic breakdown. However, once it reaches the small intestine, a fascinating physiological bottleneck occurs.
The intestinal lining cannot absorb water purely through passive bulk flow against osmotic gradients. Water follows solute transport, specifically, the active transport of sodium ions (Na+Na^+Na+) across the intestinal epithelial cells via specialized carrier proteins like the Sodium-Glucose Linked Transporter 1 (SGLT1). As sodium and accompanying glucose molecules are actively pumped out of the intestinal lumen and into the bloodstream, osmotic pressure drops locally, and water molecules are forcibly dragged across the intestinal membrane through tight junctions and aquaporins to maintain equilibrium.
When you drink pure water, there is a deficit of sodium and glucose in the lumen. The body must actually secrete electrolytes from its own extracellular stores into the gut lumen to facilitate optimal absorption, or rely on slower, pressure-driven absorption gradients. Consequently, a portion of pure water sits longer in the gut, can cause sloshing or discomfort if consumed in massive quantities, and is processed by the kidneys for excretion at a surprisingly rapid rate if electrolytes are missing.
3. The Beverage Hydration Index (BHI): Science quantifies Hydration
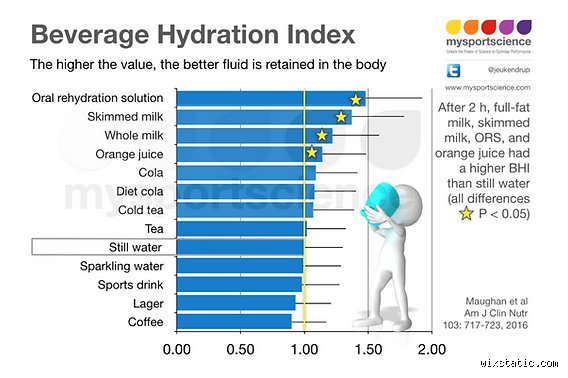
For decades, the superiority of various drinks over water was largely a matter of theoretical sports nutrition or anecdotal athletic lore. However, a landmark study published in the American Journal of Clinical Nutrition by Dr. Ronald Maughan and his colleagues at Loughborough University changed the scientific landscape by introducing the Beverage Hydration Index (BHI).
The BHI was designed to measure how well a given volume of a test beverage is retained in the body compared to plain still water over a specified multi-hour window. In the study, healthy male subjects ingested a standardized 1 liter of plain water or one of several test drinks over a 30-minute period. Researchers then tracked urine output over the subsequent two hours and four hours to calculate net fluid retention.
The results challenged conventional nutritional dogmas. While plain water served as the baseline (index value of 1.0), several common beverages demonstrated significantly higher fluid retention scores:
Oral Rehydration Solutions (ORS): Scored the highest, often retaining fluid up to 30% to 50% more effectively than plain water.
Skim and Full-Fat Milk: Both scored significantly higher than water (roughly 1.15 to 1.25), proving that complex nutrient matrices can enhance fluid retention.
Orange Juice and Sports Drinks: Exhibited high retention profiles due to their balanced osmolar loads.
Tea and Coffee (in moderate amounts): Showed retention profiles remarkably similar to water, debunking the persistent myth that caffeinated beverages possess a net-dehydrating diuretic effect.
Why did milk and oral rehydration solutions outperform plain water? The answer lies in their composition. Milk contains a natural blend of lactose (sugar), whey and casein proteins, sodium, and potassium. This complex biochemical architecture slows gastric emptying, sustains the release of nutrients into the small intestine, and maintains a steady, prolonged SGLT1-mediated transport of water across the intestinal wall. Instead of triggering a sudden spike in urine output, the infamous "drink and run" phenomenon associated with chugging large volumes of pure water, nutrient-dense and electrolyte-balanced fluids allow the body to absorb and retain water gradually over an extended period.
4. Electrolytes: The unsung heroes of cellular osmosis
To fully appreciate why certain liquids hydrate better than water, one must examine the role of electrolytes, specifically sodium, potassium, magnesium, and calcium. These minerals dissociate into charged ions when dissolved in bodily fluids, creating the electrical gradients necessary for nerve impulse propagation, muscle contraction, and fluid balance.
Sodium and potassium operate in a delicate, life-sustaining tango known scientifically as the sodium-potassium pump (Na+/K+−ATPaseNa^+/K^+-ATPaseNa+/K+−ATPase). This membrane-bound enzyme pumps three sodium ions out of the cell for every two potassium ions it pumps in, expending a massive share of the body's resting metabolic energy to maintain intracellular stability.
When we sweat during exercise or lose fluids through illness, we do not just lose water; we lose significant quantities of electrolytes, predominantly sodium and chloride. If an individual attempts to rehydrate solely with pure, unmineralized water, two problems occur:
The Dilution Effect: The extracellular fluid is further diluted, lowering the plasma sodium concentration.
The Renal Switch: The kidneys, sensing a drop in plasma osmolality and perceiving that body fluid is too dilute, immediately halt the production of ADH and ramp up urine output. Your body works frantically to dump the excess pure water to restore homeostatic electrolyte concentrations, leaving you urinating frequently without actually achieving deep cellular hydration.
Liquids that incorporate carefully calibrated ratios of sodium and potassium bypass this renal trap. By matching or approximating the osmolality of human blood plasma (isotonic drinks) or providing a hyper-efficient transport gradient (hypotonic or balanced oral rehydration solutions), these fluids signal to the kidneys that fluid retention is safe and necessary. The sodium molecules anchor the water within the extracellular matrix, while glucose molecules pull both sodium and water across the intestinal epithelium with maximal kinetic efficiency.
5. The myth of diuretic dehydration (Coffee, tea, and alcohol)
No discussion of alternative hydrating liquids is complete without addressing the cultural anxieties surrounding common beverages like coffee, tea, and alcoholic drinks. For generations, office workers and fitness enthusiasts alike have been warned that every cup of coffee or afternoon tea acts as a net negative on hydration status, driving fluid out of the body faster than it enters.
From a pharmacological perspective, caffeine is indeed a mild, transient diuretic. It works by blocking adenosine receptors in the renal vasculature, leading to dilation of the afferent arterioles, an increase in the glomerular filtration rate (GFR), and a temporary inhibition of sodium and water reabsorption in the renal tubules.
However, controlled clinical trials have repeatedly demonstrated that regular consumers of caffeinated beverages develop a rapid tolerance to this diuretic effect. When you drink a cup of coffee or black tea, you are consuming roughly 98% to 99% pure water. The fluid volume delivered by the beverage vastly outweighs the mild, temporary diuretic response triggered by the caffeine content.
A comprehensive review of hydration studies by researchers at the School of Sport, Exercise and Health Sciences at Loughborough University confirmed that when consumed in moderate amounts (equivalent to normal daily dietary habits), caffeinated drinks contribute to total daily water intake just as effectively as plain water. The net fluid balance remains positive.
Alcohol, conversely, is a potent and unambiguous inhibitor of hydration. Ethanol acts directly on the central nervous system to suppress the synthesis and release of Antidiuretic Hormone (ADH) from the posterior pituitary gland. In the absence of ADH, the renal collecting ducts become impermeable to water, preventing reabsorption and leading to a massive surge in the production of dilute, copious urine. This is why a night of drinking leads to profound morning-after dehydration, characterized by splitting headaches, dry mucous membranes, and hemoconcentration. Even so, alternating alcoholic beverages with electrolyte-rich water or broths can mitigate this drastic fluid loss, proving once again that the presence of solutes alters the physiological trajectory of ingested fluids.
Looking ahead: The spectrum of advanced Hydration
As we have established, hydration is far more sophisticated than a simple binary choice between drinking water and being dehydrated. The human body is an intricate biological system tuned to absorb fluids most efficiently when they are delivered with the correct balance of electrolytes, low-to-moderate sugars, and amino acids.
In the second part of this expert analysis, we will transition from foundational physiology to practical application. We will examine specific categories of liquids, ranging from commercial sports drinks and coconut water to oral rehydration solutions, bone broths, and dairy-based beverages, analyzing their precise biochemical profiles, clinical applications, and how you can leverage them to optimize your daily cognitive performance, athletic recovery, and overall cellular health.
It looks like you didn't include the actual questions for Question 2 and Question 3! Please provide the text or topics for both questions, and I will be happy to write the 4-5 sentence paragraphs for you right away.