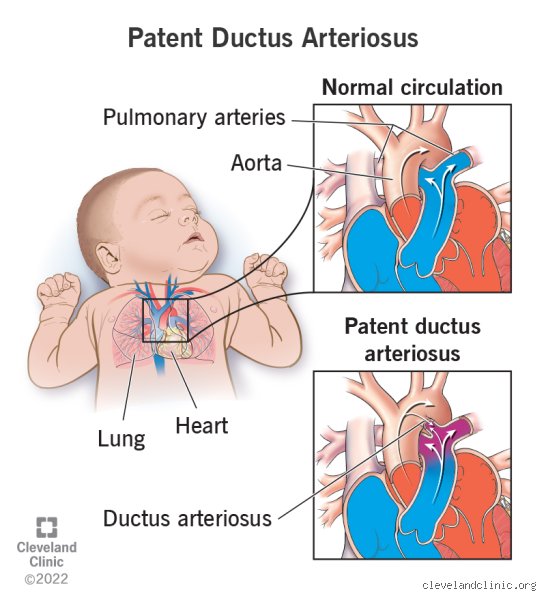
Understanding Patent Ductus Arteriosus (PDA)
In utero, a fetus does not use its lungs to breathe; instead, oxygen and nutrients are supplied directly by the mother via the placenta. Because the fetal lungs are collapsed and filled with fluid, pulmonary vascular resistance is exceptionally high, meaning very little blood needs to flow through the lungs. To bypass this non-functional pulmonary circuit, nature provides a temporary, critical vascular shunt known as the ductus arteriosus. This muscular blood vessel connects two major arteries leaving the heart: the pulmonary artery (which normally carries deoxygenated blood from the right ventricle to the lungs) and the descending aorta (which distributes oxygenated blood to the rest of the body).
During fetal life, approximately 90% of the blood exiting the right ventricle is diverted through the ductus arteriosus directly into the systemic circulation, bypassing the pulmonary bed entirely. This is a brilliant evolutionary design that ensures oxygen-rich blood is prioritized for vital organs such as the brain and heart.
However, at the moment of birth, a dramatic physiological transformation occurs. With the baby's first breath, the lungs expand, filled with oxygen, and pulmonary vascular resistance drops precipitously. Concurrently, the placenta is detached, systemic vascular resistance rises, and arterial oxygen tension increases significantly. In a healthy, full-term newborn, these abrupt biochemical and physical changes trigger the constriction and functional closure of the ductus arteriosus within the first 12 to 24 hours of life, followed by permanent anatomical sealing (fibrosis) over the subsequent weeks, transforming the vessel into a non-functional fibrous remnant known as the ligamentum arteriosum.
When this normal closure mechanism fails, the ductus remains open—or patent. This condition is known as Patent Ductus Arteriosus (PDA). While a PDA is a normal and vital structure before birth, its persistence after birth constitutes a congenital heart defect characterized by abnormal blood flow between the aorta and the pulmonary artery.
Pathophysiology and Hemodynamic consequences
The clinical impact of a patent ductus arteriosus depends almost entirely on two factors: the physical size of the opening (caliber) and the pressure gradient between the aorta and the pulmonary artery.
Because systemic blood pressure (in the aorta) is consistently much higher than pulmonary arterial pressure after birth, an unclosed ductus creates an abnormal channel for blood to flow backward from the systemic circulation into the pulmonary circulation. This phenomenon is known as a left-to-right shunt.
The cascade of volume overload
Pulmonary Hyperemia: As blood shunts from the high-pressure aorta back into the lower-pressure pulmonary artery, a significant volume of blood recirculates through the lungs unnecessarily. This causes overcirculation, or pulmonary hyperemia.
Left-Sided Heart Strain: The extra blood returning from the lungs fills the left atrium and left ventricle with a much higher volume than normal. Over time, this chronic volume overload forces the left side of the heart to work harder, leading to ventricular dilation (enlargement) and hypertrophy (thickening of the heart muscle). In severe cases, this can progress to congestive heart failure.
Pulmonary Hypertension and Vascular Remodeling: If a large PDA is left untreated for an extended period, the persistently high blood flow and elevated pressure within the pulmonary vascular bed can cause structural remodeling of the pulmonary arterioles. The walls of these small vessels thicken, leading to fixed pulmonary hypertension. If pulmonary vascular resistance eventually exceeds systemic resistance, the shunt reverses direction (right-to-left), resulting in unoxygenated blood entering the systemic circulation—a life-threatening condition known as Eisenmenger syndrome.
In premature infants, the consequences can be even more acute. Premature babies already have fragile respiratory systems, and a large PDA can flood the lungs with fluid, worsening respiratory distress syndrome, prolonging the need for mechanical ventilation, and increasing the risk of intraventricular hemorrhage, necrotizing enterocolitis (NEC), and renal dysfunction due to "steal" of blood away from systemic organs during diastole.
Clinical presentation and diagnosis
The clinical presentation of a PDA varies widely depending on the patient's age at diagnosis, the size of the shunt, and whether the patient was born prematurely or at term.
In Preterm Infants: A significant PDA often manifests in the neonatal intensive care unit (NICU) as worsening respiratory support requirements, inability to wean off a ventilator, a hyperactive or "bounding" peripheral pulse, a widened pulse pressure, and clinical signs of congestive heart failure such as tachycardia, hepatomegaly (enlarged liver), and poor feeding.
In Term Infants and Children: Small PDAs may be completely asymptomatic and are frequently discovered incidentally when a physician hears a characteristic continuous "machinery" murmur during a routine physical examination. This classic murmur is audible throughout both systole and diastole because the pressure gradient between the aorta and pulmonary artery persists across the entire cardiac cycle.
In Adults: Undiagnosed or mildly restrictive small-to-moderate PDAs may not present until adulthood, where patients might experience exercise intolerance, palpitations, atrial arrhythmias, or progressive shortness of breath.
Diagnostic Modalities
Confirming the diagnosis and assessing the anatomy of a PDA relies on several non-invasive and invasive diagnostic tools:
Transthoracic Echocardiography (Color Doppler): This is the gold standard for diagnosing a PDA. Echocardiography visualizes the anatomical structure directly, measures the diameter and length of the ductus, evaluates the direction and velocity of blood flow via color Doppler, and assesses the size and function of the left atrium and left ventricle.
Electrocardiogram (ECG): In patients with significant left-to-right shunting, the ECG may reveal signs of left ventricular hypertrophy or left atrial enlargement.
Chest Radiography (X-ray): A chest radiograph can reveal cardiomegaly (enlarged heart shadow, specifically involving the left atrium and ventricle) and increased pulmonary vascular markings (prominent blood vessels in the lungs).
Cardiac Catheterization: While largely replaced by echocardiography for simple diagnosis, cardiac catheterization may still be performed when intervention (such as transcatheter closure) is planned, or when there is a need to accurately measure pulmonary vascular resistance in older patients suspected of developing pulmonary hypertension.
Indications for intervention: Why and when to close a PDA
Not every PDA discovered in early life requires immediate aggressive intervention. In premature infants, a conservative approach with fluid restriction and medical therapy (such as cyclooxygenase inhibitors like ibuprofen or indomethacin) is often attempted first to encourage natural closure. However, when medical management fails, or when the infant experiences significant hemodynamic instability, closure becomes necessary.
For term infants, children, and adults, a patent ductus arteriosus almost always warrants closure. Even if an individual is entirely asymptomatic with a small PDA, closure is strongly recommended for one primary reason: prevention of infective endocarditis.
The turbulent, high-velocity jet of blood flowing through the persistent ductus damages the delicate endothelial lining of the pulmonary artery near the ductal insertion site. This damaged tissue creates an ideal breeding ground for circulating bacteria, predisposing the patient to endarteritis, an infection of the blood vessel wall that carries high morbidity and mortality. Elective closure eliminates the long-term risks of progressive left ventricular volume overload, myocardial dysfunction, and late-onset pulmonary vascular disease.
... Continuing our comprehensive examination of Patent Ductus Arteriosus (PDA), we now turn our focus to the clinical interventions required when medical management is insufficient or contraindicated. When a PDA fails to close naturally and leads to significant clinical complications, such as pulmonary overcirculation, congestive heart failure, or failure to thrive, a corrective procedure becomes necessary. Modern pediatric cardiology and cardiothoracic surgery offer two primary approaches for PDA closure: catheter-based transcatheter closure and surgical ligation.
The interventional options: Catheter-Based Closure vs. Surgical ligation
Selecting the appropriate closure method depends heavily on the patient’s age, weight, anatomical characteristics of the ductus, and overall clinical stability.
1. Transcatheter PDA Closure (Catheter-Based)
For older infants, children, and adults, transcatheter closure is overwhelmingly the gold standard. This minimally invasive technique avoids the need for open-chest surgery, minimizing trauma, scarring, and recovery time.
The Mechanism: A specialized interventional cardiologist guides a thin, flexible catheter through a blood vessel, typically the femoral vein or artery in the groin, up into the heart and directly into the PDA.
Devices Used: Once the catheter reaches the ductus, a tiny, self-expanding device (such as a PDA coil or a specialized nitinol occluder mesh button) is deployed. This device acts as a permanent plug, halting blood flow through the shunt. Over the subsequent weeks, the body's natural endothelial cells grow over the device, permanently sealing the channel.
Advantages: Shorter hospital stays (often outpatient or overnight), absence of a surgical scar, reduced risk of chest wall deformity, and rapid return to normal activities.
2. Surgical Ligation
Surgical ligation is traditionally reserved for premature infants in the neonatal intensive care unit (NICU) whose tiny blood vessels cannot accommodate catheter delivery systems, or for exceptionally large ductal structures where catheter-based devices might pose a risk of embolization or impingement on surrounding major vessels (like the aorta or pulmonary artery).
The Mechanism: Performed by a pediatric cardiothoracic surgeon, this procedure is usually done via a left thoracotomy (an incision between the ribs on the left side of the chest) without opening the heart chambers or requiring cardiopulmonary bypass.
The Technique: The surgeon carefully dissects around the ductus and securely ties it off (ligates it) using permanent surgical sutures or metal clips. In some cases, the ductus is divided entirely (transection) to ensure permanent closure.
Advantages: Highly effective for extremely low birth weight infants (ELBW) where catheter technology cannot safely reach; provides immediate, definitive anatomical closure.
Step-by-Step clinical breakdown of the Procedures
Understanding the perioperative journey can alleviate anxiety for families navigating this diagnosis.
Pre-Procedural Preparation
Before either intervention, a comprehensive diagnostic workup is performed. This typically includes:
Echocardiogram: To visualize the exact size, shape, and hemodynamic impact of the PDA.
Electrocardiogram (ECG): To evaluate heart rhythm and electrical activity.
Chest Radiograph: To assess heart size and the appearance of the lung fields (checking for pulmonary congestion or edema).
Laboratory Testing: Complete blood count, coagulation profiles, and type-and-screen for potential blood products.
Intra-Operative Experience
Anesthesia: Both procedures require general anesthesia to ensure the patient remains completely still and pain-free. For premature infants, specialized neonatal anesthesiologists manage delicate respiratory parameters, as these infants often have chronic lung disease (bronchopulmonary dysplasia).
Monitoring: Continuous arterial blood pressure monitoring, pulse oximetry, and electrocardiographic tracking are maintained throughout. In surgical cases, cerebral near-infrared spectroscopy (NIRS) may be used to monitor brain oxygenation during vascular manipulation.
Immediate Post-Operative Management and recovery
The immediate post-procedural phase requires meticulous nursing and medical oversight, particularly in fragile neonatal populations.
In the recovery unit or NICU/PICU
Hemodynamic Stabilization: Closing a large PDA abruptly alters the workload on the heart. Once the left-to-right shunt is eliminated, the left ventricle no longer has to pump the extra volume of blood returning from the lungs. Blood pressure and heart rate are closely monitored for signs of acute rebound hypertension or transient left ventricular dysfunction.
Respiratory Support: Premature infants frequently require continued ventilator support immediately following surgery as their lungs gradually recover from chronic hyperperfusion. Over subsequent days, ventilator settings are typically weaned as pulmonary edema clears.
Pain Management: While catheter-based procedures involve minimal discomfort (usually managed with mild analgesics like acetaminophen), surgical ligation involves an intercostal incision. Multimodal pain management regimens, including localized nerve blocks or targeted intravenous analgesics, ensure comfort.
Wound Care: For surgical patients, the left lateral chest incision is monitored daily for signs of healing, erythema, or drainage. Sutures or surgical glues used are typically self-absorbing, requiring minimal active maintenance upon discharge.
Potential risks, complications, and risk mitigation
While modern PDA closures are exceptionally safe and routine, every medical intervention carries inherent risks. A thorough risk-benefit analysis is always conducted by the multidisciplinary care team.
Incomplete Closure or Residual Shunt: Occasionally, a tiny channel remains open around a device or clip. Follow-up echocardiography checks for this; many residual shunts spontaneously thrombose and close over time, though minor re-interventions are occasionally warranted.
Device Embolization (Catheter Procedures): Rare instances occur where a closure device shifts from its intended position. Interventional cardiologists are trained to retrieve or reposition stray devices via catheter without needing emergency surgery.
Nerve Injury: During surgical ligation, the recurrent laryngeal nerve, which runs dangerously close to the ductus, can be bruised or stretched, potentially leading to temporary or permanent hoarseness or vocal cord weakness. Surgeons utilize specialized magnification and meticulous dissection techniques to protect this nerve.
Infection: As with any invasive procedure, localized or systemic infection (infective endocarditis) is a risk, mitigated by strict sterile protocols and perioperative prophylactic antibiotics.
Bleeding or Vascular Injury: Damage to the femoral vessels during catheterization or bleeding at the surgical site are managed swiftly by the surgical team.
Long-Term prognosis, Follow-Up Care, and outlook
The long-term outlook for individuals who have undergone successful PDA closure is overwhelmingly positive.
Follow-Up Schedule
Following discharge, patients typically undergo a structured follow-up protocol:
1-Month Post-Op Evaluation: A clinical examination and follow-up echocardiogram to confirm complete closure, normal heart chamber dimensions, and appropriate ventricular function.
Intermediate Milestone Checks: Pediatric patients are often monitored annually or biannually by a pediatric cardiologist to ensure normal cardiovascular growth and development.
Transition to Adult Congenital Heart Disease (ACHD) Care: Patients born with complex congenital heart defects involving a PDA transition into specialized ACHD programs as they reach adulthood. However, isolated PDAs that are successfully closed in infancy or childhood generally require no lifelong dietary or physical activity restrictions once fully healed.
Quality of life and physical activity
Once recovery is complete, typically within a few weeks for catheter interventions and 4 to 6 weeks for surgical healing, children and adults experience a dramatic improvement in energy levels, exercise tolerance, and overall growth trajectories. Infants who previously struggled with feeding and weight gain often experience "catch-up growth," thriving within months of the repair. Adults note a significant reduction in fatigue and shortness of breath.
Conclusion
The evolution of Patent Ductus Arteriosus management stands as a triumph of modern medical engineering and clinical expertise. What once represented a high-risk surgical undertaking is now a refined, highly predictable spectrum of care ranging from targeted pharmacological inhibition to minimally invasive catheter deployment and precise surgical ligation.
Whether navigating the delicate care of a micro-premature infant in the NICU or performing an elective outpatient closure on an older child, the ultimate goal remains uniform: restoring normal, unburdened cardiovascular physiology. Through early diagnosis, sophisticated imaging, and advanced intervention, patients with a PDA can look forward to a healthy, active life unhindered by the burdens of congenital heart disease.