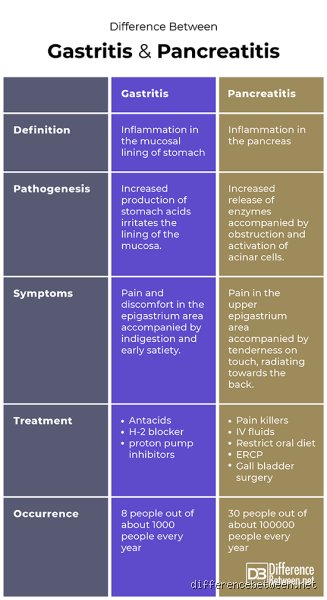
Understanding how to differentiate between these two distinct sources requires a close examination of underlying anatomy, physiological trigger points, and distinct pain patterns. This guide explores the foundational markers that set gastric pain apart from pancreatic distress, equipping you with the knowledge to recognize how each system operates under stress.
Physiological mechanics of upper abdominal discomfort
To grasp why abdominal pain can feel so ambiguous, one must first look at how visceral sensation is transmitted to the brain. Unlike the skin or skeletal muscles, which possess precise, highly localized pain receptors, the internal organs rely on visceral afferent nerves. These nerves are less concentrated and often share spinal pathways with adjacent structures. Consequently, when either the stomach or the pancreas becomes irritated, inflamed, or distended, the brain frequently registers the signal as a broad, diffuse ache across the upper central abdomen, an effect known as referred pain.
Despite this overlapping geography, the two organs have fundamentally different roles in digestion, acid regulation, and systemic metabolism. The stomach serves primarily as a muscular reservoir and chemical mixing bowl, breaking down food via hydrochloric acid and pepsin. The pancreas, by contrast, functions as both an exocrine powerhouse, secreting vital digestive enzymes like lipase, amylase, and protease into the small intestine, and an endocrine organ regulating blood glucose via insulin and glucagon. When dysfunction arises in either site, the resulting discomfort mirrors these specialized physiological duties.
Gastric irritation and mucosal barrier failure
Gastric pain typically originates from the mucosal lining of the stomach. Under normal conditions, a thick layer of mucus and bicarbonate shields the gastric wall from its own corrosive digestive juices. However, when this defensive barrier is compromised by factors such as chronic Helicobacter pylori infection, the overuse of non-steroidal anti-inflammatory drugs (NSAIDs), or excessive acid production, the underlying tissue becomes exposed.
This exposure leads to localized inflammation, gastritis, or peptic ulcer formation. When food enters the stomach or when acid secretion peaks during fasting periods, the exposed nerve endings are stimulated directly by gastric acid. This interaction produces a sharp, burning, or gnawing sensation located typically in the epigastric region (just below the breastbone). Because the stomach expands and contracts with food intake, gastric pain is heavily modulated by eating; it may flare intensely when food touches an ulcer or, conversely, find temporary relief when food buffers stomach acid.
Pancreatic inflammation and enzymatic autodigestion
Pancreatic pain, particularly in conditions like acute or chronic pancreatitis, stems from an entirely different mechanism: intraductal pressure and localized tissue autodigestion. Normally, the pancreas manufactures powerful digestive enzymes in an inactive form, ensuring they do not digest the gland itself. They are safely transported through the pancreatic duct into the duodenum, where they activate.
In pancreatitis, these enzymes activate prematurely while still inside the pancreas. This triggers a destructive inflammatory cascade where the organ begins to digest its own cellular architecture. As inflammation swells the pancreatic tissue, it stretches the tough capsule surrounding the organ, stimulating dense networks of sensory nerve fibers. Simultaneously, the buildup of fluid and edema raises internal pressure within the pancreatic ducts. This creates a deep, boring, unremitting ache that is often far more severe, persistent, and debilitating than typical gastric discomfort.
Neural pathways and referred sensation
The physical architecture of the autonomic nervous system further dictates how these two types of pain travel to the central nervous system. The stomach's sensory fibers feed into the celiac plexus and travel via the greater splanchnic nerves to the spinal cord segments T5 through T9. The pancreas shares a remarkably similar neural highway, utilizing the celiac plexus and splanchnic nerves spanning T6 through T10.
Because these neural inputs converge on overlapping segments of the spinal cord, the brain struggles to isolate the exact origin. This shared wiring explains why both conditions can cause upper abdominal tenderness, nausea, and autonomic responses like sweating or a racing pulse. However, subtle differences in how the pancreas is anchored, retroperitoneally, sitting deep behind the stomach against the posterior abdominal wall, account for why pancreatic pain so frequently radiates straight through to the back, a characteristic feature rarely seen in simple gastric ulcers.
Understanding the subtle differences between discomfort originating from the stomach and distress rising from the pancreas requires a careful look at how these distinct organs behave. When evaluating upper abdominal discomfort, recognizing the precise nature of the distress can help individuals communicate more effectively with healthcare professionals.
Anatomical proximity and overlapping signals
The anatomical positioning of these digestive components creates a diagnostic puzzle. The stomach sits in the upper left portion of the abdomen, acting as a primary reservoir and mixing chamber for food. Immediately behind the stomach lies the pancreas, an elongated gland that stretches horizontally across the back wall of the abdominal cavity. Because the pancreas rests in such close proximity to the stomach and major nerve networks, pain signals from pancreatic inflammation often project forward, mimicking severe gastric upset, gastritis, or peptic ulcer disease.
Despite this physical overlap, their underlying functions differ significantly. The stomach relies on strong muscular contractions and powerful acids to break down food mechanically and chemically. The pancreas, meanwhile, functions as both an exocrine and endocrine powerhouse. It secretes vital digestive enzymes into the small intestine while releasing hormones such as insulin directly into the bloodstream. When either organ becomes distressed, the resulting symptoms can feel alarmingly similar, yet their clinical implications diverge sharply.
Characterizing gastric distress
Discomfort originating directly from the stomach typically links closely with digestive timing and dietary intake. Conditions such as simple indigestion, acid reflux, or gastric ulcers often produce a burning sensation behind the breastbone or a gnawing ache in the upper central abdomen. This type of discomfort frequently fluctuates depending on what and when a person eats. For instance, acid-related pain may flare up shortly after consuming spicy, acidic, or fatty meals, or conversely, it might temporarily improve when food enters the stomach to buffer stomach acids.
Gastric discomfort is also frequently accompanied by localized symptoms such as bloating, excessive burping, a sour taste in the mouth, or mild nausea. While these symptoms can be intensely uncomfortable, they generally develop gradually and respond predictably to over-the-counter antacids, acid reducers, or simple dietary adjustments. If a gastric ulcer is present, the pain may follow a cyclical pattern, appearing when the stomach is empty and fading temporarily after eating.
Identifying pancreatic warning signs
In contrast, distress stemming from the pancreas, such as acute or chronic pancreatitis, tends to present with a much more intense and unyielding profile. Pancreatic pain characteristically arises in the upper middle abdomen and bores straight through to the back. Unlike typical stomach aches that might shift or ease with a change in posture or an antacid tablet, pancreatic pain is notoriously persistent. It often forces individuals to find temporary relief by curling into a fetal position or leaning forward, which helps reduce pressure on the inflamed retroperitoneal space.
The onset of pancreatic distress can be shockingly abrupt, escalating quickly into a severe, constant ache that resists ordinary home remedies. This deep, penetrating discomfort is frequently accompanied by systemic warning signs that rarely accompany simple indigestion, including repeated vomiting, fever, rapid pulse, and profound abdominal tenderness when touched. Chronic pancreatic issues may also manifest over time through subtle indicators such as unexpected weight loss, fatigue, or oily, pale stools that signal a failure to properly digest dietary fats.
Diagnostic pathways and clinical evaluation
Because physical sensations alone cannot definitively isolate the source of upper abdominal distress, medical providers rely on targeted diagnostic tools. Blood tests measuring specific pancreatic enzymes, such as amylase and lipase, can reveal whether the pancreas is actively inflamed. Imaging studies, including abdominal ultrasounds or computerized tomography (CT) scans, offer detailed views of internal structures, allowing clinicians to visualize swelling, scarring, or gallstones that might be blocking pancreatic ducts. Meanwhile, specialized procedures like a gastroscopy can inspect the internal lining of the stomach if a gastric ulcer or localized inflammation is suspected.
Navigating upper abdominal discomfort safely involves paying close attention to persistent or worsening patterns. While minor dietary indiscretions account for many routine bouts of indigestion, sudden, severe, or unyielding pain that radiates toward the back warrants immediate medical evaluation. Recognizing the distinct behavioral patterns of these neighboring organs empowers individuals to seek prompt, appropriate care when serious health concerns arise.
How to distinguish pancreatitis from common abdominal pain?
This video provides a helpful visual overview of the key clinical differences and warning signs that set pancreatic pain apart from general abdominal discomfort.