Understanding the Structure
Building a strong gerund opener requires pairing your -ing word with a clear singular verb later in the clause. Because an action or activity counts as a single concept, the main verb must always agree with a singular subject, even if the gerund phrase contains plural nouns.
Reading classic novels expands your vocabulary faster than memorizing flashcards ever could. Notice how the word reading acts as the noun that performs the action of expanding. Even if you expand the phrase to say that reading complex nineteenth-century novels builds patience, the core verb remains singular.
Avoiding the dangling modifier trap
Confusing a gerund with a participle is the most common pitfall when opening sentences with -ing words. While a gerund acts as the noun doing the action, a participle acts as an adjective describing a noun that must appear immediately after the introductory comma. If you write a phrase like running down the street, you have created a participial phrase that demands a runner right after the comma, whereas using a gerund requires no comma at all because it is the actual subject of the sentence.
Running down the street clears my head after a long day at school.
Varying your sentence rhythm
Relying too heavily on standard subject-verb-object patterns can make an essay feel repetitive and mechanical. Dropping a gerund at the start of a paragraph or following a short, punchy statement resets the cadence of your prose and keeps the reader engaged.
Practical examples in action
Learning a new instrument demands daily patience and a willingness to sound terrible for the first few months. Cooking without a recipe teaches you how flavors balance each other far better than blindly following measurements. Listening actively during a heated debate often reveals the exact flaw in your opponent's logic without you having to raise your voice.
Experimenting with these openers in your next draft will naturally elevate your sentence variety and give your arguments a more authoritative, active tone.
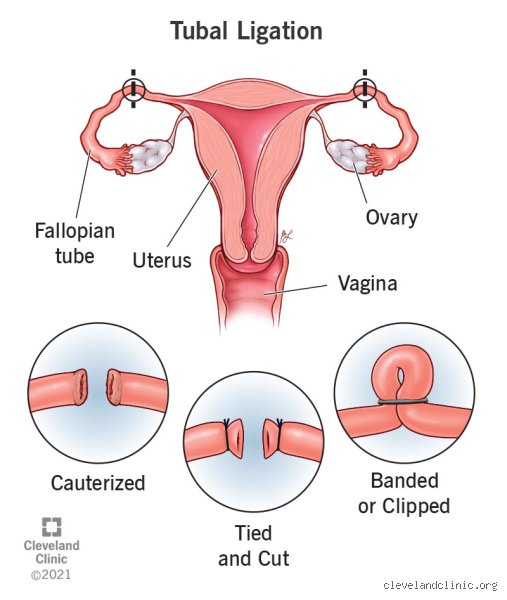
Determining whether a woman has undergone tubal ligation (commonly referred to as having one's "tubes tied") requires an understanding of medical history, surgical anatomy, and clinical diagnostics. Because the procedure takes place entirely internally within the pelvic cavity, it is impossible to detect through outward physical appearance, behavior, or casual observation.
Below is the continuation and comprehensive conclusion of an expert medical guide examining how surgical sterilization is medically verified, the physical realities of the procedure, and why physical signs are virtually undetectable to anyone other than a qualified healthcare provider reviewing medical records.
Diagnostic realities: Why external observation is impossible
A common misconception is that tubal ligation leaves visible external markers, behavioral shifts, or hormonal changes. From a physiological standpoint, this is incorrect for several reasons:
Hormonal Continuity: Tubal ligation involves the Fallopian tubes—the muscular pathways connecting the ovaries to the uterus—rather than the ovaries themselves. Because the ovaries remain completely intact and functional, they continue to produce estrogen and progesterone normally. Consequently, a woman's menstrual cycle, hormonal balance, secondary sex characteristics, and libido remain unaffected.
Internal Anatomy: The surgical interventions (such as cutting, tying, clipping, or cauterizing the Fallopian tubes) occur deep within the pelvic peritoneal cavity. There are no external anatomical alterations that signal the procedure has taken place.
Clinical methods for verifying tubal ligation
When medical verification is necessary, such as for evaluating pelvic pain, investigating post-sterilization pregnancy, or confirming surgical history when records are missing, physicians rely on specific diagnostic modalities:
1. Surgical and medical record review
The gold standard for confirming a tubal ligation is examining the operative report from the original procedure. This document details the exact technique used (e.g., Pomeroy method, Filshie clips, Yoon rings, or bipolar coagulation) and confirms that both tubes were successfully occluded or removed (salpingectomy).
2. Pelvic imaging techniques
While standard ultrasound may not always clearly visualize tiny clips or the exact state of the Fallopian tubes unless specialized high-resolution transvaginal sonography is used, other imaging modalities can offer clues:
Hysterosalpingogram (HSG): A specialized fluoroscopic x-ray procedure where a radiopaque contrast dye is injected through the cervix into the uterus. If the dye flows freely into the peritoneal cavity, the tubes are open; if the dye is blocked near the uterine cornua, tubal occlusion is confirmed.
Laparoscopy: A direct, minimally invasive surgical inspection of the pelvic organs using a laparoscope inserted through a small abdominal incision. This provides direct visual confirmation of the tubes' status.
Surgical scars and physical healing
In modern medicine, most tubal ligations are performed via laparoscopy. This approach typically involves one or two tiny incisions (often less than a centimeter in length) near the bellybutton or lower abdomen.
Fading Over Time: Surgical incisions from laparoscopy heal rapidly and often fade into nearly invisible fine lines within months or years, making them extremely difficult to identify without targeted medical knowledge.
Minilaparotomy: In cases performed shortly after childbirth (postpartum minilaparotomy), a small transverse incision is made just above the pubic hairline. While this leaves a minor scar, it is indistinguishable from scars left by other common pelvic surgeries, such as a low-transverse Cesarean section.
Summary and clinical takeaway
Determining if a woman has had her tubes tied cannot be done through guesswork, physical inspection, or casual observation. The procedure leaves no external footprint, alters no hormonal pathways, and produces no outward physical traits. Definitive verification relies exclusively on documented surgical history, specialized diagnostic imaging like a hysterosalpingogram, or direct visualization via pelvic surgery.