Unraveling the silent threat within
Cardiovascular disease remains the leading cause of death globally, and elevated cholesterol levels are a primary driving force behind this statistical reality. However, cholesterol itself is not inherently evil. In fact, it is a vital lipid molecule that every cell in the human body requires to function correctly. It serves as a building block for cell membranes, aids in the production of vital hormones such as estrogen, testosterone, and cortisol, and assists the body in synthesizing vitamin D. The danger does not lie in the presence of cholesterol, but rather in its imbalance, accumulation, and interaction with the arterial walls.
When we speak of the "main danger" of high cholesterol, we are ultimately pointing toward the progressive narrowing, hardening, and ultimate blockage of vital arteries—a pathological process known scientifically as atherosclerosis. This phenomenon transforms a flexible, elastic highway system of blood vessels into rigid, plaque-choked pipelines. As we dig into the mechanics of how this occurs, why certain types of cholesterol pose vastly different threats, and how the body responds to this cellular buildup, the true magnitude of the risk becomes starkly clear.
The core culprit: Understanding lipoproteins and the LDL threat
To understand why high cholesterol is dangerous, one must understand how cholesterol travels. Because cholesterol is fat-soluble and blood is primarily water-based, it cannot circulate freely through the bloodstream on its own. Instead, the body packages cholesterol and triglycerides into specialized transport vehicles called lipoproteins.
There are two primary categories of lipoproteins that doctors monitor:
Low-Density Lipoprotein (LDL): Commonly referred to as "bad" cholesterol. LDL is responsible for carrying cholesterol particles from the liver to the cells that need them throughout the body.
High-Density Lipoprotein (HDL): Commonly referred to as "good" cholesterol. HDL acts as a scavenger, picking up excess cholesterol from the tissues and blood vessels and transporting it back to the liver to be broken down and eliminated from the body.
The fundamental danger of high cholesterol stems almost entirely from an excess of LDL particles. When there is more LDL circulating in the bloodstream than the cells can utilize, these particles begin to linger in the plasma. This surplus sets the stage for a destructive biological cascade.
Unlike HDL, which actively clears lipid debris, small and dense LDL particles are prone to slipping beneath the innermost lining of the arteries—a single layer of cells called the endothelium. Once trapped beneath this endothelial barrier, these particles do not simply sit harmlessly; they initiate a complex inflammatory and immune response that forms the foundation of atherosclerotic plaque.
The pathological cascade: How atherosclerosis develops
The process by which high cholesterol transforms into a life-threatening danger is a multi-step pathological journey. It begins with endothelial dysfunction. The endothelium acts as a protective guardian of the blood vessels, regulating vascular tone and preventing unwanted cellular adhesion. However, chronically high levels of LDL cholesterol, combined with other risk factors such as high blood pressure, smoking, or elevated blood sugar, can damage or irritate this delicate lining.
Once the endothelium is compromised, the trapped LDL particles beneath it undergo a chemical transformation known as oxidation. Oxidized LDL is recognized by the body's immune system as a foreign invader or cellular debris. In response, specialized white blood cells called monocytes migrate from the bloodstream into the arterial wall, transforming into aggressive scavengers known as macrophages.
These macrophages attempt to engulf and neutralize the oxidized LDL particles by consuming them. However, because there is an overwhelming surplus of trapped cholesterol, the macrophages gorge themselves on lipids until they become engorged, swollen, and dysfunctional. These lipid-laden cells eventually die and rupture, accumulating into a fatty, yellowish mass known as a "foam cell" collection. This marks the earliest visible stage of atherosclerosis, often referred to by pathologists as a "fatty streak."
Over time, this process repeats continuously. Smooth muscle cells migrate from the middle layer of the arterial wall to cap off the accumulating mass of lipids, creating a fibrous scar tissue barrier. This results in the formation of a mature atherosclerotic plaque. As the plaque grows, it physically encroaches upon the lumen, the hollow interior of the blood vessel, restricting the smooth, unimpeded flow of oxygen-rich blood to vital organs.
The domino effect: Systemic vulnerabilities and organ impact
As atherosclerotic plaques expand throughout the arterial tree, the danger of high cholesterol ceases to be a localized vascular issue and becomes a systemic threat to nearly every major organ system. The cardiovascular system relies on a vast, interconnected network of blood vessels to deliver nutrients and oxygen, and when critical arteries become choked with plaque, the downstream consequences are severe.
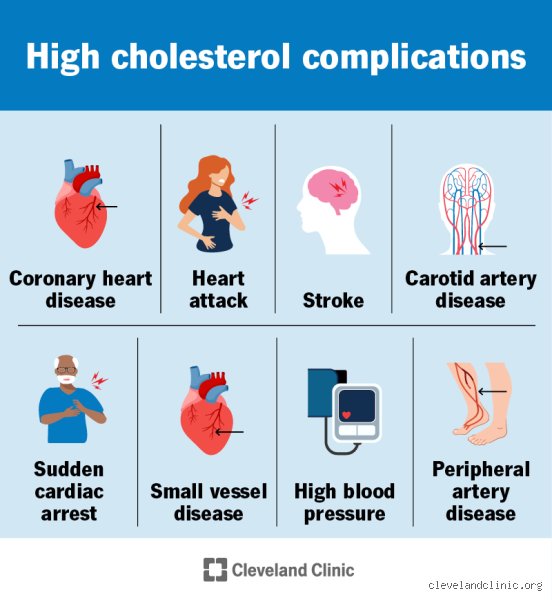
Coronary arteries and heart Disease
The heart muscle itself requires a constant, dedicated supply of oxygenated blood, which it receives via the coronary arteries. When high cholesterol causes plaque buildup in these specific vessels, it restricts blood flow during periods of exertion or stress. This condition, known as coronary artery disease (CAD), can manifest as angina, a crushing or squeezing chest pain that signals the heart muscle is starving for oxygen. If a plaque ruptures completely, it can trigger a sudden blood clot that entirely occludes the coronary artery, cutting off blood supply and causing a myocardial infarction, commonly known as a heart attack.
Cerebral circulation and stroke
The brain is similarly vulnerable to the systemic effects of dyslipidemia. The carotid arteries, which run up both sides of the neck to deliver blood to the brain, can also develop atherosclerotic plaques. If a piece of plaque breaks loose, or if a clot forms over a narrowed section, it can travel upward and block blood flow to a region of the brain. This results in an ischemic stroke, potentially causing permanent neurological damage, loss of motor function, cognitive impairment, or death.
Peripheral Artery Disease (PAD)
High cholesterol also threatens the extremities. Peripheral Artery Disease occurs when plaque builds up in the arteries supplying blood to the legs, feet, arms, or pelvis. Individuals suffering from PAD often experience painful cramping in their calves during walking or exercise, a condition called claudication. In severe cases, reduced blood flow can lead to non-healing ulcers, tissue death, and ultimately the risk of amputation.
The insidious nature of asymptomatic progression
Perhaps the most terrifying aspect of high cholesterol as a primary health hazard is its complete lack of early warning signs. Unlike high blood pressure, which can sometimes cause headaches or nosebleeds, or diabetes, which presents clear symptoms like excessive thirst and fatigue, pure hypercholesterolemia is entirely silent.
A person can maintain dangerously high LDL cholesterol levels for decades without experiencing a single day of feeling unwell. They can run marathons, climb stairs with ease, and pass routine physical examinations while their arteries are slowly undergoing the silent transformation of plaque accumulation. Because there is no physical pain, shortness of breath, or visible alteration in appearance during the early and middle stages of atherosclerosis, individuals have no intrinsic biological cue warning them of impending danger.
This asymptomatic nature breeds a dangerous sense of complacency. Millions of adults skip routine lipid panels because they "feel fine," entirely unaware that microscopic inflammatory processes and lipid deposits are quietly narrowing their vascular pathways. By the time symptoms do manifest, such as the sudden onset of chest pain, a transient ischemic attack (mini-stroke), or acute cardiac distress, the disease is often in an advanced, highly dangerous stage, requiring aggressive medical intervention or emergency surgical procedures.
The cellular cascade of atherogenesis
To fully comprehend the true danger of high cholesterol, one must look past the macroscopic view of clogged pipes and examine the microscopic battlefield within the arterial wall. Atherosclerosis is not merely a passive accumulation of sludge; it is a chronic, dynamic inflammatory disease orchestrated by the immune system in response to lipid retention.
When circulating low-density lipoprotein (LDL) particles, particularly small, dense LDL subclasses, elevate in concentration, the probability of these particles infiltrating the subendothelial space of the arterial intima increases significantly. Once trapped within the intima, these lipoproteins encounter reactive oxygen species (ROS) and enzymatic modifications, leading to oxidation. Oxidized LDL (oxLDL) acts as a biochemical alarm signal, inducing endothelial cells to express adhesion molecules such as vascular cell adhesion molecule-1 (VCAM-1) and intercellular adhesion molecule-1 (ICAM-1).
These adhesion molecules recruit circulating monocytes from the bloodstream, drawing them into the arterial wall where they differentiate into macrophages. Driven by an insatiable appetite for the modified lipoproteins, these macrophages voraciously engulf oxLDL via scavenger receptors (such as SR-A and CD36). As they ingest more and more lipid droplets, their cytoplasm becomes engorged, transforming them into distinctive "foam cells." The accumulation of these foam cells creates the earliest visible lesion of atherosclerosis: the fatty streak.
Crucially, this phase is largely asymptomatic. For decades, the body attempts to wall off these lipid deposits by recruiting smooth muscle cells from the media layer to form a protective fibrous cap composed of extracellular matrix proteins like collagen. This transforms the early fatty streak into a mature fibrofatty plaque. While a thick, fibrous cap containing stable smooth muscle cells and minimal inflammatory cells tends to remain quiescent, the ongoing presence of high cholesterol fuels a smoldering inflammatory fire beneath the surface.
The critical threshold: Plaque vulnerability versus luminal stenosis
One of the most persistent misconceptions in cardiovascular medicine is that the danger of high cholesterol is directly proportional to the degree of luminal narrowing (stenosis) it causes. Clinicians and patients alike often assume that an artery must be 70% or 90% blocked to trigger a cardiac event. However, contemporary pathology reveals a more insidious reality: the vast majority of acute myocardial infarctions and ischemic strokes do not arise from severely stenotic, stable plaques. Instead, they originate from mild to moderate stenotic lesions that are structurally unstable, the so-called "vulnerable plaque."
A vulnerable plaque is characterized by:
An expansive necrotic core rich in extracellular lipids, cholesterol crystals, and apoptotic debris.
A thin, fragile fibrous cap heavily infiltrated by activated macrophages and T-lymphocytes.
A scarcity of smooth muscle cells, which impairs the tissue's ability to repair and maintain structural integrity.
Extensive intraplaque hemorrhage driven by fragile, leaky microvessels (vasa vasorum) proliferating within the plaque structure.
High cholesterol levels, particularly when coupled with systemic inflammation, accelerate the expansion of the necrotic core and stimulate macrophages to secrete matrix metalloproteinases (MMPs). These enzymes degrade the collagen fibers forming the fibrous cap, thinning it until it can no longer withstand the mechanical stress of arterial pulsatile pressure. When the cap ruptures or undergoes surface erosion, the highly thrombogenic necrotic core is abruptly exposed to circulating blood platelets and coagulation factors. This triggers an immediate, catastrophic clotting cascade, culminating in acute luminal thrombosis that completely occludes the vessel and cuts off oxygen supply to downstream tissues. Thus, the ultimate danger of high cholesterol is its capacity to silently construct ticking time bombs within the vascular tree, long before any physical obstruction slows blood flow.
Little-Known aspect: Microvascular Disease and cognitive decline
While the public consciousness firmly links high cholesterol to macrovascular catastrophes like heart attacks and strokes, its subtle, systemic devastation of the microvasculature remains an underappreciated frontier in medical science. The danger extends far beyond the coronary and carotid arteries, infiltrating capillary beds throughout the body.
In the brain, chronic dyslipidemia contributes significantly to cerebral small vessel disease. Excess cholesterol and associated inflammatory signaling alter the permeability and structural integrity of the blood-brain barrier. Over time, this leads to white matter hyperintensities, lacunar infarcts, and chronic cerebral hypoperfusion. Epidemiological and pathological studies increasingly connect long-term exposure to elevated non-HDL cholesterol with an increased risk of vascular dementia and cognitive decline. Because the brain relies on an uninterrupted microvascular supply for optimal synaptic function, the cumulative toll of high cholesterol manifests not only as sudden stroke, but as a slow, progressive erosion of executive function, memory, and neurocognitive resilience.
Similarly, in the kidneys, chronic exposure to dyslipidemia accelerates glomerulosclerosis and interstitial fibrosis. The renal microvasculature suffers progressive endothelial dysfunction, reducing the kidney's filtration efficiency and accelerating the progression of chronic kidney disease (CKD). This creates a vicious cycle: as renal function declines, systemic inflammation and lipid metabolism abnormalities worsen, further amplifying cardiovascular risk.
Reevaluating conventional risk metrics
As our understanding of lipidology has evolved, the clinical community has shifted away from relying exclusively on a simplistic total cholesterol or standard LDL-C reading. While these traditional markers remain valuable baseline indicators, they often mask the true individual risk profile.
The contemporary synthesis of cardiovascular risk integrates advanced lipid subfractionation and particle counting. Two individuals may share an identical LDL-C concentration of 130 mg/dL, yet possess vastly different risk profiles:
Patient A may have large, buoyant, cholesterol-replete LDL particles (Pattern A), which have a lower propensity to penetrate the arterial intima.
Patient B may possess a high concentration of small, dense LDL particles (Pattern B), which easily cross the endothelial barrier, undergo rapid oxidation, and drive aggressive atherogenesis.
Consequently, advanced markers such as Apolipoprotein B (ApoB), which measures the total count of atherogenic, apoB-containing particles (including LDL, VLDL, IDL, and lipoprotein(a)), provide a far more accurate quantification of arterial risk. Evaluating remnant cholesterol (the cholesterol content within triglyceride-rich lipoproteins) highlights another independent driver of residual cardiovascular risk. High cholesterol is not a monolithic entity; it is a heterogeneous spectrum of lipid particles whose structural behavior, electrical charge, and inflammatory potential dictate the true velocity of vascular decay.
Conclusion and Final Verdict
The overarching danger of high cholesterol is its deceptive camouflage. Operating silently and incrementally over decades, it subverts normal vascular biology, transforming vital conduits of life into brittle, inflamed landscapes prone to sudden rupture. It is a pathology defined not by immediate pain or obvious functional loss in its early stages, but by its capacity to accumulate irreversible damage until a critical threshold is crossed.
By shifting our perspective from mere luminal blockage to the complex cellular biology of plaque vulnerability, microvascular degradation, and particle-level atherogenicity, we uncover the true gravity of dyslipidemia. Recognizing that high cholesterol is an active, inflammatory driver of systemic vascular disease, rather than a passive plumbing issue, underscores the critical importance of early, precise risk stratification and comprehensive metabolic stewardship.
Final Verdict: The ultimate peril of high cholesterol lies in its insidious latency. It is a silent architect of cardiovascular and cerebral decline, whose primary danger is realized only when stable protection gives way to catastrophic acute events. Addressing this threat requires looking beyond rudimentary lipid panels to understand the intricate inflammatory and structural dynamics operating within the arterial wall.