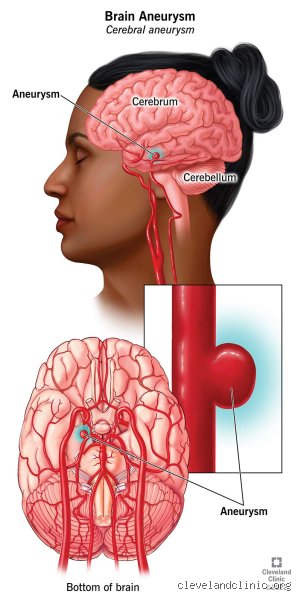
<h1>The Ticking Clock Beneath Your Skull: Exactly How Long Does It Take for an Aneurysm to Burst?</h1> <p>How long does it take for an aneurysm to burst? The unsettling truth is that an unruptured brain aneurysm can rupture anywhere from within seconds of its formation to never at all, as many remain stable over a lifetime. While medical science can estimate rupture risks based on size, location, and shape, predicting the exact timeframe of a rupture remains one of neurology’s most elusive mysteries. If you or someone you care about is living with this silent vascular ticking time bomb, understanding the unpredictable timeline between formation and catastrophe is essential for navigating your next steps with absolute clarity.</p> <h2>Deconstructing the Silent Threat: What an Aneurysm Actually Is</h2> <p>To understand the precarious timeline of a cerebral aneurysm, we first have to look at what is happening inside the delicate architecture of your cerebrovascular system. We tend to visualize our blood vessels as rigid, enduring plumbing, but they are living, dynamic tissues constantly adapting to hemodynamic stress.</p> <p>When an aneurysm forms, a localized section of an artery wall weakens, thins, and begins to balloon outward under the relentless pressure of pulsating blood flow. This structural failure typically occurs at the branching points of major cerebral arteries—most notably along the Circle of Willis at the base of the brain—where blood turbulence is highest.</p> <h3>The Anatomy of Vascular Weakening</h3> <p>The inner lining of an artery (the intima) and the muscular middle layer (the media) begin to degrade. Over time, collagen and elastin fibers break down, leaving only a fragile, stretched pouch composed largely of adventitia and scar tissue. This pouch has no muscular support, meaning it cannot contract or regulate blood pressure locally.</p> <p>Here is where conventional medical literature often oversimplifies the narrative. We are told that aneurysms grow steadily larger like a balloon being blown up with air until the rubber simply gives out. But honestly, it is unclear whether gradual stretching is the primary pathway to a rupture. Many catastrophic bleeds occur in small, stable-looking aneurysms that never showed signs of progressive enlargement, baffling even the most seasoned neurosurgeons.</p> <h3>Why Experts Disagree on the Growth-to-Rupture Timeline</h3> <p>You might assume that bigger always means more dangerous, and therefore a fast-growing aneurysm is practically guaranteed to burst within a predictable window. Yet, vascular specialists fiercely debate this correlation. Some clinical models suggest that an aneurysm must reach a critical threshold—typically 7 millimeters or greater—before the risk of rupture spikes dramatically. </p> <p>However, reality frequently mocks our statistical models. We see patients with massive, multi-lobed aneurysms that remain completely silent for decades, while others experience a devastating subarachnoid hemorrhage from a tiny, 3-millimeter outpouching that formed only months prior. This variance introduces a subtle, haunting irony into modern neurovascular medicine: the more advanced our imaging technology becomes, the better we are at discovering these incidental lesions, yet the less certain we feel about when—or if—they will actually tear open.</p>
The Timeline of Growth vs. Sudden Expansion: Why Progression Varies
When examining the natural history of vascular anomalies—whether intracranial or aortic—clinicians frequently encounter a profound paradox: while some aneurysms remain indolent and stable over decades, others undergo rapid, catastrophic structural failure in a matter of months or even days. Understanding the exact timeframe from formation to rupture requires moving past a single, generalized clock and examining the biological dynamics driving vessel wall degradation.
In typical clinical scenarios, unruptured intracranial aneurysms (UIAs) grow at a remarkably slow rate, often estimated between 1 to 2 millimeters per year, though many remain completely static for a patient's entire lifetime. Longitudinal studies evaluating patient cohorts reveal that it can take anywhere from 10 to 30 years for a small, newly formed vascular pouch to reach a critical threshold size (such as 7 to 10 millimeters) where the risk profile sharply escalates. However, this gradual trajectory is not guaranteed.
Factors such as localized hemodynamic stress—the continuous physical pounding of blood flow against a weakened arterial bifurcation—can trigger micro-tears within the tunica intima and media layers. When these structural layers fail to repair themselves or when chronic inflammation sets in, the aneurysm transitions from steady, slow remodeling into an accelerated expansion phase. Sudden morphological changes, such as the formation of a daughter sac (a secondary bulge on the primary aneurysm), drastically shorten the timeline toward rupture, turning a chronic, monitored condition into an acute medical emergency.
Critical Catalysts: What Accelerates the Path to Rupture?
To evaluate how quickly an aneurysm might progress to the bursting point, physicians look far beyond baseline calendar time. Instead, they rely on multifactorial predictive frameworks that weigh hemodynamic forces against patient-specific vulnerabilities.
The following table outlines the primary variables that dictate whether an aneurysm will remain stable or accelerate toward rupture:
When multiple high-risk indicators converge, the timeline compresses dramatically. For instance, an actively smoking patient with uncontrolled hypertension who harbors a lobulated, 12-millimeter posterior circulation aneurysm faces a cumulative annual rupture risk that can exceed 10% to 20%, meaning a structural failure could occur within months rather than decades.
Silent Expansion to Acute Emergency: Warning Signs and the Window for Intervention
One of the most dangerous aspects of aneurysm progression is its largely asymptomatic nature. Because blood vessels lack somatic pain fibers inside the brain and deep within the torso, an aneurysm can grow, thin, and approach the brink of rupture without triggering a single physical warning.
However, prior to a complete, full-thickness wall blowout, many patients experience what clinicians term a sentient leak or warning symptoms caused by localized micro-fractures, rapid localized stretching, or minor sentinel hemorrhages:
The "Thunderclap" Headache: For cerebral aneurysms, a sudden, agonizing headache—frequently described by survivors as "the worst headache of my life"—can signal a sentinel bleed or micro-rupture occurring days before a catastrophic stroke.
Focal Neurological Deficits: Pressure from an expanding intracranial sac can compress adjacent cranial nerves, resulting in sudden double vision, a drooping eyelid (ptosis), or numbness in the face.
Localized Deep Discomfort: For abdominal or thoracic aortic aneurysms, patients may notice a dull, persistent, or throbbing ache in the lower back, abdomen, or chest that worsens with physical exertion or changes in posture.
Recognizing these symptoms provides a narrow, life-saving window for intervention. Emergency imaging via computed tomography angiography (CTA) or magnetic resonance angiography (MRA) allows neurosurgeons and vascular specialists to visualize the imminent failure site and deploy immediate surgical clipping, endovascular coiling, or stent-graft placement before total rupture occurs.
Modern Management and Predictive Prognostics: Shifting from Observation to Prevention
Because predicting the exact day or month an aneurysm will burst remains an imperfect science, modern clinical medicine has transitioned from passive waiting to proactive mathematical modeling. Tools like the PHASES score (which factors in Population, Hypertension, Age, Size, Earlier subarachnoid hemorrhage, and Site) empower physicians to calculate a patient-specific 5-year rupture risk with high statistical precision.
When the calculated risk of rupture outweighs the inherent risks of elective surgical or endovascular repair, intervention is recommended immediately, neutralizing the threat before the timeline runs out. For smaller, low-risk aneurysms kept under active surveillance, serial imaging every 6 to 12 months ensures that the moment a vessel begins deviating from its stable growth curve, the medical strategy can pivot decisively toward treatment.
Have you or someone you know recently received an aneurysm diagnosis, and are you currently navigating decisions regarding active monitoring versus surgical intervention?