The central question capturing the imagination of researchers, clinicians, and health-conscious individuals alike is whether structured fasting protocols can genuinely "reset" the pancreas. To evaluate this hypothesis with scientific rigor, one must look far beyond superficial weight loss metrics or short-term glycemic fluctuations. We must examine the intricate molecular biology, cellular plasticity, and regenerative capacity of pancreatic tissue when subjected to periodic absence of exogenous nutrients. This comprehensive inquiry requires a deep dive into the cellular kinetics of beta-cell preservation, the mitigation of lipotoxicity, the attenuation of chronic low-grade inflammation, and the induction of ancient autophagic clearance mechanisms that clear cellular debris and restore optimal metabolic functioning.
The dual nature of the pancreas: Exocrine workload and endocrine vulnerability
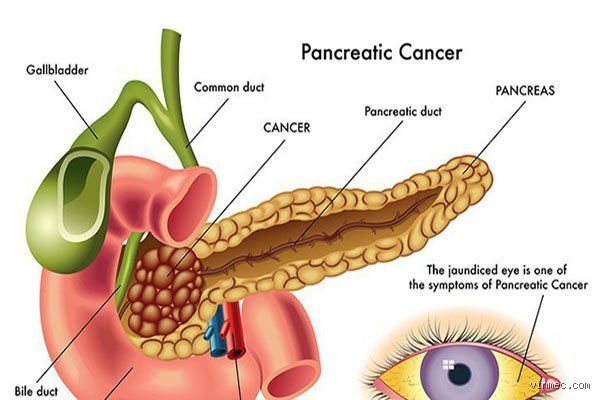
To understand how fasting might alter, repair, or rejuvenate the pancreas, one must first appreciate the staggering biological complexity and metabolic intensity of the organ itself. Anatomically divided into the head, body, and tail, the pancreas performs two distinct physiological functions that together consume a massive amount of cellular energy and biosynthetic machinery. Approximately ninety-five percent of the pancreatic mass is dedicated to the exocrine system. Here, specialized acinar cells synthesize, pack, and secrete an array of powerful digestive zymogens—including trypsinogen, chymotrypsinogen, procarboxypeptidase, pancreatic amylase, and lipolytic enzymes—into the pancreatic ductal network. These enzymes travel to the duodenum, where they become activated to break down dietary proteins, carbohydrates, and fats. The remaining five percent of the pancreatic landscape is composed of the endocrine tissue, famously organized into the microscopic clusters known as the islets of Langerhans.
Within these remarkable neuroendocrine micro-organs reside several distinct cellular populations, most notably the insulin-producing beta cells, glucagon-secreting alpha cells, somatostatin-producing delta cells, and pancreatic polypeptide-producing PP cells. The beta cells, which constitute the majority of the islet mass in humans, bear an immense physiological burden. Every time an individual consumes a meal containing carbohydrates or proteins, postprandial hyperglycemia triggers these beta cells to rapidly synthesize, process, and exocytose millions of insulin molecules into the capillary network. This intricate secretory dance must be executed with absolute precision to maintain systemic blood glucose within the narrow, life-sustaining range of approximately 70 to 100 milligrams per deciliter.
Yet, this relentless secretory demand creates a state of chronic cellular vulnerability. In the context of modern hyper-caloric diets characterized by chronic overnutrition, high glycemic loads, and persistent hyperinsulinemia, beta cells are driven into a state of perpetual hyper-activation. This persistent metabolic stress leads directly to intracellular calcium dysregulation, mitochondrial overload, and the excessive generation of reactive oxygen species (ROS). Over time, this oxidative stress precipitates endoplasmic reticulum (ER) stress, wherein the folding capacity of the endoplasmic reticulum is overwhelmed by the sheer volume of proinsulin synthesis. Unmitigated ER stress triggers the unfolded protein response (UPR), which, if chronic and unresolved, ultimately tips the cellular balance toward apoptosis and programmed cell death. Understanding this pathway of beta-cell exhaustion provides the fundamental rationale for exploring fasting: by removing the constant, unrelenting stimulus for insulin secretion, can we offer the endocrine pancreas a period of crucial physiological rest?
Metabolic shifts during fasting: From glycolytic dependency to ketone utilization
When an individual transitions from a postprandial (fed) state to a fasting state, the body undergoes a profound systemic metabolic reconfiguration. This shift is not merely a passive reduction in circulating calories; it is an active, highly orchestrated neuroendocrine adaptation designed to sustain cellular energy homeostasis in the absence of exogenous fuel. Within the first few hours following the cessation of food intake, circulating glucose and insulin levels decline precipitously, while counter-regulatory hormones such as glucagon and catecholamines rise. This hormonal pivot signals the liver to transition from glycogenolysis, the breakdown of stored glycogen, to hepatic gluconeogenesis, while concurrently prompting adipose tissue to initiate lipolysis, releasing non-esterified fatty acids (NEFAs) and glycerol into the bloodstream.
As the fast extends beyond twenty-four to forty-eight hours, hepatic glycogen stores become largely depleted, forcing a systemic metabolic transition toward fatty acid oxidation and hepatic ketogenesis. The liver converts excess circulating free fatty acids into ketone bodies, primarily beta-hydroxybutyrate (BHB) and acetoacetate, which serve as highly efficient, alternative energy substrates for peripheral tissues, including the myocardium, skeletal muscle, and the central nervous system.
This metabolic transition exerts a powerful protective influence on the pancreas. In the fed state, pancreatic tissue, particularly the hyper-metabolic beta cells, is continuously exposed to high concentrations of glucose and circulating lipids. Chronic exposure to elevated free fatty acids in the presence of high glucose, a pathological state commonly referred to as glucolipotoxicity, leads to the accumulation of toxic lipid intermediates such as diacylglycerols and ceramides within the beta cells. These lipotoxic molecules impair insulin gene expression, disrupt mitochondrial oxidative phosphorylation, and trigger apoptotic cascades.
By inducing a fasting state, circulating levels of both glucose and non-esterified fatty acids decline, interrupting this destructive glucolipotoxic cycle. The elevation of circulating ketone bodies, particularly beta-hydroxybutyrate, acts far beyond its role as a mere cellular fuel. BHB functions as an endogenous signaling molecule and an epigenetic modifier. It acts as an inhibitor of class I histone deacetylases (HDACs), modifying chromatin structure to upregulate stress-resistance genes, suppress inflammatory pathways, and enhance cellular antioxidant defenses within pancreatic tissue. Through these integrated systemic shifts, fasting creates an internal biochemical milieu that halts ongoing cellular damage and establishes a permissive environment for tissue repair.
Autophagy and cellular housekeeping in the endocrine and exocrine pancreas
One of the most compelling biological mechanisms proposed to explain the restorative potential of fasting is the upregulation of autophagy, an evolutionary conserved intracellular degradation and recycling system. Discovered and elucidated at the molecular level through groundbreaking work on autophagy-related (Atg) genes, this housekeeping mechanism allows cells to sequester damaged organelles, misfolded proteins, and dysfunctional macromolecules into double-membrane vesicles known as autophagosomes. These autophagosomes subsequently fuse with lysosomes, where acid hydrolases degrade the cargo into basic building blocks such as amino acids, fatty acids, and nucleotides, which are then recycled back into the cellular economy for energy production or de novo synthesis.
Under basal conditions, autophagy operates at a low level to maintain cellular homeostasis. However, the induction of autophagy is exquisitely sensitive to nutrient availability and intracellular energy status, being powerfully stimulated by nutrient deprivation and drops in the intracellular ATP-to-AMP ratio. The master regulatory kinase governing this process is the mammalian target of rapamycin (mTOR), a nutrient-sensing protein kinase that promotes anabolic processes and actively suppresses autophagy when amino acids and growth factors are abundant. Conversely, fasting leads to the inhibition of mTOR complex 1 (mTORC1) and the simultaneous activation of AMP-activated protein kinase (AMPK), a cellular energy sensor that directly phosphorylates and activates initiation complexes of the autophagic machinery.
Within the pancreas, the maintenance of robust autophagic flux is exceptionally critical for long-term functional survival. Beta cells, due to their specialized role as professional secretory cells, are continuously synthesizing massive quantities of proteins, rendering them exceptionally vulnerable to the accumulation of misfolded proinsulin molecules and damaged mitochondria. If left unchecked, these damaged organelles generate a surplus of reactive oxygen species that inflict structural damage on cellular membranes and DNA. Fasting-induced autophagy clears these dysfunctional mitochondria, a selective form of autophagy known as mitophagy, thereby restoring mitochondrial respiratory efficiency, reducing oxidative stress, and preserving glucose-stimulated insulin secretion (GSIS).
Similarly, in the exocrine pancreas, proper autophagic clearance prevents the premature intracellular activation of digestive zymogens, a catastrophic pathological event that triggers autodigestion, acinar cell necrosis, and the initiation of acute or chronic pancreatitis. By periodically clearing out damaged subcellular components and mitigating basal inflammatory tone, fasting acts as an intrinsic cellular custodian, rejuvenating the structural integrity of both the endocrine islets and the exocrine acinar architecture.
Hormonal reset: Insulin sensitivity, Beta-Cell rest, and the incretin axis
The concept of a pancreatic "reset" must also be evaluated through the lens of dynamic endocrine signaling, particularly the relationship between insulin resistance, peripheral tissue responsiveness, and beta-cell workload. In individuals with insulin resistance, a hallmark of metabolic syndrome, obesity, and prediabetes, peripheral target tissues such as skeletal muscle, liver, and adipose tissue exhibit a blunted response to circulating insulin. To overcome this peripheral resistance and maintain normoglycemia, the pancreatic beta cells undergo a compensatory functional adaptation, upregulating insulin synthesis and secreting supraphysiological amounts of insulin into the bloodstream. This chronic hyperinsulinemia, while temporarily effective at controlling blood glucose, places an unsustainable workload on the islets of Langerhans, accelerating beta-cell exhaustion and driving the progressive loss of functional beta-cell mass characteristic of advancing type 2 diabetes.
Fasting interrupts this vicious pathological feedback loop through multiple distinct physiological pathways. By enforcing a period of absolute or relative caloric abstinence, fasting dramatically reduces basal and stimulated insulin secretion, granting the beta cells a much-needed physiological reprieve. This "beta-cell rest" prevents the continuous depletion of insulin secretory granules, allows the endoplasmic reticulum to recover from chronic folding stress, and restores the sensitivity of intracellular calcium signaling pathways required for proper exocytosis.
Concurrently, fasting profoundly enhances peripheral insulin sensitivity. As hepatic glycogen stores are exhausted and systemic lipid oxidation increases, ectopic lipid deposits within the liver and skeletal muscle are mobilized and burned for fuel. This clearance of intracellular lipid intermediates (such as diacylglycerols and ceramides) re-establishes normal insulin receptor signaling cascades, including the phosphorylation of insulin receptor substrate (IRS) proteins and the subsequent translocation of glucose transporter type 4 (GLUT4) vesicles to the plasma membrane in skeletal myocytes and adipocytes.
When feeding is eventually reintroduced following a fasting protocol, the body responds with markedly improved metabolic efficiency. Because peripheral tissues are now exquisitely sensitive to insulin, significantly lower circulating concentrations of the hormone are required to achieve glucose disposal. This dramatic reduction in postprandial insulin demand translates directly into a permanent reduction in the daily secretory workload of the beta cells. Fasting and caloric restriction modulate the incretin axis, gut-derived hormones such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP), which play vital roles in enhancing glucose-dependent insulin secretion, promoting beta-cell survival, and slowing gastric emptying. By resetting the sensitivity of peripheral tissues and unloading the hyperactive endocrine pancreas, fasting helps break the pathological cycle of metabolic exhaustion and re-establishes healthy endocrine equilibrium.
Explore related aspects of metabolic health and pancreatic physiology:
The quest for bio-hacking and metabolic optimization has led many to explore extreme dietary protocols, with intermittent and prolonged fasting taking center stage. Yet, when examining whether abstaining from food can genuinely reverse damage or structurally renew the organ responsible for insulin and digestive enzymes, where things get complicated is distinguishing between popular wellness claims and rigorous, peer-reviewed clinical science. While animal studies, particularly those spearheaded by researchers like Dr. Valter Longo, have shown that specialized fasting-mimicking diets can trigger cellular reprogramming and prompt pancreatic beta-cell regeneration in mice, translating these dramatic biological overhauls to human physiology remains an ongoing scientific journey. Moreover, the human pancreas is an immensely complex dual-purpose gland, balancing delicate endocrine clusters with heavy exocrine duties, making any single intervention prone to diverse and unpredictable reactions across different metabolic profiles.
Can fasting reverse insulin resistance by giving the pancreas a break?
Resting the insulin-producing beta cells is often cited as a primary benefit of restricting the eating window, allowing baseline circulating insulin levels to drop significantly. When no exogenous nutrients are introduced, the body shifts away from continuous glucose processing, which theoretically reduces cellular overstimulation and can improve peripheral insulin sensitivity over time. Furthermore, this metabolic downtime encourages the clearance of visceral fat deposits that chronically pressure pancreatic function, helping to ease the inflammatory burden on surrounding tissues. However, it's important to note that these systemic improvements do not automatically equate to a full structural "reset" of the organ itself. As a result, while short-term metabolic relief is frequently observed, individuals with advanced metabolic dysfunction require comprehensive medical management rather than relying on fasting alone to repair chronic cellular wear and tear.
How does autophagy target damaged pancreatic cells during prolonged restriction?
During extended periods without caloric intake, the body initiates autophagy, an intracellular cleaning mechanism that systematically breaks down and recycles dysfunctional proteins, organelles, and damaged cellular debris. In experimental models, this cellular housekeeping has been observed to clear out senescent cells within pancreatic islets, reducing localized inflammation and paving the way for precursor cells to differentiate into functional endocrine tissue. Delving deeper into these molecular pathways reveals that down-regulating nutrient-sensing pathways like mTOR and PKA plays a critical regulatory role in reactivating developmental genes linked to tissue renewal. However, the issue remains that human pancreatic architecture is tightly regulated and far less plastic than that of rodents, meaning the scale and efficiency of autophagy observed in a laboratory setting cannot yet be reliably replicated in human clinical trials.
What are the primary metabolic risks when attempting unsupervised fasting protocols?
Dropping caloric intake too aggressively without professional oversight can backfire, particularly for individuals struggling with blood sugar regulation or underlying pancreatic vulnerabilities. When the body undergoes prolonged energy deficits, counter-regulatory hormones such as cortisol and adrenaline spike to maintain glucose availability, which can paradoxically trigger glucose spikes or exacerbate metabolic instability in vulnerable populations. There's no consensus on the safety margins for extended fasts, with many endocrinologists warning that erratic eating patterns can precipitate muscle wasting, nutritional deficiencies, or dangerous electrolyte imbalances. Furthermore, over-restricting food intake can disrupt normal gallbladder and exocrine function, potentially aggravating rather than alleviating digestive distress. Therefore, anyone considering structured therapeutic fasts must navigate these protocols under strict clinical supervision to safeguard against unintended physiological harm.
Evaluating the promise of metabolic rest and organ longevity
Navigating the vast mix of modern nutritional science requires separating the genuine physiological benefits of metabolic rest from exaggerated marketing myths. there's still a long way to go when it comes to claiming that a weekend fast can magically erase years of metabolic damage or permanently cure chronic pancreatic conditions. While structured dietary interventions offer powerful tools for enhancing insulin sensitivity and reducing systemic inflammation, they must be viewed as supportive strategies rather than standalone miracle cures. True metabolic health relies on a sustainable, balanced lifestyle that respects the profound complexity of human biology rather than looking to extreme fasting as a quick fix.