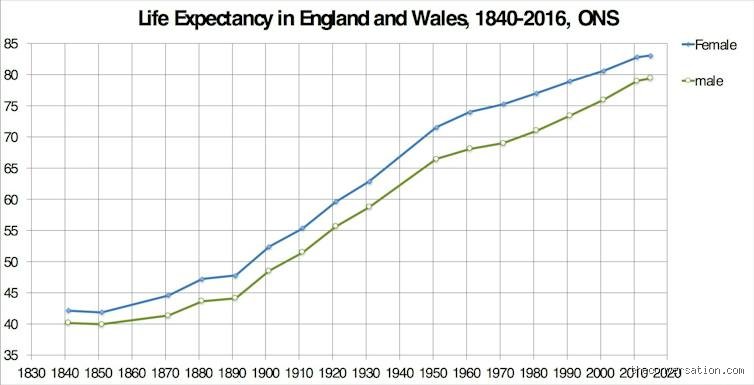
The Mid-Victorian paradox: Demography and Life Expectancy in the United Kingdom in 1850
For the modern observer, a life expectancy hovering around forty immediately conjures an image of a society populated almost exclusively by the young, where reaching one's fifth decade was a rare and celebrated anomaly. In demographic science, however, life expectancy at birth (e0e_0e0) is an actuarial abstraction, a synthetic summary metric derived from age-specific mortality rates at a given point in time, rather than a literal prediction of the age at which a typical adult would drop dead. Understanding what it meant to live and die in the UK in 1850 requires dismantling the misleading simplicity of that single headline number. It demands an examination of the brutal toll of infant and child mortality, the sharp geographical divides created by rapid urbanization, the precariousness of class, and the epidemiological landscape that preceded the germ theory of disease.
The actuarial illusion: Life Expectancy at Birth vs. Adult longevity
To interpret mid-Victorian mortality statistics accurately, one must distinguish between life expectancy at birth and conditional life expectancy, the number of additional years an individual could expect to live once they had survived the perilous gauntlet of early childhood.
In 1850, the arithmetic mean of human lifespan in Britain was dragged downward by an extraordinary rate of death among infants and toddlers. According to the meticulous civil registration records compiled by the General Register Office (GRO), roughly 150 to 160 out of every 1,000 live-born infants died before reaching their first birthday. Of those who survived infancy, another substantial fraction perished before age five from acute infectious diseases such as measles, scarlet fever, whooping cough, and diphtheria. In total, nearly one in four children born in 1850 did not survive to see their fifth birthday.
Because an infant death registers as zero years lived in the actuarial ledger, high infant mortality acts as a massive mathematical anchor on life expectancy at birth. When demographic historians adjust the 1850 life tables to examine individuals who successfully navigated the hazards of early childhood, a markedly different picture emerges:
| Age Milestone in 1850 (England & Wales) | Remaining Life Expectancy (Approximate) | Total Expected Age at Death |
|---|---|---|
| At Birth (Age 0) | 40 – 41 years | 40 – 41 years |
| Age 5 | 49 – 51 years | 54 – 56 years |
| Age 15 | 43 – 45 years | 58 – 60 years |
| Age 30 | 32 – 34 years | 62 – 64 years |
| Age 50 | 19 – 21 years | 69 – 71 years |
As the table demonstrates, a British child who reached their fifth birthday in 1850 could reasonably expect to live into their mid-fifties. If that same individual survived the occupational hazards of young adulthood and the maternal mortality risks of childbearing to reach age thirty, living into one's sixties was entirely commonplace. Reaching seventy or eighty was by no means miraculous; Victorian parishes, workhouses, and parlors contained a visible cohort of elderly citizens. The demographic tragedy of 1850 was not that human beings aged prematurely, nor that the biological ceiling of human longevity was lower than it is today, but rather that an enormous proportion of the population never got the chance to grow old.
The urban penalty: Industrialization and the geography of Death
While national averages offer a useful baseline, speaking of a single "British" life expectancy in 1850 obscures one of the most profound demographic phenomena of the nineteenth century: the urban penalty. The Industrial Revolution had triggered the most rapid urban migration in human history. Between 1801 and 1851, the proportion of the population living in urban areas in England and Wales surged from roughly 30 percent to over 50 percent, making Britain the first predominantly urban society in the world.
Cities grew far faster than their civic infrastructure could accommodate. Manchester, Liverpool, Birmingham, Leeds, and Glasgow swelled with rural migrants and Irish immigrants fleeing the devastation of the Great Famine. Housing was thrown up hastily in the form of poorly ventilated "back-to-back" terraces, damp cellar dwellings, and overcrowded tenements. Without municipal water systems, modern sewage networks, or regular refuse collection, these dense urban centers became lethal incubators for waterborne and airborne pathogens.
Consequently, geography dictated survival in 1850 far more decisively than it does in the twenty-first century. William Farr, the pioneering medical statistician serving as Compiler of Abstracts at the General Register Office, spent the 1840s and 1850s mapping these stark disparities. Farr demonstrated that while rural agricultural counties, such as Surrey, Sussex, or parts of the West Country, enjoyed a life expectancy at birth of 45 to 50 years, the industrial heartlands were experiencing a demographic catastrophe.
In the worst-affected urban districts, life expectancy plummeted to levels not seen since the Black Death:
Liverpool: Widely regarded as the unhealthiest city in mid-Victorian Britain due to extreme overcrowding, port-borne infections, and vast numbers of destitute Irish famine refugees, Liverpool recorded an average life expectancy at birth of just 25 to 26 years in the late 1840s and 1850.
Manchester: The cradle of the cotton industry exhibited an overall life expectancy at birth hovering near 27 to 29 years, driven by respiratory ailments from coal smoke and cotton dust alongside relentless gastrointestinal infections.
London: The metropolis presented a complex mosaic. While affluent western parishes like St. George Hanover Square recorded life expectancies approaching rural norms (around 40 to 44 years), overcrowded eastern districts such as Whitechapel, Bethnal Green, and St. Giles languished in the high twenties to low thirties.
This stark divergence meant that moving from a countryside village in Wiltshire to a factory district in Lancashire in 1850 effectively cost a family up to fifteen or twenty years of average life expectancy.
Class, occupation, and the socioeconomic gradient
Layered atop the urban-rural divide was an equally unforgiving socioeconomic hierarchy. Social reformers and statisticians of the era, most notably Edwin Chadwick in his landmark 1842 Report on the Sanitary Condition of the Labouring Population of Great Britain, had already exposed the brutal correlation between social class and mortality, a relationship that remained firmly entrenched in 1850.
Chadwick’s data, alongside subsequent municipal health reports, revealed that within the very same city, the wealthy gentry and the industrial working class inhabited entirely different epidemiological worlds. In industrial centers like Manchester and Leeds, the average age at death for the gentry and professional classes was typically 38 to 44 years (a figure still depressed by childhood diseases that respected no class boundary). For tradesmen and shopkeepers, the average fell to roughly 20 to 25 years. For mechanics, factory operatives, and unskilled laborers, the average age at death sank to an astonishing 17 to 19 years, largely because over half of working-class children died before reaching age five.
Several interlocking mechanisms drove this class disparity:
Housing Density and Sanitation: Wealthier families occupied spacious townhouses in elevated, well-drained suburbs equipped with private water cisterns and early flushing water closets. Working-class families crowded into single rooms in low-lying districts near rivers and canals that doubled as open sewers, sharing a single outdoor privy and a contaminated standpipe among dozens of households.
Nutritional Vulnerability: While real wages for British workers were beginning a slow, uneven upward climb by 1850, working-class diets remained heavily reliant on bread, potatoes, and tea, with limited access to fresh milk, meat, or vegetables. Adulteration of food, such as alum in bread or watered-down, bacteria-laden milk, was rampant prior to the passage of effective food safety legislation later in the century. Chronic undernutrition weakened immune responses, turning otherwise survivable childhood infections into fatal events.
Occupational Hazards: Industrial labor extracted a direct physical toll. Coal miners faced catastrophic roof collapses, methane explosions, and progressive black lung disease (anthracosis). Textile workers inhaled dense clouds of cotton and flax fibers, succumbing to byssinosis ("brown lung") and tuberculosis. Sheffield cutlery grinders inhaled metallic and stone dust that routinely killed them before age thirty-five, while matchmakers and pottery workers suffered debilitating poisoning from white phosphorus and lead glazes.
The epidemiological landscape: Killers of 1850
To understand why life expectancy stood at 40 years in 1850, one must look at what was actually killing the British population. In the mid-nineteenth century, medicine stood on the threshold of a scientific revolution, yet germ theory had not yet been established by Louis Pasteur or Robert Koch. The prevailing medical orthodoxy was the miasma theory, the belief that diseases were transmitted by noxious vapors ("bad air") rising from rotting organic matter, stagnant water, and filth. While miasma theory accidentally prompted useful sanitary cleanups, it left physicians powerless to prevent or cure the specific microbial pathogens ravaging the country.
Mortality in 1850 was overwhelmingly dominated by infectious and parasitic diseases, which accounted for roughly 60 to 70 percent of all deaths, the exact inverse of modern Britain, where chronic degenerative conditions like cardiovascular disease and cancer predominate.
Tuberculosis ("Consumption"): The single greatest killer of adults in 1850 was Mycobacterium tuberculosis. Responsible for roughly one in every six to eight deaths across Britain, tuberculosis thrived in damp, poorly ventilated homes and crowded workshops. Because it struck disproportionately at young adults between the ages of 15 and 35, it hollowed out families and deprived households of primary breadwinners.
Waterborne Enteric Diseases: Cholera, typhoid fever, and infantile summer diarrhea were perennial scourges. Britain had just endured the devastating 1848–1849 cholera pandemic, which claimed over 53,000 lives in England and Wales alone. Even in non-epidemic years like 1850, typhoid and dysentery circulated continuously through contaminated wells and rivers. For infants weaned early onto cow's milk or gruel mixed with unboiled water, acute diarrheal dehydration was the leading cause of death.
Childhood Exanthems and Respiratory Infections: Scarlet fever, measles, whooping cough, and smallpox swept through urban neighborhoods in cyclical waves. Although Edward Jenner had introduced smallpox vaccination in 1796, uptake remained inconsistent until compulsory infant vaccination was enacted in 1853, leaving periodic outbreaks lethal. Meanwhile, bronchitis and pneumonia, exacerbated by coal-smoke air pollution and unheated housing, claimed vast numbers of both the very young and the elderly every winter.
Maternal Mortality: For women of childbearing age, pregnancy carried persistent peril. In 1850, approximately 5 women died for every 1,000 live births (roughly fifty times the modern UK rate). Puerperal fever, a streptococcal infection often transmitted unintentionally by doctors and midwives who did not practice antiseptic handwashing, alongside hemorrhage and obstructed labor, meant that adult female life expectancy lagged behind or barely matched male life expectancy in many districts, reversing the biological longevity advantage women enjoy today.
By 1850, however, the sheer visibility of these mortality statistics, broadcast through William Farr’s quarterly reports and the newly established General Board of Health under the Public Health Act of 1848, had begun to shift the national conscience. Britain was poised at a critical inflection point between the demographic toll of early industrialization and the sanitary, medical, and nutritional reforms that would transform human survival over the next century.
The urban penalty: Industrialization and geographic disparities
While the national average life expectancy at birth in England and Wales hovered around 40 to 41 years in 1850, that aggregate figure conceals a stark, brutal geographic divide. To understand mid-Victorian mortality, demographers rely on the concept of the "urban penalty", the phenomenon where rapid, unplanned urbanization drove death rates in industrial centers significantly higher than those in rural agricultural counties.
By 1851, the United Kingdom had become the first nation in history where more than half the population lived in towns and cities. However, urban infrastructure had not kept pace with this demographic explosion. While a child born in rural Surrey or healthy agricultural pockets of the south could expect to live into their late forties or even early fifties, a child born into the industrial slums of Manchester, Liverpool, or Glasgow faced a drastically shorter horizon.
In the late 1840s and early 1850s, life expectancy at birth in Manchester and Liverpool frequently dipped into the mid-to-late twenties, and for the working-class laborers living in densely packed cellar dwellings and back-to-back terraced housing, the statistical expectation at birth could fall below 20 years.
| Region / Settlement Type | Approximate Life Expectancy at Birth (c. 1850) | Primary Drivers of Mortality |
|---|---|---|
| Rural Agricultural Counties (e.g., Surrey, Dorset) | 45 – 50 years | Lower population density, cleaner water sources, less industrial pollution |
| National Average (England & Wales) | 40 – 41 years | Balanced by high rural survival rates against severe urban mortality |
| Industrial Towns (e.g., Birmingham, Leeds) | 30 – 35 years | Overcrowding, factory accidents, early respiratory disease |
| Major Port & Textile Cities (e.g., Liverpool, Manchester) | 25 – 29 years | Contaminated water supplies, cholera, typhus, extreme infant mortality |
The invisible killers: Infectious disease and living conditions
In 1850, Britain stood on the precipice of the bacteriological revolution, yet medical science still largely operated under the miasma theory, the belief that diseases were transmitted by noxious "bad air" rising from rotting organic matter. Consequently, the true biological vectors of Victorian mortality ran unchecked through the nation's streets and waterways.
Waterborne and filth Diseases
Without modern sewage systems or water filtration, urban rivers like the Thames in London and the Irwell in Manchester functioned simultaneously as open sewers and sources of drinking water. Cholera struck Britain in devastating waves, most notably in 1831–32, 1848–49, and 1853–54, killing tens of thousands within days of symptom onset. Alongside cholera, endemic waterborne illnesses like typhoid fever and dysentery claimed lives year-round, hitting young children and the elderly hardest.
Airborne and crowd Diseases
Overcrowded housing facilitated the rapid spread of airborne pathogens. Tuberculosis (then known as consumption) was the single greatest killer of young adults in mid-19th-century Britain, thriving in damp, poorly ventilated homes and dusty textile mills. Among children, scarlet fever, measles, whooping cough, and diphtheria swept through neighborhoods with terrifying regularity, turning routine childhood illnesses into fatal events.
Occupational Hazards and pollution
For those who survived childhood and entered the industrial workforce, the physical toll of Victorian labor shortened adult lifespans. Coal miners succumbed to "black lung" (anthracosis) and catastrophic underground explosions; pottery workers suffered from lead poisoning; and Sheffield knife-grinders inhaled fatal quantities of metallic dust, often dying of respiratory failure before reaching forty. Outside the factory gates, thick coal smoke blanketed industrial cities, blocking sunlight and contributing to widespread rickets (vitamin D deficiency), which weakened immune systems and complicated childbirth for women.
Class, Gender, and the social gradient of Death
Longevity in 1850 was not merely a matter of where one lived, but also of social standing and biological sex. Social reformer Edwin Chadwick’s landmark Report on the Sanitary Condition of the Labouring Population of Great Britain (1842) had already exposed the class divide in mortality, and by 1850, those disparities remained deeply entrenched.
The Aristocracy and Gentry: Wealthier families enjoyed spacious, well-ventilated homes, varied diets rich in protein and fresh produce, access to private physicians, and the financial means to flee cities during summer disease outbreaks. Their life expectancy at birth regularly exceeded 50 to 55 years, comparable to early 20th-century standards.
The Working Class: Manual laborers and factory operatives endured chronic malnutrition, adulterated food (such as bread bulked with alum or milk diluted with contaminated water), and zero safety net in the event of injury or illness. For an urban laborer, reaching age 45 was considered entering old age.
The Gender Gap: Across the UK in 1850, women maintained a slight biological advantage, living on average two to three years longer than men (roughly 42 years for women versus 39–40 years for men). However, this gap was far narrower than it is today. High rates of maternal mortality, driven by puerperal (childbed) fever, lack of antiseptic practices, and pelvic deformities caused by childhood rickets, claimed the lives of roughly 5 in every 1,000 births, offsetting much of women's natural longevity advantage during their childbearing years.
The turning point: From Mid-Century stagnation to the Mortality Revolution
Looking at 1850 in isolation reveals a society caught in a demographic bottleneck: economic output and technological innovation were surging, yet human longevity had largely stagnated since the late 18th century. Paradoxically, however, 1850 also marks the exact historical inflection point when the foundations for modern life expectancy were laid.
Just two years prior, Parliament had passed the Public Health Act of 1848, creating the General Board of Health and empowering local authorities to appoint medical officers, build sewers, and regulate slaughterhouses. In 1854, physician John Snow famously traced a Soho cholera outbreak to the Broad Street water pump, providing the empirical proof needed to dismantle miasma theory and establish modern epidemiology. Following the "Great Stink" of 1858, engineer Joseph Bazalgette began constructing London's monumental intercepting sewer network, a model soon replicated across Britain's industrial cities.
Once clean water, waste removal, improved nutrition, and eventually vaccination and antisepsis took hold in the final decades of the 19th century, British life expectancy broke free from its mid-Victorian ceiling. By 1900, life expectancy at birth had climbed to nearly 48 years; by 1950, it surpassed 69 years; and today, it stands above 81 years.
The statistic that UK life expectancy in 1850 was roughly 40 years tells a dual story. It captures the harsh reality of an era in which infectious disease and unregulated urbanization robbed millions of children of the chance to grow up, yet it also stands as the baseline from which one of humanity's greatest public health triumphs began.