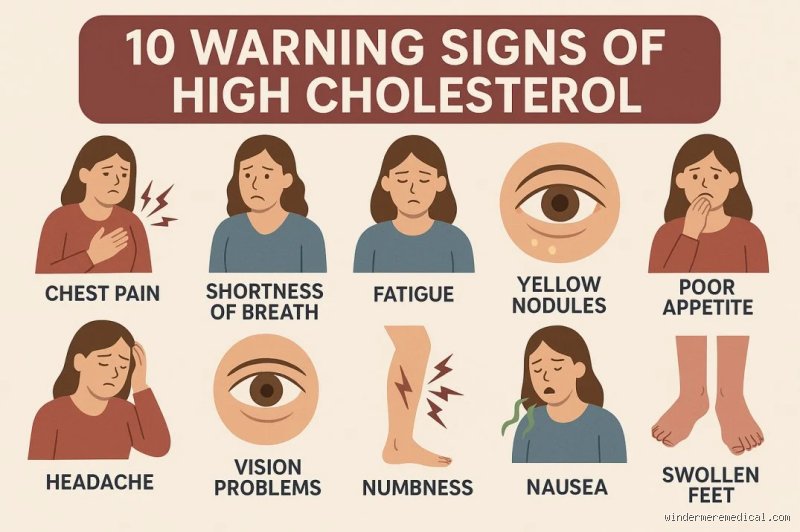
This insidious nature is precisely what makes public education around lipid profiles so vital, yet so profoundly challenging. Millions of individuals walk around with severely compromised vascular health, completely unaware that fatty deposits are slowly accumulating along the interior linings of their vital blood vessels. When the human body finally does begin to broadcast distress signals, those signs frequently indicate that the condition has already progressed far beyond initial plaque formation, having advanced to a critical stage of arterial narrowing, stiffening, or partial obstruction.
Understanding the five primary indicators associated with advanced or severe high cholesterol requires a foundational shift in how we view cardiovascular wellness. While a routine blood test, specifically a lipid panel measuring total cholesterol, Low-Density Lipoprotein (LDL), High-Density Lipoprotein (HDL), and triglycerides, remains the only definitive method for catching hypercholesterolemia in its asymptomatic infancy, the human body eventually develops secondary physical markers when lipid levels remain dangerously unchecked over long periods.
The underlying mechanics: How cholesterol accumulates unnoticed
To appreciate why physical signs of high cholesterol take so long to appear, one must first examine the microscopic mechanics of lipid metabolism and vascular pathology. Cholesterol itself is not an inherent poison; in fact, it is an essential biochemical building block required by every cell in the human body. It plays a critical role in cellular membrane integrity, the synthesis of steroid hormones such as estrogen, testosterone, and cortisol, and the production of Vitamin D and bile acids necessary for fat digestion. The liver manufactures the vast majority of the cholesterol your body needs, while the remainder is absorbed directly from dietary sources containing animal fats.
Because cholesterol is a waxy, fat-based substance, it cannot dissolve or travel freely through the watery medium of the bloodstream. To solve this logistical problem, the body packages cholesterol into microscopic transport vehicles known as lipoproteins. These specialized proteins coat the hydrophobic cholesterol and triglyceride molecules, allowing them to be safely ferried to tissues throughout the body.
Among these transport vehicles, Low-Density Lipoprotein (LDL) is commonly labeled as "bad" cholesterol. LDL’s primary function is to deliver cholesterol particles to peripheral cells. However, when LDL particles are present in excessive quantities, or when they undergo chemical modification through processes such as oxidation, they begin to infiltrate the delicate innermost lining of the arterial walls, a single-cell layer known as the endothelium.
Once trapped beneath the endothelial layer, these oxidized LDL particles trigger a localized inflammatory immune response. White blood cells, specifically monocytes, migrate into the arterial wall and transform into macrophages, aggressively gobbling up the excess LDL until they become engorged, fat-laden cells called foam cells. Over time, these foam cells accumulate, dying and releasing their lipid contents to form a core of debris. The body attempts to wall off this inflammatory mess by building a fibrous cap over it, creating what is known as an atherosclerotic plaque.
As these plaques grow larger, they gradually encroach upon the arterial lumen, reducing the volume of blood that can flow freely to vital organs. Yet, the human vascular network exhibits remarkable elasticity and compensation mechanisms. An artery can often lose a significant percentage of its internal diameter before systemic blood flow drops enough to cause noticeable ischemic symptoms in resting tissues. This physiological buffer is the primary reason why high cholesterol remains invisible for so long, emphasizing why identifying secondary physical manifestations and maintaining routine screening protocols are absolute necessities for lifelong cardiovascular protection.
Decoding the silent pathology of lipid imbalances
The human circulatory system operates largely out of sight and out of mind, maintaining a delicate hydraulic equilibrium that delivers oxygen and vital nutrients to every tissue. Within this pressurized network, cholesterol travels bound to specialized proteins, serving essential physiological functions such as cell membrane stabilization and hormone synthesis. However, when metabolic pathways falter, low-density lipoprotein (LDL) particles can accumulate beyond the clearance capacity of hepatic receptors. This surplus of circulating lipids initiates a cascade of endothelial injury, oxidative modification, and sub-endothelial retention.
Because the early stages of atherosclerosis and systemic hyperlipidemia rarely trigger acute systemic distress, high cholesterol has rightfully earned its designation as a silent pathology. The systemic nature of lipid accumulation means that pathological changes occur over decades before crossing the threshold of clinical manifestation. Understanding how these microscopic alterations eventually translate into physiological warning signs requires a rigorous examination of lipid deposition dynamics across diverse vascular beds and peripheral tissues.
Cutaneous and ocular manifestations of excess lipids
While internal arterial narrowing progresses silently, the integumentary and visual systems occasionally provide direct external windows into systemic lipid metabolism. When blood concentrations of cholesterol and triglycerides reach profound elevations, frequently driven by genetic predispositions such as familial hypercholesterolemia, excess lipoproteins escape the microvasculature and are engulfed by tissue macrophages. These lipid-engorged scavenger cells, known as foam cells, aggregate in specific anatomical zones where local tissue temperatures and mechanical pressures favor deposition.
One of the most notable visual markers is xanthelasma palpebrarum, characterized by soft, velvety, yellowish plaques that typically manifest symmetrically near the inner canthi of the eyelids. Similarly, corneal arcus (or arcus senilis) presents as an opaque white, grey, or light-yellow ring encircling the peripheral cornea. While corneal arcus is a normal physiological variant in older populations due to age-related lipid infiltration, its appearance in individuals under the age of forty strongly correlates with unmanaged dyslipidemia and accelerated vascular aging.
Beyond the ocular adnexa, lipid deposits can manifest as xanthomas across various structural landmarks of the musculoskeletal system. Tendinous xanthomas frequently present as firm, nodular swellings embedded within major tendons, most notably the Achilles tendon and the extensor tendons of the hands. Eruptive xanthomas, by contrast, appear as sudden crops of small, yellow-orange papules surrounded by inflammatory halos, often erupting over pressure-bearing surfaces such as the buttocks, knees, and elbows. The presence of these physical stigmata serves as an unambiguous clinical indicator that systemic lipid transport mechanisms are severely overwhelmed.
Hemodynamic compromise in peripheral vascular beds
As systemic atherosclerosis advances, the gradual expansion of fibrofatty plaques compromises the internal luminal diameter of muscular and elastic arteries. This mechanical narrowing restricts volumetric blood flow, introducing measurable hemodynamic gradients during periods of elevated metabolic demand. The peripheral vasculature of the lower extremities frequently bears the early brunt of this generalized atherosclerotic burden, manifesting as peripheral artery disease (PAD).
In patients with significant lower-extremity arterial stenosis, muscular perfusion fails to match the oxygen requirements of exercising skeletal muscle. This mismatch produces intermittent claudication, a characteristic cramping, aching, or fatiguing pain localized in the calves, thighs, or gluteal regions that consistently manifests during physical exertion and resolves reliably with rest. Beyond muscular discomfort, chronic arterial insufficiency impairs distal tissue viability, leading to subtle physical signs such as diminished peripheral pulses, delayed capillary refill, coolness of the distal extremities, and trophic changes such as hair loss and cutaneous thinning over the lower shins and feet.
The neurological and cardiac threshold of acute ischemia
When systemic dyslipidemia goes unrecognized and unmanaged, atherosclerotic plaques undergo progressive remodeling characterized by lipid core expansion, thinning of the fibrous cap, and chronic focal inflammation. These vulnerable plaques carry a high risk of spontaneous rupture or surface fissuring. When a plaque ruptures, exposure of thrombogenic sub-endothelial matrix proteins triggers acute platelet aggregation and activation of the coagulation cascade, culminating in partial or complete luminal thrombosis.
In the coronary circulation, acute vessel occlusion or critical stenosis restricts myocardial oxygen supply, precipitating ischemic syndromes ranging from stable angina to acute myocardial infarction. Patients may experience retrosternal chest discomfort, tightness, or pressure that radiates to the neck, jaw, left shoulder, or arm, frequently accompanied by autonomic symptoms such as diaphoresis, nausea, and dyspnea. Similarly, when atherosclerotic debris or acute thrombi compromise the carotid or cerebral circulation, patients face catastrophic neurological events, including transient ischemic attacks (TIAs) or ischemic strokes, signaled by sudden focal deficits such as unilateral motor weakness, facial asymmetry, and expressive dysphasia.
Strategic clinical interventions and Long-Term risk mitigation
Mitigating the insidious progression of hyperlipidemia requires a structured, multi-modal clinical strategy aimed at stabilizing the vascular endothelium and normalizing circulating lipid fractions. The foundation of management relies upon targeted medical nutrition therapy, emphasizing the reduction of dietary saturated and trans-fats in favor of soluble fibers, plant stanols, and omega-3 polyunsaturated fatty acids. Concurrently, structured aerobic and resistance exercise regimens enhance insulin sensitivity, upregulate peripheral glucose and lipid utilization, and support modest elevations in high-density lipoprotein (HDL) functionality.
When lifestyle modifications prove insufficient to achieve target LDL thresholds, particularly in individuals harboring genetic risk factors or established cardiovascular disease, pharmacotherapy becomes necessary. HMG-CoA reductase inhibitors (statins) remain the cornerstone pharmacological intervention, competitively inhibiting hepatic cholesterol synthesis and upregulating surface LDL receptor expression to clear circulating atherogenic particles. For patients requiring supplementary lipid-lowering efficacy, adjunctive agents such as ezetimibe, PCSK9 inhibitors, or Bempedoic acid provide synergistic mechanisms to drive atherogenic particle concentrations below critical risk thresholds, ultimately interrupting the natural history of silent vascular disease.