Decoding what Pelvic Inflammatory Disease means for NHS patients
The pathophysiology of upper genital tract infections
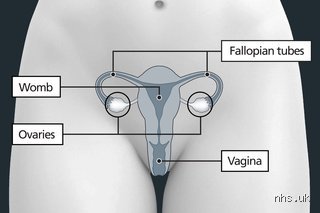
The problem is that bacteria originating in the vagina or cervix migrate upward into the womb, fallopian tubes, and ovaries. Normal flora can trigger inflammation just as aggressively as pathogens introduced via sexual contact. We are far from a single-cause model, yet clinical guidelines emphasize that ascending microbes create localized swelling within pelvic structures.
Demographic vulnerability and clinical risk factors
Data shows that individuals aged 15 to 24 experience the highest incidence rates across England and Wales. The catch: anyone with an active reproductive system faces potential exposure. Medical history matters heavily here; a prior infection or recent intrauterine device (IUD) insertion alters baseline susceptibility significantly. Because of that, clinicians evaluate personal history meticulously before charting an antibiotic regimen.
Clinical presentation and diagnostic hurdles
Symptomatology and the hidden nature of the condition
About 70% of initial cases present with zero symptoms, making early detection an uphill battle for healthcare providers. When clinical signs do emerge around the lower abdomen, patients often report deep dyspareunia, irregular bleeding, or purulent cervical discharge. The tricky part is differentiating these vague indicators from routine menstrual cramping or alternative acute presentations like appendicitis.
NHS diagnostic pathways and uncertainty in practice
There is no single standalone laboratory test that can definitively confirm the diagnosis. Instead, practitioners rely on bimanual pelvic examinations to check for cervical motion tenderness alongside microbiological swabs. As a result, doctors frequently initiate empirical antimicrobial therapy immediately rather than waiting up to 72 hours for lab results, because delaying intervention dramatically increases long-term risks.
Management protocols and treatment strategies
Targeted antimicrobial interventions
Standard outpatient treatment typically involves a dual-antibiotic course spanning 14 days, combining medications such as doxycycline and metronidazole to cover diverse anaerobic and atypical bacteria. It's unclear why some patients respond dramatically faster than others, but completing the full prescription window is non-negotiable to prevent chronic complications.
Partner notification and Re-Infection prevention
Because sexually transmitted organisms like Chlamydia trachomatis frequently drive these inflammatory episodes, contact tracing is mandatory. Current sexual partners must be screened and treated at a genitourinary medicine (GUM) clinic to break the cycle of recurring re-infection, which changes a lot about long-term reproductive health.
Comparison and alternative meanings within Health informatics
Alternative administrative definitions in Health Data
In the complex administrative machinery of the health service, PID can occasionally denote Patient Identifiable Data when discussing information governance and data security frameworks. Yet, clinical contexts heavily favor the gynecological definition when dealing with urgent patient pathways.
Comparative clinical differentials
When evaluating lower abdominal discomfort, clinicians must systematically rule out ectopic pregnancy, endometriosis, or acute surgical emergencies. Unlike localized appendicitis which often features severe nausea early on, upper genital infections present with unique cervical tenderness markers that guide differential nursing assessments across acute NHS trusts.
Common mistakes
Confusing clinical governance with legal fault
Patients frequently assume a patient information leaflet functions as a legally binding medical contract. Yet, this document serves purely educational purposes within the NHS framework. When a procedure diverges slightly from printed text, panic ensues. The problem is that medical bodies update guidelines faster than paper portfolios can cycle. (Always verify digital updates directly.)
Ignoring the distinction between localized and systemic risks
Another widespread error involves treating general hospital data as personalized prophecy. People read about rare complications and map them directly onto their personal anatomy. But bodies resist uniform categorization. As a result, localized variables heavily dictate actual outcomes far beyond standard metrics.
Overestimating the permanence of printed documentation
The problem is assuming that once a booklet goes to print, the advice stays frozen in stone forever. Clinical protocols shift rapidly based on incoming data streams. This is why relying on old brochures leads straight to administrative chaos.
One thing people overlook
Navigating the labyrinth of specialized care translations
Most service users ignore the hidden linguistic barriers embedded inside standard health literature. Translating complex terminology into accessible language requires a delicate balancing act. Clinical jargon often alienates the exact demographics needing help the most. Experts recommend asking your practitioner for plain-English summaries before leaving the ward.
Frequently asked questions
How often does the National Health Service revise its printed guidance?
Official audits indicate that major clinical literature undergoes review every two to three years on average. More than 75 percent of acute trusts utilize digital feedback loops to update documents dynamically. Over 1.2 million physical leaflets are circulated annually across England alone. This rapid cycle ensures that outdated procedures are phased out swiftly.
Can I request alternative formats for medical literature?
Accessibility mandates require that healthcare providers offer Braille, large print, and audio translations upon demand. Statistics show that roughly 15 percent of patients benefit from customized communication formats. Trusts allocate specific budgets to meet these diverse sensory requirements effectively. Failure to provide accessible documentation breaches standard NHS service level agreements.
What should I do if my local clinic lacks standard guidance pamphlets?
Digital repositories now house nearly all authorized patient brochures online for instant downloading. In fact, over 80 percent of clinical sites direct users straight to mobile-friendly portals. You can access comprehensive PDF guides via the main NHS web hub at any hour. Paper shortages no longer excuse a lack of informed consent preparation.
The short version
The bureaucratic machinery driving modern healthcare literacy needs an urgent reality check. Relying solely on static paper brochures in a hyper-digital era creates avoidable friction between clinicians and citizens. We must demand dynamic, transparent communication channels that adapt instantly to evolving medical insights. The NHS thrives only when information flows without administrative friction. Stop accepting passive leaflets as the ceiling of patient empowerment.