Defining "100% Fatal" in modern medicine
True 100% lethality—where a diagnosis serves as an inescapable prognosis—is extraordinarily rare in human pathology. To reach this absolute threshold, a pathogen or biological anomaly must possess a mechanism that completely bypasses, disables, or overwhelms the human immune system while inflicting irreversible damage on vital organ systems, most notably the central nervous system. In epidemiology, a 100% CFR often depends on a critical distinction: preventability versus curability. Some conditions are entirely preventable before symptoms begin, yet become universally fatal the moment clinical signs manifest. Others lack any known preventative measure, vaccine, or therapeutic intervention, remaining 100% fatal from the instant of biological onset.
Examining the diseases at this absolute edge of lethality reveals two distinct biological frontiers: transmissible spongiform encephalopathies (prion diseases), which hold the grim distinction of being strictly 100% fatal with zero known survivors in human history, and symptomatic rabies, the deadliest known viral infection once it breaches the central nervous system.
Prion diseases: The unbroken 100% fatality barrier
If we apply the strictest possible definition of a 100% fatality rate, an illness for which there is no vaccine, no cure, no effective treatment, and not a single documented case of human survival, only one category of disease qualifies: transmissible spongiform encephalopathies (TSEs), commonly known as prion diseases.
Unlike bacteria, viruses, fungi, or parasites, prions are not living organisms and do not contain genetic material (DNA or RNA). Instead, a prion (short for proteinaceous infectious particle) is a misfolded variant of a normal, harmless protein found predominantly in the brain, called the cellular prion protein (PrPCPrP^CPrPC). When an abnormal, misfolded prion protein (PrPScPrP^{Sc}PrPSc) enters the brain, whether through genetic mutation, spontaneous misfolding, or ingestion of contaminated tissue, it acts as a rogue template. Upon contact with normal PrPCPrP^CPrPC proteins, the misfolded prion forces them to abandon their healthy shape and adopt its own corrupted, beta-sheet-rich structure.
This triggers a relentless, exponential chain reaction. As misfolded proteins accumulate, they clump together into toxic amyloid plaques and fibers that systematically destroy neurons. Over months or years, this neuronal death leaves microscopic holes throughout the brain tissue, giving it a characteristic sponge-like appearance under a microscope, hence the term spongiform encephalopathy. Because prions are merely misshapen versions of the body's own native proteins, the human immune system does not recognize them as foreign invaders. No antibodies are produced, no inflammatory response is triggered to clear the threat, and conventional antimicrobial or antiviral drugs have zero effect.
Major human Prion diseases
All known human prion diseases carry a 100% fatality rate, though they differ in how they originate and how rapidly they progress:
| Prion Disease | Primary Cause / Origin | Typical Disease Duration | Key Clinical Features |
|---|---|---|---|
| Creutzfeldt-Jakob Disease (CJD) | Sporadic (85%), inherited (10–15%), or acquired/iatrogenic (<1%) | 4 to 12 months | Rapidly progressive dementia, involuntary muscle jerks (myoclonus), vision loss, ataxia |
| Variant CJD (vCJD) | Consumption of beef contaminated with Bovine Spongiform Encephalopathy (BSE) | 12 to 14 months | Early psychiatric symptoms, painful sensory disturbances, delayed neurological decline |
| Fatal Familial Insomnia (FFI) | Inherited mutation in the PRNP gene (or rarely sporadic) | 7 to 18 months | Progressive, untreatable inability to sleep, autonomic dysfunction, hallucinations, dementia |
| Gerstmann-Sträussler-Scheinker (GSS) | Inherited mutation in the PRNP gene | 2 to 10 years | Progressive loss of coordination (ataxia), slurred speech, late-onset cognitive decline |
| Kuru | Acquired via ritualistic funerary cannibalism in Papua New Guinea | 6 to 12 months | Severe tremors, loss of motor control, emotional instability, eventual inability to swallow |
Creutzfeldt-Jakob Disease (CJD) is the most common human prion disorder, affecting roughly one to two people per million globally each year. In the vast majority of cases, it occurs sporadically without any identifiable trigger; a single protein spontaneously misfolds, initiating the fatal cascade. Once neurological symptoms such as memory loss, behavioral changes, and impaired coordination appear, cognitive and physical decline is breathtakingly fast, typically leading to coma and death within a year.
Fatal Familial Insomnia (FFI) illustrates just how devastating localized prion damage can be. Caused by a specific dominant mutation in the PRNP gene, FFI targets the thalamus, the brain region responsible for regulating sleep-wake cycles and relaying sensory signals. Patients develop a worsening insomnia that resists all sedatives and sleeping medications. Deprived of restorative sleep, the body enters a state of permanent autonomic overdrive, characterized by rapid heart rate, excessive sweating, high blood pressure, and panic attacks, followed by hallucinations, severe weight loss, and total dementia before death inevitably occurs.
Kuru, though now virtually extinct following the cessation of ritualistic cannibalism among the Fore people of Papua New Guinea in the mid-20th century, provided crucial scientific proof that prion diseases could be transmitted orally. Kuru demonstrated that prions could remain dormant in the human body for incubation periods exceeding 40 to 50 years before suddenly triggering their 100% fatal neurological decline.
Rabies: The 100% lethal viral threshold
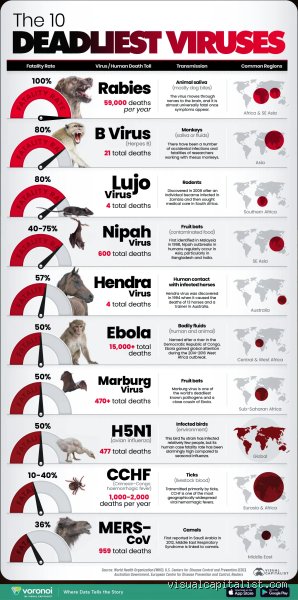
While prion diseases are universally fatal from the moment of biological onset, rabies occupies a unique and terrifying position in infectious disease medicine. Caused by neurotropic viruses of the genus Lyssavirus, rabies is 100% preventable prior to the onset of symptoms, yet virtually 100% fatal the moment clinical symptoms appear.
Rabies is a zoonotic disease transmitted primarily through the saliva of infected mammals, most commonly dogs globally, and wildlife such as bats, raccoons, skunks, and foxes in North America and Europe. What makes the rabies virus uniquely insidious is its stealthy journey through the nervous system. Unlike most viruses that enter the bloodstream and immediately provoke a massive immune alarm, the rabies virus stays hidden from immune surveillance. After entering the body through a bite or scratch, it binds to peripheral nerve endings near the wound site and begins traveling slowly up the axons toward the spinal cord and brain at a rate of roughly 8 to 20 millimeters per day.
During this incubation period, which typically lasts from one to three months, though it can range from less than a week to over a year depending on the distance between the wound and the brain, the infected person feels completely normal. Because the virus remains cloaked inside nerve cells, the immune system rarely mounts a significant response. However, this silent transit window is precisely why Post-Exposure Prophylaxis (PEP) is so extraordinarily effective. Thorough wound washing combined with rabies immunoglobulin (which provides immediate passive antibodies) and a series of rabies vaccines trains the immune system to intercept and destroy the virus before it reaches the central nervous system.
Crossing the point of no return
Once the rabies virus reaches the spinal cord and ascends into the brain, the window for intervention slams shut. The virus replicates rapidly within neurons, triggering acute, fatal encephalomyelitis. Paradoxically, autopsies of rabies victims often reveal relatively little physical destruction of brain cells compared to prion diseases; instead, the virus hijacks and scrambles neurotransmitter signaling, causing catastrophic functional failure of the brain and autonomic nervous system.
Clinical rabies manifests in two primary forms:
Furious Rabies (approx. 80% of cases): Characterized by extreme agitation, hyperactivity, confusion, hallucinations, and autonomic instability. It produces the classic, haunting symptoms of hydrophobia (fear of water) and aerophobia (fear of drafts of fresh air), caused by violent, painful involuntary spasms of the diaphragm and throat muscles whenever the patient attempts to swallow or feels air on their skin.
Paralytic Rabies (approx. 20% of cases): A quieter, more protracted form in which muscles gradually become paralyzed starting from the site of the bite, slowly progressing upward until the patient slips into a coma.
In both forms, death typically follows within two to ten days of symptom onset due to cardio-respiratory arrest. Across all of recorded medical history, fewer than 30 people worldwide have ever been documented to survive symptomatic rabies, and nearly all of those rare exceptions had either received partial vaccination prior to symptom onset or were subjected to experimental intensive care protocols (such as the controversial Milwaukee Protocol), often surviving with severe, permanent neurological damage. For all practical epidemiological purposes, once rabies symptoms begin, its fatality rate remains locked at 100%.
The mechanics of absolute letality: Prion diseases
To truly understand a condition with a 100% case fatality rate, one must look beyond conventional pathogens. Bacteria, viruses, fungi, and parasites rely on genetic material, DNA or RNA, to replicate and hijack host cells. Modern medicine possesses antibiotics, antivirals, and immune-boosting therapies designed to intercept these foreign invaders.
However, the group of conditions holding the undisputed record for a 100% fatality rate, transmissible spongiform encephalopathies (TSEs), commonly known as prion diseases, utilize an entirely different mechanism. Prions are neither living organisms nor viruses; they contain no genetic code whatsoever. Instead, they are misfolded proteins.
The human body naturally produces cellular prion proteins (PrPCPrP^CPrPC) predominantly in the nervous system. Their precise physiological function remains a subject of ongoing research, but they are generally harmless. The catastrophe begins when a rogue, misfolded prion (PrPScPrP^{Sc}PrPSc) enters the body or spontaneously forms via genetic mutation.
This rogue protein acts as a molecular template. Upon contacting a normal protein, it forces the healthy molecule to adopt its own aberrant, twisted shape. This triggers a devastating chain reaction: two become four, four become eight, cascading exponentially through neural tissue. Because the immune system recognizes these proteins as self-derived, it mounts no inflammatory response, leaving the rogue proteins to accumulate unchecked.
The pathological cascade: Turning the brain to sponge
As misfolded prions aggregate, they form microscopic amyloid plaques that disrupt cellular communication and cause massive neuronal death. Under a microscope, the affected brain tissue becomes riddled with holes, presenting a spongy, porous appearance, hence the term spongiform encephalopathy.
This physical degradation translates into a terrifying clinical picture depending on the specific prion disease variant:
Creutzfeldt-Jakob Disease (CJD): The most common human prion disease, manifesting as rapid progressive dementia, personality changes, memory loss, and involuntary muscle twitching (myoclonus).
Fatal Insomnia (FI): A genetic or sporadic condition that systematically destroys the thalamus, the brain's sleep-regulation center, leading to a total, unyielding inability to sleep, followed by autonomic failure and death.
Kuru: Historically prevalent among the Fore people of Papua New Guinea, spread through ritualistic mortuary cannibalism, characterized by severe tremors and uncontrolled emotional outbursts (the "laughing death").
Regardless of the specific variant or how it was acquired, whether sporadic, genetic, or acquired via contaminated surgical instruments or tissue, the trajectory is relentlessly progressive. The time from the onset of clinical symptoms to total neurological collapse and death is typically measured in months, or occasionally a few short weeks. There are zero documented cases of natural recovery from symptomatic CJD or fatal insomnia; medical intervention remains entirely palliative.
Why conventional medicine fails against prions
The absolute lethality of prion diseases stems from the extreme physical and chemical resilience of the infectious agent itself. Standard sterilization protocols designed to protect patients in medical settings, such as autoclaving surgical instruments at high heat, exposure to ultraviolet radiation, or treatment with chemical disinfectants like alcohol or formalin, fail to neutralize prions.
The misfolded protein's beta-sheet-rich structure is remarkably stable, resisting enzymatic degradation by proteases. Because they lack nucleic acids, methods that target viral or bacterial DNA/RNA are completely ineffective. Hospital equipment exposed to known or suspected prion cases often must be quarantined or destroyed outright to prevent hospital-acquired transmission.
The blood-brain barrier shields the central nervous system from most systemic therapeutics, and designing a drug that can safely dismantle a misfolded protein without disrupting the trillions of vital, correctly folded proteins in the human body represents one of pharmacology's most elusive challenges.
The frontier of Fatal pathology
While other conditions like untreated rabies or primary amoebic meningoencephalitis (caused by Naegleria fowleri) boast historical case fatality rates exceeding 97% to 99%, rare modern survival anomalies exist due to aggressive experimental interventions (such as the Milwaukee protocol for rabies or specialized drug combinations for amoebic infections).
Prion diseases stand entirely alone. They represent a chilling paradigm shift in pathology: a disease driven not by a living parasite or a replicating virus, but by the fundamental architecture of matter itself turning against the host. Until science discovers a way to safely reverse protein folding dynamics within the central nervous system, prion diseases maintain their grim, unyielding position at the absolute pinnacle of human mortality.