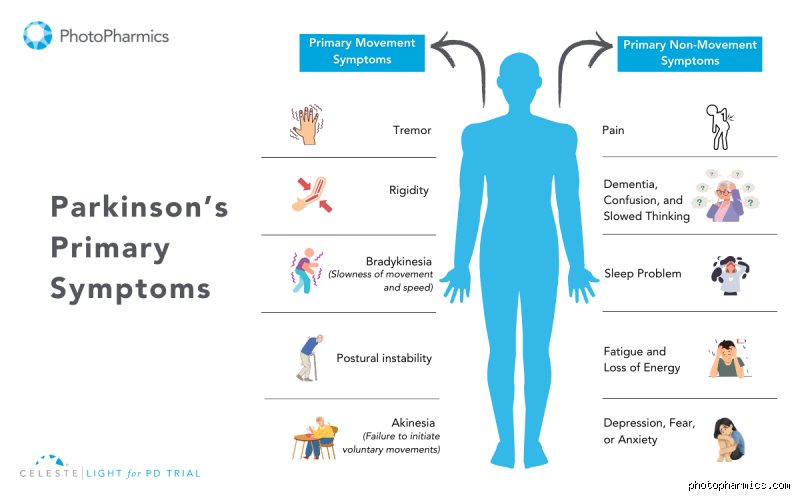
However, defining Parkinson’s disease solely by its motor symptoms is like describing a massive iceberg by looking exclusively at the small shard of ice jutting out above the surface of the ocean. Beneath that visible tip lies a sprawling, complex, and deeply impactful array of non-motor and atypical manifestations that profoundly alter daily life, alter psychological well-being, and complicate clinical management. In fact, medical research increasingly points to the reality that many of these hidden features do not merely accompany the disease—they often precede the onset of any noticeable motor symptoms by years, or even decades.
For patients, families, and healthcare providers, recognizing these less-understood facets is vital. Misattributing these issues to normal aging, stress, or entirely separate medical conditions can delay proper diagnosis and leave individuals struggling without appropriate interventions. To truly understand the breadth of this condition, we must look beyond the tremor and explore the complex systemic reach of the disease. This first part of our comprehensive expert exploration digs into the underlying framework of the condition and begins uncovering the subtle, surprising, and frequently overlooked symptoms that change the paradigm of what living with Parkinson’s truly means.
The neurological landscape: Why Parkinson’s is more than a Movement Disorder
To grasp why Parkinson’s manifests in such a diverse array of seemingly disconnected ways, one must first understand how the brain operates and what happens when neurodegeneration sets in. Dopamine is widely celebrated as the brain's "pleasure chemical," but in a functional neurological context, it acts as a master conductor for an intricate orchestra of circuits responsible for movement coordination, mood stabilization, autonomic regulation, sleep architecture, and cognitive processing.
When the neurons responsible for manufacturing dopamine gradually degenerate, the impact is systemic. Pathological changes in Parkinson’s are not restricted to the substantia nigra. Abnormal accumulations of a protein called alpha-synuclein, known as Lewy bodies, spread across various regions of the central and peripheral nervous systems. This includes areas controlling the gastrointestinal tract, the brainstem nuclei responsible for regulating sleep and blood pressure, and cortical regions tied to higher-level thinking and sensory integration.
Because the pathology is widespread, the clinical presentation is inherently multidisciplinary. A person living with Parkinson’s may successfully manage their motor stiffness with medication, only to find their quality of life profoundly disrupted by severe sleep disturbances, abrupt shifts in blood pressure, or a silent, progressive loss of the sense of smell. Acknowledging this broader clinical picture allows for a shift from reactive care to proactive, holistic disease management.
Unveiling symptom one: Anosmia (the silent disappearance of smell)
One of the most fascinating, yet consistently under-recognized, early indicators of Parkinson’s disease is anosmia, or a profound reduction and loss in the sense of smell (hyposmia). While losing one's sense of smell is commonly brushed aside as a temporary consequence of a sinus infection, seasonal allergies, or a common cold, when it occurs chronically and progressively without a clear upper respiratory cause, it can be an early red flag of neurodegeneration.
Clinical studies demonstrate that up to 75% to 90% of individuals with Parkinson’s experience a significant dampening of their olfactory faculties. What makes this symptom particularly compelling to neuroscientists is its timeline. Olfactory dysfunction often emerges years or even decades before any visible tremors, gait changes, or stiffness appear.
The Underlying Mechanism
Why does the nose stop working well before the limbs begin to shake? Current pathological models suggest that alpha-synuclein pathology often begins in areas of the brain and nervous system closely tied to sensory input and autonomic regulation. The olfactory bulb, the structure right behind the nasal cavity that processes smells, and the anterior olfactory nucleus are among the earliest sites impacted by Lewy body accumulation. Because the olfactory system has a direct, unmitigated pathway to the brain, it acts as an early victim of the disease process.
The impact on daily life
The loss of smell is far more than a minor inconvenience; it carries profound safety and quality-of-life implications. Individuals with severe anosmia cannot smell smoke from a fire, gas leaks from a stove, or spoiled food in the refrigerator, creating hidden domestic hazards. Human flavor is deeply intertwined with olfaction. When smell is compromised, food often tastes flat, cardboard-like, or unappealing, which can inadvertently lead to a loss of appetite, unintended weight loss, and nutritional deficiencies. Despite its early appearance, anosmia is frequently omitted from routine medical checkups, leaving patients unaware that their altered sense of smell is part of a larger neurological puzzle.
Unveiling symptom two: REM Sleep Behavior Disorder (RBD)
Sleep architecture is routinely fractured in neurodegenerative conditions, but one specific parasomnia stands out for its uncanny and direct link to Parkinson’s: REM Sleep Behavior Disorder (RBD).
During normal rapid eye movement (REM) sleep, the stage where vivid dreaming occurs, the brain normally induces a state of temporary muscle paralysis (atonia). This evolutionary safeguard prevents us from physically acting out our dreams, keeping us safely still while our minds navigate fantastical or intense scenarios. In individuals with RBD, however, this paralysis fails to activate.
Acting out the subconscious
People with RBD physically enact their dreams, often in dramatic, violent, or disruptive ways. This can manifest as punching, flailing, kicking, shouting, leaping out of bed, or grasping at the air during sleep. These episodes can be frightening for bed partners and dangerous for the patient, who risks injuring themselves or others against headboards, nightstands, or walls.
A critical diagnostic window
What elevates RBD from a standalone sleep disorder to a crucial lesser-known symptom of Parkinson’s is its predictive power. Longitudinal neurological studies indicate that a vast majority of individuals diagnosed with idiopathic (primary) REM Sleep Behavior Disorder will eventually develop Parkinson’s disease or a related alpha-synucleinopathy over time. It functions as a clinical harbinger, signaling that the brainstem circuits responsible for motor inhibition during sleep are already under siege by pathological protein aggregation. Recognizing RBD early opens up a vital window for monitoring, lifestyle modifications, and future neuroprotective clinical trials designed to slow disease progression before movement symptoms ever manifest.
Setting the stage for the deeper exploration
As we have seen, Parkinson’s disease extends far beyond the surface-level motor impairments that historically defined it. By examining features like early olfactory loss and dramatic nocturnal disturbances, we begin to appreciate the true complexity of this neurological condition.
In the continuation of this expert analysis, we will explore four additional hidden facets of the condition, ranging from autonomic nervous system failures and gastrointestinal disconnects to subtle cognitive shifts and hidden emotional hurdles, providing a complete, compassionate, and scientifically rigorous understanding of what it means to look beyond the tremor.
...Continuing from the exploration of the motor-centric definitions of Parkinson’s disease, we must look deeper into the complex landscape of non-motor and atypical clinical manifestations that frequently elude initial diagnostic scrutiny. While public perception remains tethered to resting tremors and progressive limb rigidity, the pathological progression of alpha-synuclein aggregation reaches far beyond the substantia nigra, impacting autonomic regulation, sensory processing, and cortical networks years before overt motor dysfunction materializes.
Symptom four: Dysautonomia and unexplained gastrointestinal distress
Long before a patient notices a change in their gait or a subtle tremor in their fingers, the enteric nervous system, often referred to as the body's "second brain", frequently bears the earliest brunt of pathological changes. Gastrointestinal dysfunction, particularly chronic and severe constipation, is one of the most prominent yet frequently underestimated non-motor signs of Parkinson's disease.
This is not ordinary, lifestyle-induced sluggishness; it stems from the degeneration of autonomic nerve fibers that coordinate smooth muscle contractions throughout the gastrointestinal tract. Slowed transit time can precede motor diagnoses by a decade. Coupled with dysautonomia, manifesting as unexplained fluctuations in blood pressure upon standing (orthostatic hypotension), sudden thermal regulation issues, and abnormal sweating patterns, these systemic disruptions highlight how deeply Parkinson's impacts the body's involuntary control networks. Clinicians are increasingly recognizing that persistent, treatment-resistant digestive and vascular irregularities in older adults warrant a broader neurological evaluation rather than isolated symptomatic treatments.
Symptom five: REM Sleep Behavior Disorder (RBD)
Sleep disturbances are ubiquitous in neurodegenerative conditions, but Rapid Eye Movement (REM) Sleep Behavior Disorder (RBD) holds a uniquely predictive relationship with Parkinson's disease. In a healthy nervous system, the brainstem actively paralyzes the body's skeletal muscles during REM sleep, preventing individuals from physically acting out their dreams.
In patients developing alpha-synucleinopathies, this protective atonia fails. Consequently, individuals begin thrashing, punching, kicking, vocalizing, or leaping out of bed during vivid, often action-packed or threatening dreams. Partners are frequently the first to identify the pattern, noting that the sleeper appears to be physically fighting or fleeing in their sleep. Longitudinal neurological studies indicate that a significant percentage of individuals diagnosed with idiopathic RBD will eventually convert to overt Parkinson's disease or related synucleinopathies, making it one of the most reliable windows for early prognostic assessment.
Symptom six: Anosmia and olfactory deficits
Perhaps the most paradoxical indicator of neurodegeneration is the profound loss of smell, known clinically as anosmia or hyposmia. Because olfactory changes do not directly impair physical movement, they are rarely brought up spontaneously during routine medical examinations. Patients often only realize the deficit retrospectively when they notice they can no longer perceive the scent of coffee, flowers, or spices.
Pathologically, the olfactory bulb and anterior olfactory nucleus are among the very first regions in the central nervous system to accumulate Lewy bodies. The progressive loss of chemical sensory perception can manifest years or even decades prior to any diagnostic motor milestones. While olfactory deficits can stem from chronic sinus issues, aging, or viral infections, a progressive, unexplained fading of smell combined with minor systemic or sleep anomalies provides a critical clue for early identification.
Moving toward comprehensive care
Recognizing these lesser-known manifestations, ranging from early autonomic and sensory shifts to complex sleep architecture breakdowns, fundamentally transforms how modern medicine approaches neurodegenerative conditions. By looking past the visible tremor and shifting focus toward the systemic multi-system nature of the disease, researchers and clinicians can better support diagnostic accuracy, target symptom management more effectively, and improve overall quality of life for individuals navigating these complex medical journeys.