The tipping point: Transitioning from stability to crisis
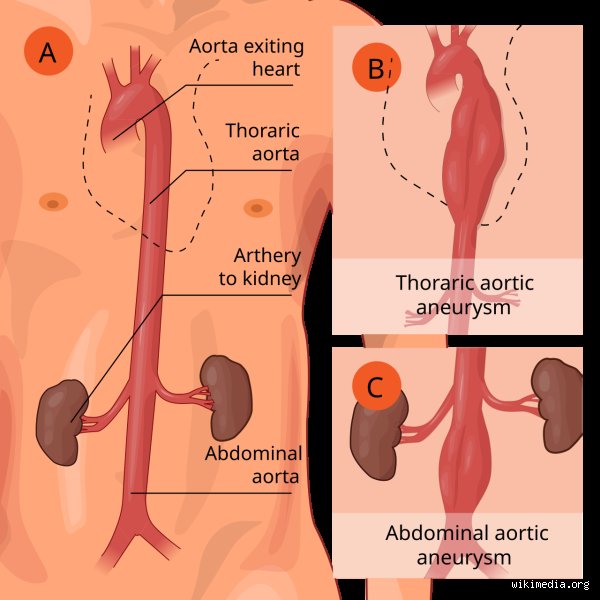
When tracking the structural integrity of the aorta, the timeline from a stable expansion phase to a catastrophic event is governed by physics, material fatigue, and biological stress. While smaller aneurysms may remain stable over many years, enlarging at an average rate of roughly one millimeter to two millimeters per year, the structural dynamics shift dramatically once the vessel crosses critical size thresholds—typically around 5.0 to 5.5 centimeters for abdominal aortic aneurysms.
As the diameter increases, the tension on the wall multiplies according to the law of Laplace, meaning that the physical force pulling the arterial wall apart escalates even if blood pressure remains constant. This nonlinear increase in wall stress explains why growth rates are rarely constant; larger aneurysms frequently expand faster than small ones, compounding the risk of mechanical failure.
Recognizing the warning signs of impending failure
Before a complete, catastrophic rupture occurs, the weakened aortic wall often undergoes a phase of microscopic tearing or minor localized bleeding, known as a contained rupture or impending rupture. During this window—which may last anywhere from a few hours to a couple of days, the body attempts to contain the hemorrhage, sending out urgent physiological distress signals.
Patients experiencing this transitional phase commonly report sudden, severe, and unrelenting pain. Unlike the dull, chronic ache associated with slow expansion, this pain is characteristically sharp, tearing, or stabbing, frequently radiating intensely into the lower back, flanks, or abdomen.
Alongside localized pain, systemic symptoms of acute internal blood loss begin to manifest. These warning signs include:
Sudden, unexplained lightheadedness, dizziness, or fainting spells
A rapid, thumping heart rate paired with a sudden drop in blood pressure
Clammy, pale skin and an overwhelming sense of impending doom
Sudden weakness or numbness in the lower extremities due to compromised blood flow
These clinical manifestations demand immediate emergency intervention, as they signify that the margin between containment and total circulatory collapse has vanished.
The window for intervention and modern outcomes
The timeline from the onset of a full rupture to fatal exsanguination can be terrifyingly brief, often measured in minutes to hours. This stark reality underscores why proactive surveillance and elective surgical repair are vital. By identifying expanding vessels through routine screening or imaging before they reach the critical failure threshold, medical teams can perform scheduled repairs via open surgical grafting or minimally invasive endovascular aneurysm repair (EVAR).
Understanding how long an aneurysm can persist before rupture is less about predicting a precise calendar date and more about respecting the physiological boundaries of weakened tissue. Through vigilant monitoring of growth rates, strict blood pressure regulation, and timely surgical planning, the timeline can be interrupted long before the vessel reaches its breaking point.