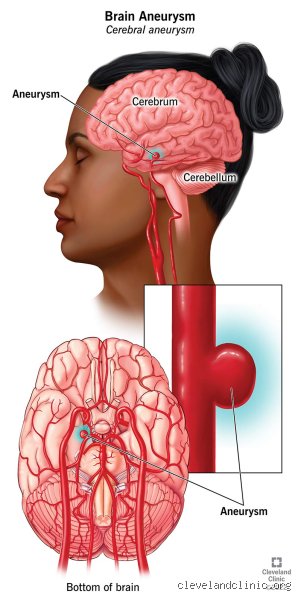
The question, "Can you survive if an aneurysm bursts?", is one of the most consequential inquiries in modern neurology and emergency medicine. The short answer is yes: people do survive ruptured brain aneurysms every day. But that survival is rarely a matter of luck alone; it is a complex intersection of rapid diagnosis, advanced neurosurgical intervention, patient age, overall health, and the sheer anatomical location of the bleed within the intricate vascular network of the brain.
1. The anatomy of a weakness: What exactly is an aneurysm?
To understand how survival is possible after a rupture, one must first understand what an aneurysm is and how it forms. The human brain is an energy-intensive organ, demanding a constant, highly regulated supply of oxygenated blood. This blood is delivered via a dense, complex network of arteries that wind along the base of the brain, most notably within a circular vascular structure known as the Circle of Willis.
The walls of these cerebral arteries are composed of multiple layers of tissue designed to withstand the high pressure of pulsating blood pumped directly from the heart. However, at certain vulnerable points, typically at the bifurcations or branching junctions where blood flow changes direction abruptly, the muscular middle layer of the arterial wall can be congenitally thin or weaken over time due to hemodynamic stress, hypertension, atherosclerosis, or trauma.
When this localized weakening occurs, the inner lining of the artery balloons outward under arterial pressure, creating a fluid-filled pouch resembling a small berry on a stem. This is a saccular (or berry) aneurysm, the most common type found in the intracranial circulation.
As long as the wall of this pouch maintains its structural integrity, the patient may remain completely asymptomatic. But if the forces acting against the wall, systolic blood pressure, vessel wall degradation, inflammation, and mechanical stress, exceed the tensile strength of the tissue, the wall tears. The blood escapes into the subarachnoid space (the area between the brain and the thin tissues that cover it), triggering a subarachnoid hemorrhage (SAH).
2. The grim statistics: Breaking down survival rates
When examining survival rates for a ruptured brain aneurysm, medical literature paints a sobering picture, though one that has steadily improved over the past several decades thanks to advances in neurocritical care and endovascular techniques.
Historically, and even in modern global health statistics, the mortality associated with a ruptured aneurysm is notoriously high:
Immediate Mortality: Approximately 10% to 15% of patients with a ruptured aneurysm die before ever reaching a hospital, succumbing to the massive initial surge of intracranial pressure and brain tissue damage.
First 30 Days: Among those who make it to a medical facility, roughly 40% to 50% do not survive the first 30 days following the event due to secondary complications such as vasospasm, hydrocephalus, or re-bleeding.
Long-Term Outcomes: Of the survivors who make it past the critical initial window, about half suffer permanent neurological, cognitive, or psychological deficits that impair their daily independence and quality of life.
These statistics, while daunting, must be contextualized. They represent aggregate populations across all age groups, health statuses, and geographic locations with varying access to specialized care. For a younger, otherwise healthy patient who receives immediate treatment at a comprehensive stroke center equipped with a dedicated neuro-intensive care unit, the odds of survival and meaningful functional recovery are significantly higher than the baseline population averages.
3. The cascading crisis: What happens inside the skull?
Survival depends not only on stopping the initial hemorrhage but also on managing the devastating cascade of secondary events that occur inside the closed box of the skull. The human skull is a rigid encasement with a fixed volume, containing brain tissue (~80%), cerebrospinal fluid (CSF) (~10%), and blood (~10%), a physiological principle known as the Monro-Kellie doctrine.
When a blood vessel ruptures inside this restricted space, the introduction of high-pressure arterial blood drastically disrupts this delicate equilibrium:
Intracranial Pressure (ICP) Spike: The sudden pooling of blood increases pressure inside the skull, compressing vital brain structures and temporarily or permanently interrupting normal cerebral perfusion pressure.
Ischemia and Cell Death: Because blood is toxic to delicate neural tissue, the escaped blood triggers intense inflammation, cellular destruction, and localized ischemia (lack of blood flow) as normal microvascular pathways are choked off.
Cerebral Vasospasm: Between 4 to 14 days post-rupture, the breakdown products of the escaped blood can cause the major cerebral arteries to violently constrict (vasospasm). This secondary constriction can restrict blood flow to vast regions of the brain, causing delayed ischemic strokes long after the initial aneurysm has been secured.
Hydrocephalus: Blood can block the normal absorption pathways of cerebrospinal fluid, causing fluid to accumulate in the brain's ventricles (hydrocephalus), which further elevates pressure and requires surgical drainage via an external ventricular drain (EVD) or shunt.
4. Recognizing the catastrophe: The "thunderclap" warning
Time is the single most critical determinant of survival and recovery when an aneurysm ruptures. Every minute that passes without intervention increases the risk of re-bleeding and irreversible brain injury. Yet, recognizing a rupture can be deceptively difficult for bystanders and patients alike because the presentation is often distinct from traditional ischemic strokes.
The hallmark symptom of a ruptured cerebral aneurysm is a thunderclap headache, classically described by patients who survive as “the worst headache of my life.” Unlike a typical migraine or tension headache that builds in intensity over hours, a thunderclap headache strikes with maximum ferocity in a fraction of a second, feeling as though someone has struck the back of the head with a baseball bat.
Other cardinal signs and symptoms accompanying a rupture include:
Nausea and Vomiting: Resulting from sudden, severe increases in intracranial pressure.
Stiff Neck: Irritation of the meninges by blood in the subarachnoid space mimics the signs of meningitis.
Photophobia: Extreme sensitivity to light.
Neurological Deficits: Sudden confusion, altered mental status, slurred speech, weakness on one side of the body, or numbness.
Cranial Nerve Palsies: A sudden drooping eyelid or double vision, which often occurs because an enlarging or bleeding aneurysm compresses the third cranial nerve (oculomotor nerve).
Loss of Consciousness: Ranging anywhere from brief fainting spells to deep, prolonged coma.
5. Risk factors: Why do aneurysms form and rupture?
Understanding who is most at risk helps clinicians identify vulnerable individuals before a catastrophic rupture occurs. While anyone can develop a cerebral aneurysm, certain genetic, environmental, and lifestyle factors substantially increase both formation and rupture risk.
Hypertension (High Blood Pressure): Chronic high blood pressure places unremitting mechanical stress on the arterial walls, accelerating wear and tear at vulnerable vascular junctions.
Smoking: Cigarette smoking is one of the strongest modifiable risk factors for both the formation and the rupture of brain aneurysms. Chemicals in tobacco smoke damage endothelial cells and promote destructive inflammatory responses within blood vessel walls.
Family History: Individuals with a first-degree relative (parent, sibling, child) who has suffered an intracranial aneurysm or subarachnoid hemorrhage face a significantly elevated risk, suggesting underlying genetic predispositions in connective tissue integrity.
Connective Tissue Disorders: Rare genetic syndromes, such as Ehlers-Danlos syndrome (Type IV), Marfan syndrome, and autosomal dominant polycystic kidney disease (ADPKD), are strongly associated with structural weakness in arterial walls.
Substance Abuse: The use of powerful sympathomimetic drugs, particularly cocaine and amphetamines, causes acute, violent spikes in blood pressure that can precipitate the immediate rupture of an existing, fragile aneurysm.
The acute phase: Securing the aneurysm and stabilizing the patient
When a brain aneurysm ruptures, causing a subarachnoid hemorrhage (SAH), the immediate medical priority shifts from diagnosis to urgent stabilization and aneurysm securing. The primary and most terrifying risk in the hours immediately following a rupture is a second bleed, known as rebleeding, which carries an overwhelmingly high mortality rate. Consequently, neuro-intensive care units (neuro-ICUs) operate with extreme urgency. Patients are closely monitored for airway protection, blood pressure regulation, and intracranial pressure management.
Medical teams must strike a delicate balance with blood pressure: it must be kept high enough to maintain cerebral perfusion (ensuring oxygen reaches vital brain tissues) but low enough to prevent further tearing of the compromised blood vessel wall. Once the patient is stabilized, definitive intervention to seal off the ruptured aneurysm is initiated, typically within the first 24 to 48 hours.
Treatment pathways: Endovascular Coiling versus Microsurgical Clipping
The two gold-standard interventions used to secure a ruptured aneurysm are endovascular coiling and microsurgical clipping. The choice between these two approaches depends heavily on the aneurysm’s anatomical features, its location, size, and shape, as well as the patient's overall clinical grade and medical history.
Endovascular Coiling: This is a minimally invasive procedure performed by a neuro-interventional radiologist. A catheter is inserted through a puncture site, usually in the femoral artery in the groin or the radial artery in the wrist, and threaded carefully through the vascular network up into the brain's blood vessels. Once inside the aneurysm sac, the surgeon deploys tiny platinum coils. These coils fill the cavity, induce localized blood clotting, and permanently block the aneurysm off from the main blood circulation. Coiling avoids an open skull incision, often resulting in shorter initial procedures and a faster short-term recovery phase. However, because coils can occasionally compact over time, long-term monitoring via follow-up brain imaging is essential to check for recurrence.
Microsurgical Clipping: This is a traditional open neurosurgical procedure requiring a craniotomy, temporarily removing a precise section of the skull. Operating under a high-powered surgical microscope, the neurosurgeon meticulously navigates around delicate brain tissue to locate the base or "neck" of the aneurysm. A tiny, spring-loaded titanium clip is then placed directly across the neck, permanently pinching it shut and stopping blood flow into the sac while preserving the surrounding healthy arteries. Clipping is celebrated for its long-term durability; once clipped, an aneurysm rarely reopens. It is often preferred for wide-necked aneurysms, certain complex shapes, or cases where a large intracerebral blood clot must be evacuated simultaneously.
Managing secondary complications: Vasospasm and hydrocephalus
Surviving the initial rupture and subsequent treatment is only the first hurdle. The days following a subarachnoid hemorrhage are fraught with secondary physiological hazards that can profoundly impact the final outcome. Two of the most formidable complications are cerebral vasospasm and hydrocephalus.
Cerebral vasospasm typically sets in between 3 to 14 days after the rupture. As blood breaks down in the subarachnoid space, it irritates the cerebral blood vessels, causing them to dangerously constrict. This narrowing can severely restrict blood flow, starving brain cells of oxygen and triggering a secondary ischemic stroke. Neuro-ICUs actively monitor patients using transcranial Doppler ultrasound and deploy specialized medications (such as calcium channel blockers) or endovascular balloon angioplasty to keep vessels dilated.
Hydrocephalus occurs when the normal circulation of cerebrospinal fluid (CSF) is blocked by blood products, leading to a buildup of fluid and dangerous pressure inside the ventricular system of the brain. To relieve this pressure, neurosurgeons may place an external ventricular drain (EVD) or a permanent shunt to divert excess fluid.
The long road of rehabilitation and recovery
For those who navigate the treacherous waters of the acute phase and secondary complications, recovery transitions into a marathon rather than a sprint. The impact of a ruptured aneurysm extends far beyond the physical sealing of the blood vessel; the blood extravasation itself injures surrounding brain parenchyma.
Rehabilitation is inherently multidisciplinary, tailored to the specific cognitive, emotional, and physical deficits experienced by the patient. Physical therapy addresses balance, motor skills, and endurance, while occupational therapy focuses on regaining independence in activities of daily living. Because a brain bleed often affects executive functions, memory, processing speed, and emotional regulation, neuropsychological rehabilitation is indispensable. Patients and their families frequently encounter invisible challenges, such as fatigue, anxiety, depression, and personality changes, which require compassionate, sustained therapeutic support.
Prognosis and quality of life: What survival really looks like
Statistical realities regarding ruptured aneurysms are sobering, yet they carry room for profound resilience. Historically, roughly 30% to 50% of individuals who suffer a ruptured brain aneurysm do not survive the initial event or the immediate aftermath, with many succumbing before ever reaching a hospital. Among those who do make it to definitive medical care and survive treatment, a significant percentage experience varying degrees of long-term disability.
However, modern neuro-intensive care, advanced surgical techniques, and early intervention have significantly shifted these trajectories. Many survivors achieve a high degree of independence and return to meaningful, productive lives, particularly younger patients or those who presented in better clinical condition at the time of admission. Quality of life outcomes depend heavily on the promptness of medical intervention, the volume of the initial bleed, and the rigorous management of complications during the hospital stay.
Vigilance, medical advancements, and hope
Surviving a burst aneurysm is proof of the resilience of the human body, the precision of modern neurosurgery, and the tireless vigilance of critical care teams. While the phrase "ruptured aneurysm" evokes profound fear, understanding the realities of survival, treatment options, and the recovery process demystifies this medical crisis. Continued advancements in endovascular devices, neuro-imaging, and post-operative management continue to improve survival curves and functional outcomes year after year. For survivors and their families, recovery demands patience, adaptability, and comprehensive support, transforming a catastrophic medical emergency into a journey of profound healing and renewed life.