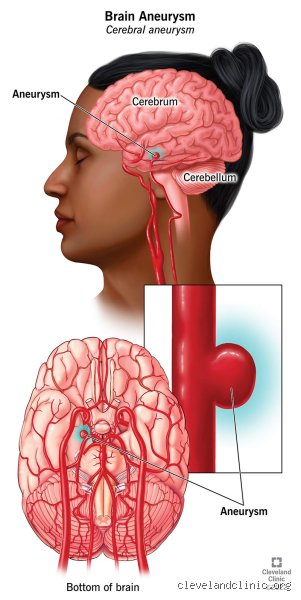
To understand the lethal potential of this condition, it's important to note what a brain aneurysm actually is. A brain aneurysm—often referred to as an intracranial or cerebral aneurysm—is a localized, balloon-like bulge or weakness in the wall of an artery within the brain. This structural vulnerability typically develops at the branching points of major arteries at the base of the brain, a region known anatomically as the Circle of Willis. Over time, constant hemodynamic stress, systemic hypertension, and structural degradation of the arterial wall can cause this weakened section to expand, thin out, and ultimately breach. When the wall fails entirely, blood escapes violently into the subarachnoid space, the fluid-filled area between the brain and the thin tissues that cover it, resulting in what medical professionals classify as an acute subarachnoid hemorrhage (SAH).
The moment an aneurysm ruptures, the physiological consequences are immediate and profoundly dangerous. Moreover, the sudden influx of arterial pressure blood into the confined vault of the skull causes an immediate, dramatic spike in intracranial pressure (ICP). This acute surge compresses delicate neural tissue, disrupts normal cerebral perfusion, and can precipitate rapid loss of consciousness, coma, or sudden cardiac arrest. Patients often describe the experience as the "worst headache of my life," an abrupt and agonizing symptom colloquially referred to as a thunderclap headache. Alongside this excruciating head pain, individuals frequently experience nausea, vomiting, stiff neck, photophobia, and focal neurological deficits depending on the exact location of the rupture within the cerebral vasculature.
The statistical reality surrounding ruptured brain aneurysms underscores their extreme lethality. Clinical studies and epidemiological data consistently show that approximately 50% of people who suffer a ruptured brain aneurysm will not survive the initial event or the immediate aftermath. Of those who make it to a hospital alive, a significant percentage still face high rates of long-term morbidity and mortality due to secondary complications. Furthermore, the window for effective medical intervention is vanishingly narrow, requiring rapid emergency medical services, advanced neuroimaging such as CT angiography, and immediate neurosurgical or endovascular intervention to secure the aneurysm and prevent re-bleeding.
To appreciate the broader picture of cerebrovascular health, we must examine the complex tapestry of risk factors that contribute to aneurysm formation and subsequent rupture. While some risk factors are entirely beyond an individual's control, such as congenital connective tissue disorders, polycystic kidney disease, or a robust family history of cerebral aneurysms, many significant contributors are lifestyle and environmentally mediated. Chronic hypertension, cigarette smoking, excessive alcohol consumption, and the use of illicit stimulants like cocaine place an extraordinary amount of shear stress on cerebral blood vessels. By identifying these modifiable risk factors and managing systemic blood pressure rigorously, medical practitioners can mitigate baseline vulnerabilities before a rupture occurs.
In conclusion, the danger posed by a ruptured intracranial aneurysm cannot be overstated. It is a life-threatening medical emergency where every minute counts, carrying a notoriously high mortality rate and the potential for lifelong cognitive and physical impairment. Recognizing warning signs, understanding the underlying vascular mechanics, and prioritizing rapid emergency response are essential steps in combating the devastating impacts of this condition.
The critical path to medical intervention
When a cerebral aneurysm bursts, the immediate priority shifts to stabilizing the patient and securing the compromised blood vessel to prevent further hemorrhage. Emergency medical services transport the individual to a specialized neurological center where diagnostic imaging, such as a CT angiogram, maps the exact location and size of the vascular defect. Rapid intervention is crucial because a significant percentage of patients do not survive the first twenty-four hours without prompt clinical management. Neurologists and neurosurgeons work collaboratively to control intracranial pressure and mitigate the immediate threats posed by the sudden pooling of blood.
Question 2?
What are the primary surgical options used to secure a ruptured cerebral aneurysm? Neurosurgeons typically choose between surgical clipping, which involves placing a tiny metal clip across the base of the aneurysm via an open craniotomy, and endovascular coiling, a minimally invasive approach where platinum coils are threaded through a catheter to block blood flow. Both techniques aim to permanently isolate the weakened pouch from the main arterial circulation. Selecting the optimal procedure depends heavily on the aneurysm's unique anatomical location, its geometric shape, and the overall clinical stability of the patient.
Managing secondary complications and Long-Term recovery
Even after the initial rupture is successfully treated, patients face a vulnerable recovery window characterized by severe secondary risks. Vasospasm, the sudden constriction of blood vessels, frequently occurs days after the event, potentially starving healthy brain tissue of essential oxygen and causing secondary strokes. Medical teams closely monitor fluid balances, electrolyte levels, and intracranial pressure to prevent complications like hydrocephalus, where cerebrospinal fluid accumulates hazardously within the brain's cavities.
Rehabilitation forms a cornerstone of long-term survival for those who navigate the initial crisis. Physical therapy, occupational therapy, and speech-language pathology help patients relearn vital functions and manage lasting cognitive or physical impairments. While the journey requires extensive medical oversight and personalized support networks, early detection and state-of-the-art neurological care continue to improve survival trajectories for affected individuals.