The biology, biomarkers, and diagnostic landscape of systemic immune responses
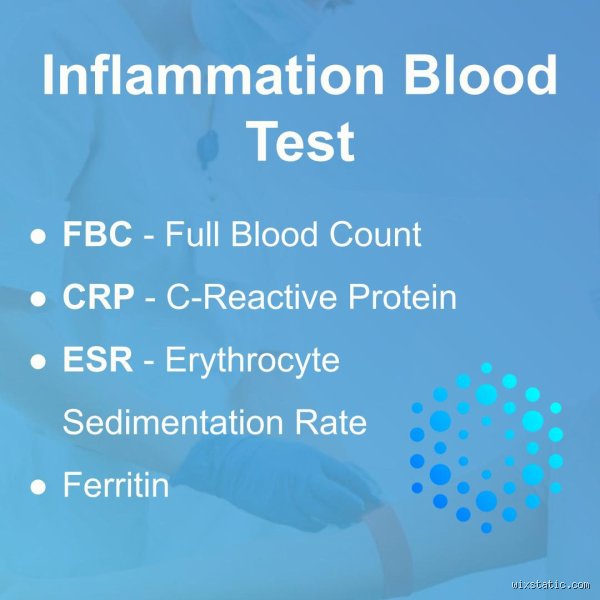
Given its invisible and systemic nature, a central question arises for clinicians and patients alike: Can a blood test reveal inflammation?
The short answer is an unequivocal yes. While blood tests cannot always pinpoint the precise anatomical location or the exact underlying trigger of inflammatory processes without further clinical context, they are exceptionally powerful tools for detecting systemic inflammatory markers. This comprehensive first part of our expert exploration digs into the physiological mechanisms of inflammation, the primary biomarkers quantified in clinical laboratories, and how modern medicine interprets these molecular signals.
1. The dual nature of Inflammation: Acute versus Chronic
To understand what blood tests reveal, one must first distinguish between the two primary forms of inflammation:
Acute Inflammation: This is the body’s immediate, short-term response to harmful stimuli. When you cut your finger, sprain an ankle, or contract influenza, the immune system dispatches white blood cells, plasma proteins, and fluid to the affected site. This results in the classic clinical signs: rubor (redness), calor (heat), tumor (swelling), dolor (pain), and functio laesa (loss of function). Once the threat is neutralized or the tissue heals, the acute response subsides.
Chronic Inflammation: In contrast, chronic inflammation is a prolonged, dysregulated immune response where the body continues to send inflammatory cells and chemicals even when there is no outside danger. Over time, this persistent internal stress can damage healthy cells, tissues, and organs. Because chronic inflammation is often asymptomatic in its early stages, clinicians rely heavily on blood biomarkers to detect its presence before irreversible damage occurs.
Because blood circulates throughout the entire body, it acts as a chemical mirror reflecting systemic immune activity. When tissues become inflamed—whether due to an infection, an autoimmune flare, or metabolic stress—they release signaling molecules into the bloodstream, triggering measurable alterations in blood composition.
2. The molecular cascade: How inflammatory signals reach the bloodstream
When tissue injury, cellular stress, or microbial invasion occurs, local immune cells (such as macrophages and mast cells) release specialized signaling proteins known as cytokines and chemokines. Prominent pro-inflammatory cytokines include Tumor Necrosis Factor-alpha (TNF-α\alphaα), Interleukin-1 beta (IL-1$\beta$), and Interleukin-6 (IL-6).
These cytokines travel via the circulatory system to various organs, most notably the liver. Upon receiving signals like IL-6, the liver rapidly alters its protein synthesis profile, ramping up the production of acute-phase reactants. These are proteins whose plasma concentrations rise (positive acute-phase reactants) or fall (negative acute-phase reactants) in response to inflammation.
By measuring the concentrations of these acute-phase reactants and evaluating cellular components in the blood, laboratory diagnostics can quantify the magnitude of the inflammatory response.
3. Key biomarkers: C-Reactive Protein (CRP) and High-Sensitivity CRP (hs-CRP)
Among the most well-established and frequently ordered tests for systemic inflammation is the C-Reactive Protein (CRP) assay.
Standard CRP: Discovered in the 1930s, standard CRP is a ring-shaped, pentameric protein synthesized by the liver. Its levels can rise dramatically, often by a factor of 1,000 or more, within hours of severe tissue injury, bacterial infection, or acute trauma. Standard CRP is exceptionally useful for monitoring acute conditions, such as tracking recovery from surgery, evaluating acute flare-ups of inflammatory bowel disease, or detecting bacterial infections in hospitalized patients.
High-Sensitivity CRP (hs-CRP): For assessing chronic, low-grade vascular and systemic inflammation, particularly in the context of cardiovascular risk stratification, standard CRP lacks the necessary analytical sensitivity. The high-sensitivity CRP test measures minute quantities of the protein in the blood (expressed in milligrams per liter, mg/L).
Clinical cardiology relies heavily on hs-CRP thresholds to evaluate cardiovascular risk:
Low Risk: Less than 1.0 mg/L
Average Risk: 1.0 to 3.0 mg/L
High Risk: Greater than 3.0 mg/L
Elevated hs-CRP in the absence of acute infection suggests ongoing, low-grade arterial wall inflammation, which plays a central role in atherosclerosis, the buildup of plaques in the arteries.
4. The Erythrocyte Sedimentation Rate (ESR)
Another classic, non-specific marker of inflammation is the Erythrocyte Sedimentation Rate (ESR), often referred to colloquially as a "sed rate."
Unlike CRP, which measures a specific circulating protein, the ESR measures the physical rate at which red blood cells (erythrocytes) settle to the bottom of a vertical, calibrated tube over the course of one hour.
The Biophysics of Sedimentation
Normally, red blood cells possess a negative electrical charge (zeta potential), causing them to repel one another and remain suspended individually in plasma. However, during systemic inflammation, elevated levels of large, asymmetrical acute-phase proteins, especially fibrinogen, coat the red blood cells. This coating reduces their negative charge, causing them to clump together in stacks called rouleaux formation. Because these aggregated clumps are denser than individual cells, they fall more rapidly through the plasma.
Clinical utility and limitations
While ESR has been a cornerstone of clinical rheumatology for decades, used to monitor conditions like rheumatoid arthritis, polymyalgia rheumatica, and giant cell arteritis, it is notoriously non-specific. Numerous non-inflammatory factors can elevate ESR, including:
Advanced age
Pregnancy
Anemia
Renal disease
Technical variations in laboratory handling
Consequently, ESR is rarely interpreted in isolation; it is evaluated alongside clinical symptoms and more specific biomarker panels.
5. Complete Blood Count (CBC) and cellular signatures
Inflammation is fundamentally driven and sustained by immune cells. Therefore, a Complete Blood Count (CBC) with differential provides vital clues regarding an ongoing inflammatory or infectious process.
Leukocytosis (Elevated White Blood Cell Count): An elevation in total white blood cells (WBCs) often signals an acute immune response. The differential breakdown provides further insight:
Neutrophils: Typically elevate rapidly in response to acute bacterial infections, tissue necrosis, or physiological stress.
Lymphocytes: Often increase during viral infections, though certain chronic inflammatory conditions also alter lymphocyte subsets.
Eosinophils and Basophils: Frequently elevate during allergic reactions, parasitic infections, or specific autoimmune disorders.
Platelet Count and Mean Platelet Volume (MPV): Platelets are not only crucial for hemostasis but also function as active immune cells that release inflammatory mediators. Chronic systemic inflammation frequently stimulates bone marrow production of platelets, leading to reactive thrombocytosis.
Anemia of Chronic Disease (Anemia of Inflammation): Persistent systemic inflammation alters iron metabolism via the liver peptide hormone hepcidin. Hepcidin traps iron within storage macrophages, making it unavailable for developing red blood cells. A CBC may reveal a normocytic or microcytic anemia secondary to chronic inflammatory signaling.
Summary of Part 1
Blood tests are exceptionally capable of revealing whether systemic inflammation is present within the body. Through the quantitative analysis of acute-phase reactants like CRP and hs-CRP, physical markers like ESR, and cellular shifts in a Complete Blood Count, modern laboratory medicine can detect both acute infectious processes and insidious, chronic low-grade inflammation.
However, detecting that inflammation exists is only the first step. In the upcoming second part of this expert article, we will explore advanced biomarker panels, the diagnostic challenges of non-specificity, and how clinicians translate these laboratory findings into targeted therapeutic and lifestyle interventions.
Interpreting the results: Beyond the binary
When your laboratory report arrives, it is easy to fixate on a single binary question: Is the number normal, or is it high? However, clinical interpretation is rarely that straightforward. Because markers like C-reactive protein (CRP) and the erythrocyte sedimentation rate (ESR) are entirely non-specific, a physician must weigh the quantitative value against a patient's clinical presentation, medical history, and recent life events.
To put this into perspective, consider how different magnitudes of elevation shift a clinician's perspective:
| Marker Level | Typical Clinical Implication | Common Contributing Factors |
|---|---|---|
| Normal / Low (< 3 mg/L for CRP) | Absence of significant acute systemic inflammation | Baseline healthy state, effective remission of chronic disease |
| Mild Elevation (3–10 mg/L for CRP; slight ESR rise) | Low-grade, chronic, or localized activation | Obesity, mild insulin resistance, sedentary lifestyle, localized dental inflammation, aging |
| Moderate Elevation (10–50 mg/L for CRP) | Active inflammatory or infectious state | Acute viral infections, localized bacterial infections, early rheumatoid flare, tissue trauma |
| Marked Elevation (> 50 mg/L to several hundred) | Severe systemic stress or acute tissue destruction | Acute bacterial sepsis, major trauma, severe autoimmune vasculitis, advanced tissue necrosis |
False positives are remarkably common. A recent heavy workout, pregnancy, minor trauma (like a stubbed toe or dental cleaning), sleep deprivation, or a passing common cold can temporarily push inflammatory markers out of the reference range. Conversely, a patient can harbor significant localized inflammation, such as early-stage osteoarthritis or localized bowel irritation, while maintaining completely normal systemic blood levels.
Specialized markers and advanced Testing
While standard CRP and ESR serve as the frontline workhorses of pathology laboratories, modern medicine frequently relies on more specialized biomarkers to pinpoint clinical risk or investigate complex presentations.
High-Sensitivity CRP (hs-CRP): This specialized assay measures CRP at much lower concentrations (down to 0.1 mg/L). Rather than hunting for an infection or a major autoimmune flare, hs-CRP is used in cardiology to evaluate low-grade vascular inflammation. Because atherosclerosis is fundamentally an inflammatory disease of the arterial wall, persistent micro-elevations in hs-CRP help stratify an individual's long-term cardiovascular risk, independent of traditional cholesterol panels.
Procalcitonin (PCT): Particularly valuable in emergency and critical care settings, procalcitonin rises sharply in response to bacterial infections while remaining largely unaffected by viral infections or non-infectious inflammation. This specificity allows clinicians to make rapid, evidence-based decisions regarding whether to prescribe antibiotics.
Cytokines and Chemokines: Molecules such as Interleukin-6 (IL-6), Tumor Necrosis Factor-alpha (TNF-α\alphaα), and various interferons act as the primary master switches of the immune response. Although routine measurement of cytokines is uncommon in standard practice due to cost and rapid fluctuation, they are instrumental in specialized immunology, oncology, and the management of patients undergoing targeted biologic therapies.
The landscape of Chronic Low-Grade Inflammation
In recent decades, medical research has shifted focus from acute, dramatic flare-ups to a more insidious phenomenon: chronic low-grade systemic inflammation. Unlike the fiery immune response triggered by a deep wound or bacterial pneumonia, low-grade inflammation simmers quietly in the background over months and years.
This smoldering state is intimately tied to modern lifestyle factors and metabolic health. Visceral adipose tissue, the deep fat surrounding internal organs, is not inert storage; it functions as an active endocrine organ, constantly pumping out pro-inflammatory cytokines like IL-6 and TNF-α\alphaα. Consequently, conditions such as metabolic syndrome, insulin resistance, non-alcoholic fatty liver disease, and chronic psychological stress frequently manifest as persistent, low-level elevations in hs-CRP.
Addressing this type of inflammation requires looking far beyond a prescription pad. Clinical strategies focus heavily on lifestyle modifications that dampen immune hyperactivity:
Nutritional Adjustments: Emphasizing whole, unprocessed foods rich in antioxidants and omega-3 fatty acids while minimizing refined sugars and trans fats.
Body Composition: Gradual reduction of visceral adiposity through consistent physical activity and caloric balance.
Restorative Sleep: Correcting sleep fragmentation and chronic sleep deprivation, both of which trigger inflammatory pathways.
Stress Management: Mitigating chronic activation of the hypothalamic-pituitary-adrenal (HPA) axis through mindfulness, behavioral therapy, and stress-reduction techniques.
Navigating the diagnostic maze: What happens next?
If you undergo a blood test and your physician reports an elevated inflammatory marker, the result should be viewed as an invitation to investigate rather than a definitive diagnosis. The diagnostic journey typically follows a logical, step-by-step framework:
Rule Out Transient Causes: If you felt completely healthy prior to the blood draw but experienced a recent minor illness, a vigorous workout, or a minor injury, your doctor may simply recommend repeating the test in two to four weeks to see if the values normalize spontaneously.
Correlate with Clinical Symptoms: Persistent elevations prompt a detailed review of symptoms. Are you experiencing morning stiffness, unexplained fatigue, unintended weight loss, joint swelling, skin rashes, or localized pain?
Targeted Secondary Testing: Depending on the clinical clues, a physician will order specific autoantibody panels (such as Antinuclear Antibodies or Rheumatoid Factor), imaging studies, or specialized consultations with rheumatologists, gastroenterologists, or infectious disease specialists.
The smoke alarm analogy revisited
Can a blood test reveal inflammation? Yes, but with an important caveat: it reveals its presence, not its provenance.
Think of tests like CRP and ESR as the biological equivalent of a smoke alarm in a large building. When the alarm shatters the silence, you know with absolute certainty that something requires your attention. However, the piercing sound does not tell you whether there is a roaring fire in the basement, a scorched piece of toast in the kitchen, or merely a faulty detector battery.
By understanding what these blood tests can and cannot accomplish, patients and practitioners can work together more effectively. Rather than inducing panic, an elevated marker serves as a valuable clinical compass, guiding medical professionals past the guesswork and directly toward the underlying root cause, paving the way for targeted, effective treatment and long-term wellness.