Common mistakes and misconceptions when using hydration and movement for glycemic control
Thinking a slow stroll excuses a High-Glycemic feast
People often fall into the trap of overestimating calories burned during casual activity. Walking definitely stimulates GLUT4 glucose transporter translocation to muscle cell membranes, yet a leisurely fifteen-minute shuffle cannot completely neutralize a meal loaded with ninety grams of refined carbohydrates. The catch: many individuals believe ten minutes on a flat sidewalk acts as a magical eraser for systemic insulin resistance. Research indicates that a light walk reduces post-prandial glycemic peaks by roughly 17 percent compared to sitting, which is helpful but not a total cure for poor dietary choices. You still have to respect basic nutritional physiology because no amount of casual stepping can rewrite how your liver processes acute fructose overload.
Ignoring the crucial timing window after meals
Waiting two hours after your last bite to lace up your sneakers completely misses the metabolic boat. Peak plasma glucose levels generally occur between thirty and sixty minutes after eating. If you begin your stroll long after your pancreas has already released a massive wave of insulin to clear the bloodstream, you miss the primary window where contracting muscles absorb glucose independently of insulin. But timing your movement early alters the entire metabolic curve before hyperinsulinemia sets in. Light activity initiated within fifteen minutes of finishing a meal suppresses the initial glucose spike far more effectively than a strenuous workout undertaken hours later when your body has already stored those circulating sugars into adipose tissue.
The unspoken nuance: Micro-Movement and kidney hemodynamics
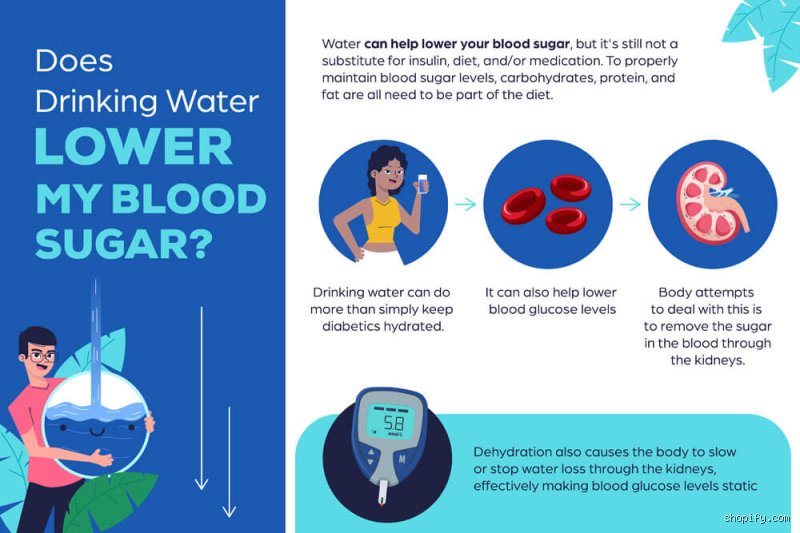
About what actually happens inside your vascular network when you combine adequate fluid intake with gentle physical activity. Hydration expands plasma volume, which lowers overall blood viscosity and allows your kidneys to maintain optimal glomerular filtration rates. Concurrently, even micro-movements—like calf raises or brief two-minute walks every twenty minutes—activate the soleus muscle pump in your lower legs. The soleus muscle possesses a unique metabolic profile that oxidizes blood glucose efficiently without relying heavily on glycogen stores. The real issue is that most people view exercise as an all-or-nothing proposition reserved for dedicated gym sessions.
Maximizing glycemic efficiency through targeted hydration
Drinking approximately 500 milliliters of fluid thirty minutes before meals optimizes gastrointestinal motility and promotes early satiety, while supporting efficient blood flow to working muscle tissue later on. When your vascular bed is well-hydrated, capillaries dilate effectively during light exertion, maximizing the surface area available for glucose transfer from plasma into interstitial fluid and ultimately into muscle cells. (This microscopic exchange mechanism is precisely why chronic dehydration exacerbates insulin resistance over time.) Combining consistent sip-by-sip fluid intake throughout the day with short movement breaks generates a compound metabolic effect that far exceeds the benefits of isolated, intense workouts performed in a state of mild dehydration.
Frequently asked questions
Does drinking water and walking lower blood sugar fast enough during an acute spike?
While mild activity and proper hydration reliably reduce post-meal glucose elevations, they do not act with the immediate speed or potency of prescribed medical interventions like rapid-acting insulin. Clinical data demonstrates that a 15-minute post-meal walk combined with adequate hydration can decrease peak glucose spikes by up to 22 mg/dL over a two-hour window. Drinking water helps your kidneys excrete excess glucose through urine once blood sugar surpasses the renal threshold of roughly 180 mg/dL, but this process takes time to manifest in systemic blood readings. Therefore, while these lifestyle habits are powerful supportive tools for daily glycemic management, you cannot rely on them as an emergency replacement for fast-acting diabetes medications during severe hyper-glycemic episodes.