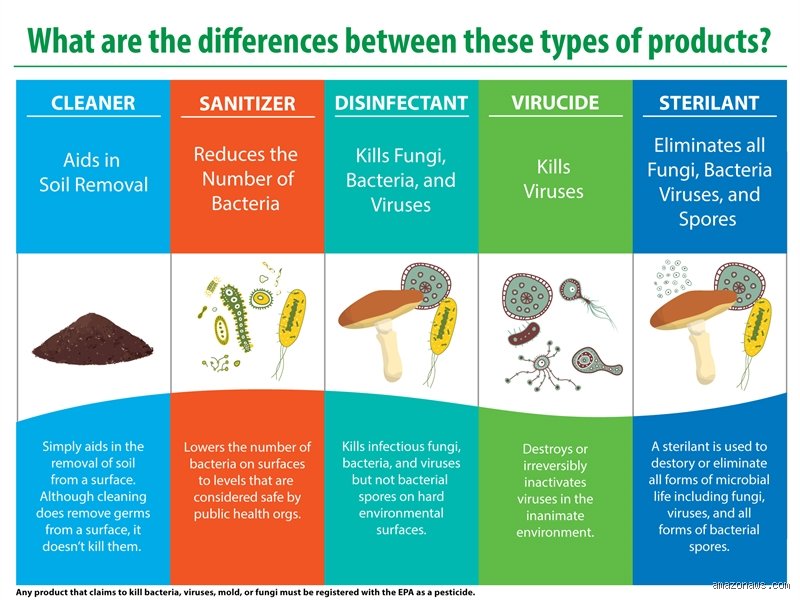
The myth of interchangeability: Disinfection vs. Sanitization in modern hygiene
Asking whether a disinfectant is "better" than a sanitizer is akin to asking whether a surgical scalpel is better than a pocket knife; the answer depends entirely on the specific task at hand, the nature of the surface, the types of pathogens present, and the regulatory environment of the space being treated.
Deconstructing the hygiene hierarchy: Clean, sanitize, and disinfect
To understand why one is not universally "better" than the other, we must first establish the tripartite hygiene hierarchy recognized by agencies such as the U.S. Environmental Protection Agency (EPA), the Centers for Disease Control and Prevention (CDC), and the World Health Organization (WHO).
1. Cleaning: The foundational prerequisite
Cleaning is the mechanical or chemical removal of dirt, debris, dust, organic matter, and a significant portion of surface microorganisms using water, detergents, and surfactants. Crucially, cleaning does not kill germs; it physically displaces them.
Organic matter (such as grease, food residue, blood, or bodily fluids) acts as a physical shield for microorganisms, protecting them from chemical attack. Therefore, sanitization and disinfection can never be performed effectively on a dirty surface. Cleaning is always the indispensable first step.
2. Sanitization: Reducing microbial load to safe levels
Sanitization is a public health standard designed to reduce the number of bacteria on inanimate surfaces to levels considered safe by public health codes or regulations.
The Metric: Typically, a sanitizer must achieve at least a 99.9% reduction (a 3-log reduction) in specific test bacteria (such as Staphylococcus aureus and Klebsiella pneumoniae) within a specified, relatively short contact time (often 30 to 60 seconds).
The Application: Sanitizers are most commonly deployed in food-contact environments—such as restaurant tables, cutting boards, commercial kitchen equipment, and daycare facilities—where food or infant contact makes harsh chemical residues undesirable or hazardous.
3. Disinfection: Destroying pathogenic invaders
Disinfection goes a step further by chemically destroying or inactivating nearly all pathogenic microorganisms (bacteria, viruses, and fungi) on hard, non-porous surfaces, though it does not necessarily eliminate bacterial spores.
The Metric: Disinfectants must achieve a much higher standard, typically a 99.999% reduction (a 5-log reduction) or greater against targeted test organisms. Hospital-grade or broad-spectrum disinfectants must pass rigorous efficacy testing against specific resistant pathogens, including Pseudomonas aeruginosa, Salmonella enterica, and various enveloped and non-enveloped viruses (e.g., influenza, norovirus, and HIV).
The Application: Disinfectants are designed for high-risk environments where infectious disease transmission is a primary concern, such as hospital operating rooms, clinical laboratories, isolation wards, restrooms, and areas experiencing active outbreaks.
The mathematical reality: Log reductions and microbial populations
To truly grasp the functional divide between sanitizers and disinfectants, one must examine the mathematics of microbial reduction. In microbiology, decontamination efficacy is measured in log reductions, where each "log" represents a 90% reduction in the population of living microorganisms.
| Log Reduction | Percentage Reduction | Remaining Microorganisms (from an initial population of 1,000,000) | Regulatory Classification |
|---|---|---|---|
| 1-Log | 90% | 100,000 | Basic cleaning / rinsing |
| 2-Log | 99% | 10,000 | Intermediate cleaning |
| 3-Log | 99.9% | 1,000 | Sanitization (Food contact safe standard) |
| 4-Log | 99.99% | 100 | Advanced sanitization |
| 5-Log | 99.999% | 10 | Disinfection (General commercial/residential standard) |
| 6-Log | 99.9999% | 1 | Hospital-Grade Disinfection / Sterilization baseline |
As this table illustrates, a sanitizer reducing bacteria by 99.9% still leaves one thousand viable organisms behind for every million present. For a dinner table or a cutting board, this is deemed biologically negligible and safe for human ingestion when combined with proper food safety protocols. However, in a surgical suite or an intensive care unit, leaving one thousand viable pathogens on a stainless steel tray could lead directly to catastrophic healthcare-associated infections (HAIs). This is why a disinfectant is strictly required in medical settings, whereas a sanitizer would be dangerously insufficient.
The critical Variable: Dwell Time and Contact mechanics
One of the most widespread misconceptions among consumers is that spraying a disinfectant and immediately wiping it off with a paper towel achieves the claimed 99.999% reduction. In reality, chemical disinfectants and sanitizers are not instant-acting magic potions; they require a precise chemical reaction window known as dwell time (or contact time).
The Chemistry of Inactivation: Active ingredients, such as quaternary ammonium compounds (quats), sodium hypochlorite (bleach), hydrogen peroxide, peracetic acid, or isopropyl alcohol, need uninterrupted physical contact with the cell wall, protein capsid, or lipid envelope of a pathogen to disrupt its cellular integrity, denature its proteins, or compromise its nucleic acids.
The Sanitizer Advantage in Speed: Because sanitizers target lower thresholds of microbial reduction, their chemical formulations are often engineered to work rapidly (often within 30 to 60 seconds), making them practical for fast-paced commercial kitchens where surfaces must be turned over quickly.
The Disinfectant Demand for Patience: True hospital-grade disinfectants frequently require a wet dwell time ranging from 3 to 10 minutes, during which the treated surface must remain visibly wet. If a user wipes the surface dry after 15 seconds, the disinfectant has failed to perform its intended function, rendering the process little more effective than standard soapy water cleaning.
The mechanics of microbial Reduction: Log reductions explained
To fully understand whether disinfection holds superiority over sanitization, one must look beyond marketing claims and examine the technical metrics used by microbiologists: log reduction.
When a product claims to sanitize, standard testing protocols (such as those established by the EPA or AOAC International) require it to reduce bacterial populations by 99.9%, which equates to a 3-log reduction. In practical terms, if a surface starts with one million bacterial cells, sanitization leaves behind roughly one thousand.
Disinfection, by contrast, demands a much higher threshold: a 99.9999% reduction (often rounded or expressed in varying regulatory tiers, but typically targeting a 6-log reduction for hospital-grade formulations). That means out of one million bacteria, only one survives.
However, this statistical leap introduces a critical nuance: Are you trying to eliminate a transient nuisance, or are you trying to break the chain of infection for pathogens?
In a residential kitchen preparing raw chicken, the primary concern is Salmonella or Campylobacter. Sanitization of food-contact surfaces prevents cross-contamination without leaving toxic chemical residues that could migrate into food.
In a clinical setting dealing with Clostridioides difficile spores or bloodborne pathogens, sanitization is wholly inadequate. Here, the complete inactivation provided by high-level disinfectants or sterilants is non-negotiable.
The critical role of dwell Time (Contact Time)
One of the most common points of failure in both consumer and commercial hygiene is the misunderstanding of dwell time (or contact time). Neither sanitizers nor disinfectants work instantaneously upon spraying.
Sanitizers are generally formulated for rapid action on pre-cleaned, non-porous food contact surfaces (like restaurant tables or cutting boards), often requiring 30 to 60 seconds of air-drying to achieve their 3-log reduction.
Disinfectants, because they target a broader and more resilient spectrum of microorganisms, including non-enveloped viruses like norovirus and bacterial endospores, frequently require the surface to remain visibly wet for 3 to 10 minutes.
If a user sprays a commercial disinfectant, wipes it dry after five seconds, and assumes the surface is sterile, the chemical has failed to perform its designated function. In many everyday scenarios, a properly applied sanitizer with correct dwell time outperforms a hastily wiped, improperly used disinfectant.
Surface materiality and chemical compatibility
A common misconception is that stronger is always better. Applying harsh disinfectants indiscriminately across all household and commercial surfaces can cause long-term structural and aesthetic damage.
| Factor | Sanitizers | Disinfectants |
|---|---|---|
| Primary Target | Food-contact surfaces, high-touch general touchpoints (low pathogen risk) | Medical facilities, areas exposed to bodily fluids, high infection-risk zones |
| Residue & Rinsing | Often formulated to leave minimal residue; potable water rinse optional or simple depending on chemical | Frequently leave chemical residues that require rinsing, especially on food-contact surfaces |
| Material Degradation | Lower risk of corrosion, pitting, or polymer breakdown over time | Higher risk of degrading plastics, rubber gaskets, and dulling stainless steel with frequent use |
| Toxicity Profile | Generally milder; lower VOC output | Often higher VOCs, requiring PPE and adequate ventilation |
When choosing between the two, facility managers and homeowners must weigh microbial risk against material longevity. Over### The Crucial Variable: Contact Time and Pathogen Spectrum
To understand whether disinfection is "better" than sanitization, one must look beyond marketing claims and examine the biological definitions enforced by regulatory bodies such as the U.S. Environmental Protection Agency (EPA). Sanitization and disinfection are not points on a simple linear scale where higher is always superior; rather, they are distinct operational protocols designed for entirely different microbiological thresholds.
Sanitization is defined by a specific mathematical benchmark: a reduction of at least 99.9% (a 3-log reduction) in the population of specific test microorganisms (typically Staphylococcus aureus and Klebsiella pneumoniae) within a specified, usually brief, timeframe. Conversely, disinfection demands a far more rigorous standard: a 99.9% to 99.9999% (a 6-log reduction) reduction, which includes the elimination of vegetative bacteria, most fungi, and specific target viruses. Crucially, standard disinfection does not inherently guarantee the destruction of bacterial spores (such as Clostridioides difficile), which requires specialized "sporicidal" disinfectants.
The operational differentiator that dictates efficacy is dwell time (or contact time). Chemical agents require an uninterrupted window of liquid phase contact to disrupt cellular membranes, denature proteins, or oxidize genetic material. A common failure in practical sanitation and disinfection is the violation of dwell times, wiping a surface dry immediately after spraying negates the chemical action, reducing a high-level disinfectant to little more than a basic detergent.
Contextual Application: Where to deploy each protocol
Choosing between a sanitizer and a disinfectant is fundamentally a risk-management exercise. Applying the wrong level of intervention either introduces unnecessary chemical hazards or leaves environments dangerously vulnerable to infectious outbreaks.
Food Preparation and Processing Surfaces: In commercial kitchens and domestic food prep areas, sanitization is frequently the preferred and legally mandated standard. Surfaces that come into direct contact with food (cutting boards, counters, utensils) require a reduction in microbial load to safe levels without leaving toxic chemical residues that could leach into food. Using harsh, broad-spectrum industrial disinfectants on a cutting board can introduce chemical toxicity risks that outweigh the biological hazard unless meticulous rinsing protocols are strictly enforced.
High-Touch Public Infrastructure: Door handles, light switches, elevator buttons, and transit handrails exist in a gray zone where routine sanitation is often inadequate during outbreak scenarios, yet continuous heavy-duty disinfection is impractical. In high-traffic environments, targeted disinfection, particularly focusing on non-porous surfaces during peak viral seasons, mitigates fomite transmission of enveloped viruses like influenza and coronaviruses.
Healthcare and Clinical Settings: In hospitals, long-term care facilities, and dental clinics, disinfection is non-negotiable. Non-critical patient-care items (blood pressure cuffs, stethoscopes, examination tables) require low-level to intermediate-level disinfection, while critical items require sterilization. Here, sanitization is entirely insufficient because the resident and transient microbial populations include opportunistic pathogens capable of causing severe systemic infections in immunocompromised patients.
Residential Environments: For standard home maintenance, the balance depends on the room. Bathrooms and areas exposed to raw meat preparation benefit from periodic disinfection. Conversely, general dusting, floor cleaning, and routine surface upkeep are effectively and safely managed through standard cleaning and sanitization, minimizing chemical exposure for children and pets.
The hidden costs: Chemical Toxicity, resistance, and Environmental impact
Assuming that "disinfection is always better" ignores the physiological and ecological trade-offs of deploying aggressive chemical agents on a routine basis.
1. Chemical Toxicity and respiratory Health
Disinfectants often rely on active ingredients with high oxidative or cellular toxicity potentials, such as sodium hypochlorite (bleach), peracetic acid, accelerated hydrogen peroxide, or high concentrations of quaternary ammonium compounds ("quats"). Overuse or improper dilution of these agents leads to occupational health risks, including chronic asthma, contact dermatitis, and mucous membrane irritation. Studies have linked chronic occupational exposure to certain disinfectants among cleaning staff to an increased incidence of chronic obstructive pulmonary disease (COPD).
2. Antimicrobial resistance and tolerance
A growing body of microbiological research indicates that widespread, indiscriminate use of chemical disinfectants, particularly quats, can drive selective pressure. While bacteria do not "resist" chemical agents in the exact same manner they resist targeted antibiotics, repeated exposure to sub-lethal concentrations of disinfectants can trigger adaptive cellular responses (such as efflux pump overexpression), potentially conferring cross-resistance to vital clinical antibiotics.
3. Environmental persistence and ecotoxicity
Many chemical sanitizers and disinfectants do not degrade harmlessly upon disposal. Quaternary ammonium compounds, for instance, bind readily to organic matter, persist in wastewater treatment sludge, and can be toxic to aquatic ecosystems when discharged into natural water bodies.
Reframing the question, integration over superiority
Is disinfectant better than sanitization? The answer is a definitive no; they are complementary tools in a structured infection control hierarchy.
Declaring one superior to the other is akin to asking whether a scalpel is better than a surgical saw, each serves a specialized function dictated by the specific demands of the environment. Effective hygiene management relies on a tiered approach:
Physical cleaning to remove gross soil and organic debris.
Sanitization for areas requiring safe microbial reduction without chemical residue accumulation (food contact surfaces, routine residential upkeep).
Disinfection for high-risk zones, outbreak containment, and non-porous surfaces exposed to resilient pathogens.
By matching the intervention strictly to the biological risk, individuals and facility managers can achieve optimal public health protection while minimizing chemical hazards and environmental impact.