When someone experiences a profound psychological shock—whether through acute events like an accident, assault, or sudden loss, or chronic experiences like prolonged neglect, abuse, or systemic distress—the immediate aftermath feels like an internal fracture. Days bleed into weeks, months, and sometimes years. Individuals find themselves asking not just when the pain will subside, but whether their brain can ever return to a state of balance, safety, and coherence.
The short, scientifically rigorous answer is both liberating and daunting: there is no universal stopwatch for psychological healing. Unlike a fractured bone that typically knits itself back together in six to eight weeks under proper immobilization, emotional trauma restructures the living landscape of the brain across multiple intersecting biological, psychological, and social dimensions. For some, significant neural recalibration can occur within months of targeted intervention; for others, recovery is a multi-year journey of gradual adaptation, nervous system regulation, and cognitive reframing.
To truly understand why the timeline varies so dramatically, we must first venture beneath the skull to examine how emotional trauma physically alters the brain’s architecture, chemistry, and functional networks. Only by looking at the neurobiology of distress can we map the intricate, non-linear pathway toward neural restoration.
1. The neurobiological landscape: How Trauma rewires the brain
For decades, psychological trauma was viewed strictly through a behavioral or psychodynamic lens, as a memory problem or an emotional wound that required talking through. Modern neuroimaging technologies, including functional MRI (fMRI), diffusion tensor imaging (DTI), and PET scans, have radically shifted this paradigm. We now know that emotional trauma is a physical experience inscribed directly into the gray and white matter of the central nervous system.
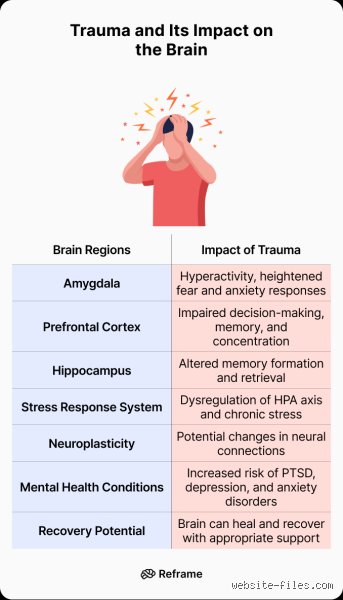
When a person undergoes a traumatic experience, the brain’s survival machinery shifts into overdrive. Three primary structures in the brain become central actors in this drama: the amygdala, the hippocampus, and the prefrontal cortex (PFC).
The amygdala: The Hyper-Vigilant sentinel
The amygdala is an almond-shaped cluster of nuclei deep within the temporal lobes, acting as the brain’s primary threat detector and emotional computer. When a threat or overwhelming emotional event occurs, the amygdala fires rapid distress signals to the hypothalamus, triggering the sympathetic nervous system to flood the body with stress hormones like adrenaline and cortisol.
In the wake of trauma, the amygdala frequently becomes hyperactive and chronically sensitized. It ceases to act merely as a momentary alarm system and instead adopts a permanent stance of high alert. To a traumatized brain, ordinary environments, sounds, or interpersonal cues are constantly misread as potential hazards. This hyper-reactivity is the biological engine behind hypervigilance, flashbacks, and intrusive emotional flooding.
The hippocampus: The disrupted timekeeper
Nestled adjacent to the amygdala, the hippocampus is responsible for contextualizing memories, sorting them into chronological order, distinguishing past danger from present safety, and encoding declarative facts.
Under chronic or severe emotional trauma, sustained high levels of cortisol can physically damage and atrophy the hippocampus. This structural shrinkage impairs its ability to put the brakes on the amygdala and prevents the proper contextualization of memory. Consequently, when a trauma survivor experiences a trigger, the hippocampus fails to signal: "That happened five years ago and you are safe now." Instead, the brain behaves as though the traumatic event is happening right now, locking the memory in a raw, unintegrated, sensory-heavy state.
The Prefrontal Cortex: The offline executive
The prefrontal cortex, specifically the ventromedial and dorsolateral prefrontal regions, represents the seat of executive functioning, impulse control, emotional regulation, rational decision-making, and long-term planning. It is the evolutionary crown of the human brain, responsible for top-down modulation of our primitive impulses.
During trauma, blood flow and metabolic activity are dynamically redirected away from the prefrontal cortex toward survival circuits (the brainstem and amygdala). In chronic trauma states, this functional disconnection can become entrenched. The executive "CEO" of the brain goes offline, leaving the individual struggling with emotional dysregulation, brain fog, impulsivity, and a compromised ability to plan for the future or assess risk accurately.
2. The chemistry of distress: Cortisol, neurotransmitters, and Allostatic Load
Beyond anatomical shifts, emotional trauma profoundly disrupts neurochemistry. A healthy brain relies on a delicate, dynamic balance of neurotransmitters, such as serotonin, dopamine, GABA, and norepinephrine, to regulate mood, motivation, and calm.
In the aftermath of trauma, this chemical baseline is thrown into chronic disarray:
Glutamate and GABA Imbalances: Glutamate (the primary excitatory neurotransmitter) can surge, leading to excitotoxicity where neurons are overstimulated and damaged, while GABA (the primary inhibitory, calming neurotransmitter) is often depleted, fueling persistent anxiety and internal turbulence.
Sustained Allostatic Load: Allostatic load refers to the cumulative wear and tear on the body and brain resulting from chronic stress responses. When cortisol levels remain abnormally elevated (or, in some long-term trauma profiles, flattened and depleted due to adrenal exhaustion), it creates a hostile biological environment for neurogenesis, the birth of new brain cells.
For the brain to heal, it must transition out of this state of chronic biological emergency. It must lower its allostatic load, restore neurotransmitter equilibrium, and reactivate the biological pathways that foster tissue repair, cellular growth, and synaptic pruning.
3. The myth of the fixed timeline: Variables that shape recovery
Because trauma impacts every individual at the cellular, structural, and psychological levels, establishing a rigid timeframe for recovery is impossible. Asking "How long does it take?" is akin to asking "How long does it take to heal from physical illness?" The answer depends entirely on the nature of the condition, the person’s constitution, and the quality of care received.
Several critical variables dictate the speed and trajectory of neural healing:
A. Type, duration, and age of Onset
Single-Incident vs. Complex Trauma: An acute, single-incident trauma (such as a car accident or a sudden natural disaster) often allows for a more localized, streamlined recovery pathway, as the rest of the neural architecture was previously stable. Conversely, Complex PTSD (C-PTSD), arising from chronic, repeated, inescapable interpersonal trauma, especially during childhood, fundamentally alters the developmental trajectory of the brain. When trauma occurs during critical windows of neurodevelopment in childhood, it shapes the very wiring of emotional regulation circuits, requiring a much more patient, foundational rebuilding process.
Age of Onset: A brain that has matured with stable relational attachments possesses a robust structural foundation to fall back upon. A brain that experienced chronic relational trauma during infancy or early childhood has missed crucial developmental milestones, meaning healing involves both repairing damage and building foundational structures for the first time.
B. Biological resilience and genetics
Genetic predispositions play an undeniable role in how the brain processes stress. Variations in genes governing serotonin transporter proteins, brain-derived neurotrophic factor (BDNF), and hypothalamic-pituitary-adrenal (HPA) axis regulation mean that two individuals can experience identical stressors yet exhibit vastly different neurological vulnerabilities and recovery speeds.
C. The therapeutic ecosystem and relational safety
The human brain is an inherently social organ. Emotional trauma is frequently relational in origin, inflicted by betrayal, abandonment, violence, or neglect, and therefore, neurobiological healing is overwhelmingly relational in execution.
When a survivor experiences safe, attuned, and consistent therapeutic interventions, such as somatic experiencing, EMDR (Eye Movement Desensitization and Reprocessing), trauma-informed cognitive behavioral therapy, or safe interpersonal relationships, the brain begins to register safety at a visceral level. This relational safety triggers neuroplastic mechanisms, gradually retraining the amygdala to step down its alarm and allowing the prefrontal cortex to reclaim its regulatory authority.
4. The superpower of change: Understanding neuroplasticity
If trauma represents a set of rigid, maladaptive neural superhighways forged out of survival necessity, healing represents the construction of new, flexible pathways of peace and integration. This is made possible by neuroplasticity, the brain’s lifelong capacity to reorganize itself by forming new neural connections, pruning unused pathways, and adapting to new experiences.
Neuroplasticity does not happen overnight. It is an organic, incremental process governed by repetition, safety, emotional processing, and physiological regulation. As an individual engages in practices that soothe the nervous system, process stuck memories, and re-establish agency, microscopic synaptic changes compound over time. Dendrites sprout new branches; myelin sheaths strengthen healthy communication lines between the prefrontal cortex and the limbic system; and the brain gradually realizes that the present moment is no longer dictated by the ghosts of the past.
In Part II of this article, we will explore the concrete developmental stages of neurobiological recovery, examine how specific therapeutic modalities accelerate neural remodeling, and look at practical, daily practices that empower the brain to reclaim its equilibrium and thrive beyond survival.
Phase 3: Activating neuroplasticity, How the brain rewires
To understand how the brain recovers from emotional trauma, one must first look at neuroplasticity, the brain’s remarkable lifelong capacity to reorganize itself by forming new neural connections. When an individual experiences severe or chronic emotional trauma, neural pathways associated with fear, hypervigilance, and threat detection become deeply entrenched, acting like a well-worn superhighway in the mind. Every time a trigger occurs, the brain automatically speeds down this familiar, highly reactive route.
Healing does not mean paving over or erasing these old pathways entirely; rather, it involves building alternative routes. Through consistent therapeutic practice and safe relational experiences, neurogenesis (the birth of new neurons, particularly in the hippocampus) is stimulated, and synaptic pruning weakens the overactive fear circuits.
Strengthening the Prefrontal Cortex: As recovery progresses, communication channels between the prefrontal cortex (the rational, executive center) and the amygdala (the alarm system) are re-established. The prefrontal cortex learns that it can send inhibitory signals back down to the amygdala, effectively saying, “We are safe right now; the alarm can be turned off.”
Restoring Hippocampal Function: Trauma often fractures how memories are stored, causing past traumatic events to feel as though they are happening in the present moment. As the hippocampus heals, it regains its ability to contextualize memories, cleanly filing them away as events that happened then, rather than threats happening now.
Phase 4: Evidence-Based modalities that accelerate neurological recovery
While the brain has an intrinsic capacity to heal, certain psychotherapeutic and somatic interventions act as catalysts, dramatically expediting the neurological restructuring process. Different modalities target distinct layers of the brain, creating a comprehensive recovery framework.
1. Eye Movement Desensitization and Reprocessing (EMDR)
EMDR utilizes bilateral stimulation (such as side-to-side eye movements, alternating tactile taps, or auditory tones) while a person recalls a traumatic memory. This process mimics the neurological mechanisms of REM sleep, facilitating the interhemispheric transfer of information. It allows the brain to "digest" stuck traumatic memories, integrating them into the broader narrative network so they no longer trigger acute physiological panic.
2. Somatic Experiencing and Bottom-Up therapies
Traditional talk therapy operates top-down, using cognitive reasoning to influence bodily states. However, because trauma is fundamentally stored in the nervous system and body (as eloquently detailed by researchers like Dr. Bessel van der Kolk), bottom-Up approaches are crucial. Somatic Experiencing focuses on bodily sensations and autonomic nervous system discharge, helping patients safely release trapped survival energy (fight, flight, or freeze) without becoming re-traumatized.
3. Neurofeedback and quantitative EEG
Neurofeedback is a specialized form of biofeedback that trains real-time self-regulation of brain function. By monitoring brainwave activity through sensors placed on the scalp, patients learn to consciously alter aberrant brainwave patterns (such as excessive high-beta waves associated with anxiety or hyperarousal) through computer-guided exercises, directly encouraging healthier neural firing patterns.
Phase 5: The role of lifestyle, Somatic integration, and daily practice
Therapy sessions alone do not constitute the entirety of healing. The daily environment and micro-habits practiced outside the clinical setting heavily dictate how quickly and thoroughly the brain remodels itself.
Optimizing Sleep Architecture: Deep slow-wave sleep and REM sleep are the biological windows during which the brain cleanses metabolic waste, consolidates emotional memories, and repairs neural tissue. Chronic sleep deprivation, common in trauma survivors, stunts neuroplasticity and prolongs hypervigilance.
Vagal Nerve Regulation: Techniques that stimulate the vagus nerve, such as slow diaphragmatic breathing, cold-water immersion, humming, and vigorous aerobic exercise, signal safety to the brainstem. Over time, these practices tone the vagus nerve, improving heart rate variability (HRV) and making it easier for the nervous system to transition out of chronic fight-or-flight states.
Co-Regulation and Safe Relationships: Human brains are inherently social organs. Isolation locks the nervous system in defensive postures, whereas safe, attuned interpersonal relationships act as a biological buffer, bathing the brain in oxytocin and fostering secure attachment pathways that counteract the isolation of trauma.
The timeline reality: Why there is no universal clock
Returning to the central question, How long does it take for the brain to heal from emotional trauma?, the most honest scientific answer is variable, fluid, and deeply individual.
[Single-Event Trauma (PTSD)] ------------> Months to a Few Years (with treatment)
[Complex / Developmental Trauma] --------> Multi-Year Journey of Intermittent Restructuring
Single-Incident vs. Complex Trauma: A person who experiences a discrete, sudden event (such as a car accident or a single assault) often experiences rapid neural reorganization with targeted treatment, sometimes showing significant brain-level and symptomatic recovery within 6 to 18 months. Conversely, complex developmental trauma, such as chronic childhood neglect, abuse, or prolonged exposure to domestic violence, alters the foundational architecture of the developing brain. This requires a much longer, multi-year journey of intermittent structural restructuring and reparenting the nervous system.
Biological and Environmental Variables: Age, genetics, baseline stress levels, ongoing exposure to triggers or toxic environments, and access to quality healthcare all act as accelerators or brakes on the healing timeline.
The Non-Linear Trajectory: Recovery is rarely a clean upward slope. It is characterized by spirals, waves, and plateaus. A survivor may feel completely healed for months, only to encounter a profound life stressor that reactivates old neural pathways. This is not a failure or a reset to square one; it is simply the brain navigating an old superhighway out of habit. With continued practice, these resurgence episodes become shorter, less intense, and easier to navigate.
Moving from surviving to thriving
Healing from emotional trauma is not about returning to who you were before the trauma occurred, that version of the self no longer exists, and the brain has changed in response to its environment. Instead, recovery is about forging a resilient, integrated self equipped with a nervous system that knows how to differentiate between historical danger and present safety.
While the brain’s rewiring process demands patience, consistency, and compassionate self-awareness, neuroscience confirms an inspiring truth: the human brain remains plastic throughout our entire lives. No matter how deeply entrenched fear pathways may feel today, the neural circuitry of safety, joy, and connection can always be rebuilt.