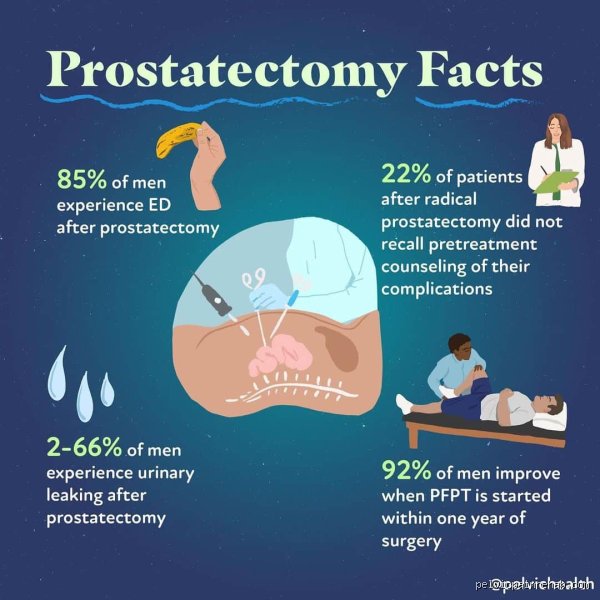
Understanding Radical Prostatectomy: The anatomy of the procedure and the scope of the problem
While this major intervention can be life-saving and serves as a foundational pillar of oncological care, the physiological toll it takes on a patient can be substantial. Evaluating the problems associated with prostate removal requires an unvarnished look into urological engineering, delicate neurovascular preservation, and the profound multi-system challenges that emerge once the gland is detached from its surrounding structures.
1. The Immediate Surgical and perioperative risks
Like any major abdominal or pelvic operation, radical prostatectomy, whether performed via open retropubic incisions, standard laparoscopy, or advanced robot-assisted laparoscopic techniques (RALP), carries standard# Navigating the Complexities: An In-Depth Examination of Radical Prostatectomy Complications and Post-Surgical Challenges (Part 1)
The anatomy of a Life-Altering decision
A prostatectomy, specifically radical prostatectomy, the complete surgical removal of the prostate gland and surrounding tissues, is one of the most common interventions for localized prostate cancer. For thousands of patients diagnosed each year, this procedure represents a vital crossroads in their medical journey, often heralded as a definitive step toward eradicating a potentially aggressive malignancy. However, the decision to undergo prostate removal is rarely straightforward. It requires a delicate, often agonizing calculus that weighs cancer control against the preservation of long-term quality of life.
To truly understand the problems associated with prostate removal, one must first look deeply into the anatomy of the pelvis. The prostate gland is not an isolated organ floating in empty space; rather, it is a hub of complex neurological and muscular networks. Nestled directly beneath the urinary bladder and surrounding the urethra (the tube through which urine and semen leave the body), the prostate shares an intensely intimate neighborhood with the cavernous nerves responsible for erectile function and the delicate sphincteric mechanisms that maintain urinary continence.
When a surgeon operates to remove the prostate, they are navigating a surgical field measured in millimeters, where a hair's-breadth deviation can mean the difference between preserving normal bodily functions and causing profound, permanent disruptions. While surgical techniques have advanced exponentially, transitioning from traditional open retropubic incisions to highly sophisticated laparoscopy and robot-assisted da Vinci systems, the inherent physical risks of operating in this confined space remain a sobering reality.
In this comprehensive first part of our exploration, we will dissect the immediate and intermediate problems associated with prostate removal, moving far beyond generalized risk percentages to examine the specific physiological mechanisms behind urinary incontinence, the profound impact on sexual health, the perioperative risks of major surgery, and the subtle yet powerful psychological toll that shadows the physical recovery process.
1. The Immediate aftermath: Perioperative and Short-Term Surgical risks
Like any major abdominal or pelvic surgery, a radical prostatectomy carries a baseline set of surgical risks that manifest in the operating room and during the immediate postoperative window, typically the first few days to weeks following the procedure. While modern anesthesia and minimally invasive techniques have drastically reduced mortality rates and hospital stays, patients must still contend with significant physiological trauma.
Hemorrhage and blood transfusions
The pelvis is a highly vascular region, cradled by a dense web of blood vessels, including the dorsal penile vein complex and branches of the internal iliac artery. During a prostatectomy, surgeons must meticulously ligate (tie off) or cauterize these vessels to maintain a clear field of vision and prevent excessive blood loss. Despite these precautions, significant bleeding can occur. Historically, open radical prostatectomies frequently required blood transfusions. While robot-assisted techniques have significantly reduced estimated blood loss, the risk of intraoperative hemorrhage remains, requiring constant monitoring of hemoglobin levels and hemodynamic stability in the immediate recovery ward.
Thromboembolic events: DVT and Pulmonary Embolism
Any major pelvic surgery immbolizes the patient for a period and disrupts normal vascular dynamics, creating a prime environment for blood clots. Deep Vein Thrombosis (DVT), the formation of a blood clot in a deep vein, usually in the legs, presents a persistent risk post-surgery. More critically, if a portion of a DVT dislodges, it can travel through the bloodstream to the lungs, resulting in a Pulmonary Embolism (PE), a life-threatening medical emergency. To mitigate this, hospitals employ aggressive prophylaxis protocols, including early ambulation, pneumatic compression boots during and after surgery, and subcutaneous anticoagulant injections (such as low-molecular-weight heparin). Nevertheless, the risk cannot be entirely eliminated.
Anastomotic Leaks
Once the prostate and seminal vesicles are completely removed, the surgeon must reconstruct the urinary tract by reconnecting the neck of the bladder directly to the urethra. This reconnection is known as the vesicourethral anastomosis. Because this newly fused junction must heal under tension while bathed in urine, there is a risk of an anastomotic leak, a failure of the tissue edges to seal completely, allowing urine to escape into the pelvic cavity.
Clinical Implications: A minor leak may resolve spontaneously with prolonged catheterization, but a significant leak can lead to severe pelvic pain, localized infection, abscess formation, and prolonged hospitalization. Surgeons typically perform a cystogram (an X-ray using contrast dye instilled into the bladder) roughly one to two weeks post-surgery to confirm the integrity of the anastomosis before the urinary catheter is removed.
Infection and wound Complications
Infections can manifest in several ways following prostate removal. Surgical site infections (SSIs) can occur at the incision sites, particularly in traditional open procedures or at the multiple small trocar sites used in robotic surgery. More commonly, patients face urinary tract infections (UTIs) introduced or exacerbated by the indwelling Foley catheter that remains in place for 7 to 14 days post-surgery to allow the anastomosis to heal. These infections require targeted antibiotic therapy and can significantly increase patient discomfort, characterized by bladder spasms, fever, and cloudy or foul-smelling urine.
2. The battle for control: Post-Prostatectomy Urinary Incontinence (PPUI)
Perhaps no complication of prostate removal is more universally feared or more immediately disruptive to daily life than urinary incontinence. The human urinary sphincter mechanism relies on two primary components: the internal sphincter (at the bladder neck) and the external sphincter (a ring of striated muscle surrounding the membranous urethra just below the prostate).
During a radical prostatectomy, the internal sphincter is routinely sacrificed because it is intimately attached to, or part of, the prostate itself. Consequently, urinary continence after surgery depends almost entirely on the structural integrity and functional capacity of the external urinary sphincter, as well as the preservation of the surrounding pelvic floor muscles (the levator ani complex).
The Mechanics of Incontinence
Even with nerve-sparing techniques and meticulous apical dissection (where the surgeon separates the prostate apex from the external sphincter), the external sphincter invariably suffers some degree of trauma, stretching, or temporary ischemia (lack of blood flow) during the procedure. The shortening of the urethra required to bridge the gap between the bladder and the remaining urethral stump changes the baseline dynamics of urinary control.
Patients experience varying degrees of Post-Prostatectomy Urinary Incontinence (PPUI), which is broadly categorized based on severity and duration:
Stress Urinary Incontinence (SUI): The most common form of leakage following prostate removal. It occurs when intra-abdominal pressure suddenly increases, such as during coughing, sneezing, laughing, heavy lifting, or changing positions from sitting to standing, and the damaged external sphincter cannot generate enough resistance to prevent urine from escaping.
Urge Incontinence: Characterized by a sudden, intense, and uncontrollable urge to urinate, often resulting in leakage before the patient can reach a restroom. This is frequently driven by post-surgical bladder irritability, overactivity, or changes in bladder compliance as it adjusts to its new anatomical configuration.
Total Incontinence: A rare but devastating complication where the sphincter mechanism is completely non-functional, resulting in continuous, round-the-clock leakage. This typically occurs only if the external sphincter is severely damaged or if the nerve supply is irreparably destroyed.
The Recovery timeline and trajectory
For the vast majority of men, urinary control does not return overnight. The recovery of continence is a gradual, rehabilitative process that unfolds over months.
The Immediate Phase: In the first days and weeks after catheter removal, most men experience significant leakage, requiring the use of multiple absorbent pads per day.
The 3-to-6 Month Window: With natural tissue healing, reduction of localized swelling, and diligent practice of pelvic floor physical therapy (Kegel exercises), the majority of patients experience progressive improvement. Studies indicate that upwards of 70% to 80% of men regain socially acceptable continence (defined as zero pads to one security pad per day) by 12 months post-surgery.
The Long-Term Persistent Cases: A significant minority, ranging from 10% to 20% or more, depending on patient age, baseline bladder function, and surgeon experience, experience long-term or permanent incontinence that fails to resolve after a year. For these individuals, the quality-of-life impact can be profound, leading to social withdrawal, anxiety, depression, and reliance on permanent protective garments.
Interventions for Persistent Incontinence
When conservative measures, such as timed voiding, lifestyle modifications, and pelvic floor physical therapy supervised by specialized therapists, fail to restore continence after 12 months, surgical and medical interventions become necessary:
Male Sling Procedures: For mild to moderate stress incontinence, a synthetic mesh sling can be placed beneath the bulbous urethra to compress it gently upward and restore resistance.
Artificial Urinary Sphincter (AUS): Widely considered the gold standard for moderate to severe post-prostatectomy incontinence. The AUS is an implantable hydraulic device consisting of a cuff that wraps around the urethra, a pressure-regulating balloon placed in the abdomen, and a small pump placed in the scrotum. When the patient needs to urinate, they squeeze the pump to deflate the cuff, allowing urine to pass; the cuff automatically reinflates a few minutes later to restore continence. While highly effective, it is a mechanical device that carries risks of mechanical failure, erosion, or infection over time.
3. The alteration of Intimacy: Erectile Dysfunction and sexual health
The prostate gland's anatomical neighbors include the neurovascular bundles (the cavernous nerves) that travel along the posterolateral edges of the prostate. These microscopic, delicate nerve fibers are responsible for transmitting the electrochemical signals from the brain that trigger an erection.
When a patient undergoes a radical prostatectomy, the primary surgical dilemma is oncological safety, ensuring that all cancer is removed with clear margins. If cancer cells are located near the outer edge of the prostate, the surgeon may have to wide-excise (sacrifice) one or both neurovascular bundles to ensure no microscopic disease is left behind. This choice directly pits cancer eradication against the preservation of erectile function.
Nerve-Sparing vs. Non-Nerve-Sparing approaches
Bilateral Nerve-Sparing: Performed when cancer characteristics (low Gleason score, low clinical stage, low volume on biopsy) allow the surgeon to safely preserve the nerves on both sides of the prostate. This offers the highest statistical probability of regaining unassisted or medication-assisted erections.
Unilateral Nerve-Sparing: Performed when cancer is suspected to be encroaching on one side of the gland. The surgeon preserves the nerve bundle on the cancer-free side while sacrificing the bundle on the affected side.
Non-Nerve-Sparing: Necessary when the tumor is large, aggressive, or directly invading the neurovascular structures. Both nerve bundles are removed. In these cases, spontaneous natural erections are virtually impossible post-surgery.
The physiology of Post-Prostatectomy Erectile Dysfunction (ED)
Even in patients who undergo successful bilateral nerve-sparing surgery, Post-Prostatectomy Erectile Dysfunction is remarkably common. This occurs because the nerves are subjected to unavoidable mechanical stretching, thermal energy from cauterization tools, and localized trauma (traction injury) during dissection.
When the nerves are temporarily stunned or permanently damaged, the corporal bodies of the penis fail to receive the regular nocturnal erections that healthy men experience during sleep. Without these natural nocturnal erections, the smooth muscle tissue inside the penis becomes oxygen-deprived (hypoxic), leading to structural changes known as corporal fibrosis, the replacement of elastic erectile tissue with rigid, non-expanding scar tissue. This process can cause a permanent loss of stretched penile length over time.
Rehabilitation and therapeutic options
Because the recovery of erectile function is notoriously slow, often taking anywhere from 18 to 36 months, medical professionals utilize a concept known as Penile Rehabilitation. The goal is to maximize oxygenated blood flow to the erectile tissues during the nerve recovery window to prevent fibrosis and preserve long-term erectile architecture.
Phosphodiesterase Type 5 (PDE5) Inhibitors: Medications such as sildenafil (Viagra), tadalafil (Cialis), or vardenafil (Levitra) are frequently prescribed, either on a nightly low-dose regimen or an on-demand basis, to stimulate blood flow.
Intracavernosal Injections: Medications (such as alprostadil) injected directly into the side of the penis using a fine needle to produce an erection independently of nerve stimulation.
Vacuum Erection Devices (VED): Mechanical cylinders placed over the penis that create a negative pressure vacuum to draw blood into the corpora cavernosa, followed by placing a constriction ring at the base of the penis to maintain rigidity.
Penile Prosthesis (Implant): For men with permanent, irreversible erectile dysfunction who fail medical therapy, surgical implantation of semi-rigid rods or inflatable cylinders offers a definitive, mechanical restoration of rigidity.
Beyond erectile dysfunction, radical prostatectomy causes complete loss of ejaculation (dry orgasm). Because the prostate and seminal vesicles, which produce the bulk of seminal fluid, are entirely removed, ejaculation of fluid no longer occurs, even though the sensation of orgasm (the neurological climax) is often preserved, albeit fundamentally altered. Removal of the prostate renders the patient permanently sterile, a crucial counseling point for younger men who have not completed their families.
4. Beyond the Physical: The psychological and emotional toll
While medical literature frequently categorizes complications into functional metrics (continence rates, potency scores, complication grades), the human experience of recovering from prostate removal encompasses a deep psychological dimension that is inextricably linked to physical recovery.
The dual impact of urinary leakage and sexual dysfunction strikes at the core of a person’s self-image, masculinity, body integrity, and relational dynamics.
Anxiety, depression, and the "cancer survivor's dilemma"
Following surgery, many patients experience a unique form of psychological whiplash. They have successfully navigated a cancer diagnosis and undergone major surgery, yet they wake up to a daily reality characterized by wearing incontinence pads, dealing with unpredictable bladder leaks, and coping with altered sexual function. This juxtaposition often triggers situational anxiety and clinical depression.
Fear of Recurrence: Even with successful pathology reports showing clear margins, the constant monitoring of Prostate-Specific Antigen (PSA) blood tests casts a psychological shadow. Every follow-up test becomes a high-stakes emotional event, often termed "PSA anxiety."
Loss of Spontaneity: Urinary incontinence and ED introduce rigid planning into everyday life. Simple activities like traveling, exercising, or attending social gatherings require meticulous preparation regarding restroom locations and pad changes, which can lead to social isolation and a withdrawal from previously enjoyed activities.
Impact on intimate partnerships
Sexual dysfunction and urinary incontinence do not happen in a vacuum; they profoundly affect partners and intimate relationships. The sudden disruption of shared sexual expression can create feelings of grief, frustration, and emotional distance between partners.
Communication breakdown is a frequent hazard; partners may struggle to discuss their mutual frustrations, leading to feelings of inadequacy, rejection, or loneliness.
Multidisciplinary survivorship care increasingly emphasizes couples-based counseling and sex therapy to help partners redefine intimacy beyond penetrative sexual intercourse, fostering emotional resilience and adaptation during the multi-year recovery arc.
Conclusion of Part 1
The decision to undergo prostate removal is a high-stakes balancing act between cancer eradication and functional preservation. As we have examined, the physical and psychological toll of a radical prostatectomy extends far beyond the operating room, touching upon fundamental aspects of bodily autonomy, urinary control, sexual identity, and emotional well-being.
In Part 2 of this comprehensive analysis, we will explore intermediate and late-onset complications, including urethral strictures, bladder neck contractures, pelvic floor pain syndromes, oncological recurrence risks, salvage therapies, and the emerging paradigm-shifts in surgical precision and technological innovation designed to mitigate these life-altering challenges.
Navigating the Long-Term realities of Prostate Removal
While the initial decision to undergo a radical prostatectomy is often centered around halting the progression of localized prostate cancer, the journey does not end when the operating room doors close. For most patients, the months and years following the procedure introduce a complex landscape of recovery, adaptation, and management of chronic side effects. Understanding the full scope of these problems requires looking beyond immediate post-operative healing to evaluate how structural anatomical changes impact daily quality of life, emotional well-being, and long-term physiological function.
Urinary control and the path to continence
One of the most immediate and distressing concerns for patients following a prostatectomy is the temporary or sometimes permanent loss of urinary control. The prostate gland sits directly below the bladder and surrounds the urethra, the tube responsible for carrying urine out of the body. During the removal of the gland, the urinary sphincter mechanism, which acts as the primary valve keeping urine contained in the bladder, is inevitably disrupted.
Types of Post-Surgical Incontinence
Stress Urinary Incontinence (SUI): This is the most common form of leakage post-surgery. It occurs when sudden pressure is placed on the abdomen, such as through coughing, sneezing, laughing, heavy lifting, or exercising. Because the damaged or weakened sphincter cannot instantly clamp shut under sudden pressure, minor to moderate leakage happens.
Urge Incontinence: Characterized by a sudden, intense urge to urinate, often accompanied by an inability to reach the restroom in time. This stems from bladder instability or irritation resulting from the surgical reconfiguration of the lower urinary tract.
Recovery timelines and Rehabilitation
For the vast majority of individuals, continence returns gradually. While some men regain complete control within a few weeks, others may require anywhere from six months to a full year. Pelvic floor physical therapy and targeted exercises (commonly known as Kegels) are crucial components of post-operative recovery, helping to strengthen the surrounding supportive musculature. In rare instances where leakage persists past 12 months, secondary medical interventions, such as artificial urinary sphincters or male slings, may be considered.
Sexual function and Intimacy Challenges
The neurovascular bundles responsible for erections run immediately adjacent to the prostate gland. Even with modern "nerve-sparing" surgical techniques designed to meticulously peel these delicate structures away from the tumor, minimizing trauma is difficult, and temporary or permanent erectile dysfunction (ED) is a frequent outcome.
+-------------------------------------------------------------------------+
| Impact of Prostate Removal on Intimacy |
+----------------------------------+--------------------------------------+
| Symptom / Physiological Change | Clinical Cause / Mechanism |
+----------------------------------+--------------------------------------+
| Erectile Dysfunction (ED) | Stretching, bruising, or resection |
| | of cavernous nerves during excision |
+----------------------------------+--------------------------------------+
| Dry Orgasm (Retrograde/Atonic) | Removal of prostate and seminal |
| | vesicles eliminates fluid creation |
+----------------------------------+--------------------------------------+
| Permanent Loss of Fertility | Absence of seminal fluid means sperm |
| | cannot mix into viable ejaculate |
+----------------------------------+--------------------------------------+
The physiology of Post-Operative ED
When nerves are bruised or severed during surgery, the penile tissues temporarily or permanently lose the signaling required to achieve a rigid erection. Age, baseline erectile function prior to surgery## Navigating Long-Term Recovery: The Persistent Challenges After Prostatectomy
While the immediate post-operative period focuses heavily on catheter management, acute wound healing, and initial infection surveillance, the true narrative of prostate removal (radical prostatectomy) often unfolds over the subsequent months and years. For many patients, the physiological adjustments required after the complete excision of the prostate gland extend far beyond the operating room, fundamentally altering aspects of daily life, physical intimacy, and emotional well-being. Understanding these lingering challenges is critical for setting realistic expectations and fostering proactive communication between patients and their multidisciplinary care teams.
Urinary Incontinence: The road to continence
One of the most immediate and pervasive concerns following a radical prostatectomy is the loss of urinary control. Because the prostate sits directly beneath the bladder neck and surrounds the urethra, acting as a natural internal sphincter, its surgical removal inevitably disrupts the delicate urinary closure mechanism. Surgeons must frequently dissect close to or through the external urinary sphincter (the muscular ring responsible for voluntary control of urination) to ensure complete cancer eradication.
The Spectrum of Leakage
Post-prostatectomy incontinence (PPI) manifests in various ways, ranging from mild stress urinary incontinence (SUI) triggered by coughing, sneezing, lifting, or laughing, to total continuous leakage in the immediate weeks post-catheter removal.
Stress Urinary Incontinence (SUI): This is the most common form of long-term leakage. When intra-abdominal pressure rises suddenly, the weakened or stunned external sphincter cannot immediately compensate, leading to involuntary urine loss.
Urge Incontinence: Sometimes associated with bladder spasms or overactivity as the bladder adapts to its new anatomical configuration and altered nerve signaling.
Total Incontinence: Less common, typically resulting from significant trauma or intrinsic weakness of the external sphincter mechanism, often requiring specialized surgical intervention if it persists beyond 12 months.
Recovery timelines and interventions
For the majority of men, continence improves progressively over time. However, the recovery curve is rarely linear.
[Catheter Removal] ---> [Weeks 1-6: Initial Leaks] ---> [Months 3-6: Strengthening] ---> [Month 12+: Plateau/Final Status]
Pelvic Floor Physical Therapy (Kegel Exercises): Re-educating and strengthening the levator ani muscles and the periurethral striated sphincter is paramount. Specialized pelvic floor physical therapists can utilize biofeedback or electrical stimulation to ensure patients are engaging the correct muscle groups rather than compensating with gluteal or abdominal muscles.
Medical Management: In certain cases where mild urge incontinence or bladder instability persists, anticholinergic medications or beta-3 agonists may be prescribed to calm detrusor muscle overactivity.
Surgical Solutions for Refractory Incontinence: For patients who experience persistent, severe incontinence a year or more after surgery, despite dedicated pelvic floor rehabilitation, surgical options remain available. These include the placement of a male sling (which compresses or repositions the bulbar urethra) or an artificial urinary sphincter (AUS), considered the gold standard for severe stress urinary incontinence.
Sexual Dysfunction: Navigating changes in Intimacy
The intersection of the prostate, surrounding nerves, and sexual function is profound. The neurovascular bundles, delicate networks of nerves and blood vessels responsible for achieving and maintaining erections, run immediately adjacent to the prostate gland. Even with modern nerve-sparing surgical techniques (whether performed via open, laparoscopic, or robot-assisted approaches), these nerves can experience significant traction, thermal injury, or structural disruption.
Erectile Dysfunction (ED)
The pathophysiology of post-prostatectomy ED involves both neurogenic and vascular components. When nerves are stretched or severed, the signaling cascade required to dilate the smooth muscle of the corpora cavernosa is impaired.
Penile Rehabilitation: Many urologists advocate for early penile rehabilitation protocols. The goal is to maximize oxygenation of erectile tissue and prevent cavernosal fibrosis (scarring and shortening of the smooth muscle) during the nerve recovery phase, which can take anywhere from 12 to 24 months.
Pharmacotherapy: Interventions typically include oral phosphodiesterase type 5 (PDE5) inhibitors (such as sildenafil or tadalafil), taken either on-demand or in low-dose daily regimens. For non-responders, alternative therapies include intraurethral alprostadil suppositories, intracavernosal injections, or vacuum erection devices (VEDs).
Penile Prosthesis: In cases where permanent, medically refractory ED occurs and patients desire a reliable surgical solution, an inflatable penile prosthesis can be surgically implanted, restoring mechanical rigidity.
Ejaculatory Changes
Beyond erectile function, a radical prostatectomy fundamentally alters the mechanics of ejaculation. Because the prostate and seminal vesicles are completely removed, and the bladder neck is surgically re-anastomosed to the urethra, orgasm becomes dry (anejaculation). While many patients still experience the sensory sensations of climax (orgasmic sensation), the physical expulsion of seminal fluid is absent. For some men, orgasms may also be accompanied by altered intensity, painful muscular contractions (climax-associated cramping), or occasional stress urinary leakage during peak arousal.
Structural and anatomical alterations
The removal of the prostate and the subsequent re-connection of the urinary tract can introduce subtle yet impactful physical changes that influence everyday comfort and long-term health.
Penile length and caliber changes
A frequently under-discussed side effect of radical prostatectomy is a perceived or measured reduction in penile length. This phenomenon is multifactorial, driven by:
Post-operative tissue scarring and fibrosis within the corpora cavernosa.
Lack of nocturnal erections (nocturnal penile tumescence) during the immediate recovery phase, which normally serves to stretch and oxygenate erectile tissues.
Internal anatomical retraction as the membranous urethra is pulled slightly superiorly during bladder-neck-to-urethra anastomosis.
While the reduction in length can be distressing, early use of vacuum erection devices or penile rehabilitation strategies can help mitigate smooth muscle remodeling and tissue retraction.
Inguinal hernia formation
Patients who undergo radical prostatectomy, particularly via open retropubic approaches or extensive robotic dissection, face an increased lifetime risk of developing inguinal hernias. The disruption of the endopelvic fascia and the weakening of the posterior wall of the inguinal canal during pelvic lymph node dissection or prostate mobilization can create anatomical vulnerabilities. Surgeons often evaluate these areas intraoperatively, but patients should remain vigilant for groin bulges, discomfort, or dragging sensations, especially when lifting heavy objects.
Psychosocial and Quality-of-Life dimensions
Physical recovery is inextricably linked to psychological well-being. The dual challenges of managing urinary leakage and navigating sexual rehabilitation can take a heavy toll on a patient’s mental health, self-image, and relational dynamics.
Anxiety and Depression
A diagnosis of prostate cancer followed by major surgery initiates a significant emotional journey. Even when cancer is successfully eradicated, the lingering side effects, such as wearing protective pads or experiencing changes in sexual potency, can trigger anxiety, frustration, and situational depression. Patients may experience a sense of grief regarding the loss of their pre-surgical bodily function and spontaneity.
Partner dynamics and Intimacy
Intimacy changes post-prostatectomy extend to partners, requiring open communication, patience, and a redefinition of physical closeness.
Couples therapy or specialized sexology counseling can provide invaluable frameworks for moving beyond penetrative sex as the sole definition of intimacy.
Support groups, both in-person and digital, offer safe spaces where men and their partners can share practical coping strategies, reduce isolation, and normalize the shared recovery experience.
Summary and proactive Management
While the problems associated with prostate removal, ranging from temporary or persistent urinary incontinence and erectile dysfunction to anatomical changes and psychosocial distress, are undeniably significant, modern surgical refinements and comprehensive rehabilitation programs have vastly improved long-term outcomes. The key to mitigating these challenges lies in a proactive, multidisciplinary approach: engaging with experienced surgical teams, utilizing pelvic floor physical therapy early, establishing structured rehabilitation regimens, and maintaining open lines of communication regarding both physical hurdles and emotional health.